Related Experiment Video
Updated: Oct 19, 2026

Non-fluoroscopic Catheter Tracking for Fluoroscopy Reduction in Interventional Electrophysiology
Published on: May 26, 2015
Cardiac memory after radiofrequency ablation of accessory pathways: the post-ablation T wave does not forget the
B Herweg1, J D Fisher, A Ilercil
1Department of Medicine, Cardiology Division, Arrhythmia Service, Montefiore Medical Center, Albert Einstein College of Medicine, Bronx, NY 10467-2490, USA.

Introduction:
Normalization of the pre-excited QRS following ablation is accompanied by repolarization changes but their directional relationship to changes in ventricular activation has not been well characterized.
Methods:
Accordingly, we measured QRS and T wave vectors and QRS-T angles from 12 lead ECG recordings immediately before and after accessory pathway (AP) radiofrequency ablation in 100 consecutive patients. Patients with bundle branch block, intraventricular conduction defect or intermittent pre-excitation were excluded, leaving a study group of 45 patients: 35 with pre-excitation and 10 with concealed APs.
Results:
With AP ablation, changes occurred in the QRS and T wave vectors and QRS-T angles that were essentially equal and opposite, so that the newly normalized QRS complex and QRS vector were accompanied by a T wave whose vector approximated that of the pre-ablation QRS vector. This tended to maintain a large QRS-T angle: 72 degrees +/- 50 degrees before, and 54 degrees +/- 34 degrees after QRS normalization (p = NS). A QRS-T angle >40 degrees was found before and after ablation in 22/35 patients (63%) with baseline pre-excitation; but never in patients with a concealed AP (p = 0.001). The angle between the pre-excited QRS and the post-ablation T wave was 35 degrees +/- 37 degrees, and
Conclusion:
T-wave changes after ablation of APs (1) are dependent on anterograde AP conduction at baseline and are not observed with concealed APs; (2) correlate in magnitude directly with the change in QRS axis and inversely with the anterograde AP-ERP; (3) are related to AP location. With termination of pre-excitation secondary repolarization changes immediately disappear and the post ablation T wave axis approximates that of the pre-excited QRS. Recognition of this sequence may prevent unnecessary clinical interventions.
More Related Videos
 09:13
Remote Magnetic Navigation for Accurate, Real-time Catheter Positioning and Ablation in Cardiac Electrophysiology Procedures
Published on: April 21, 2013
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
 01:30
Cardiac Action Potential
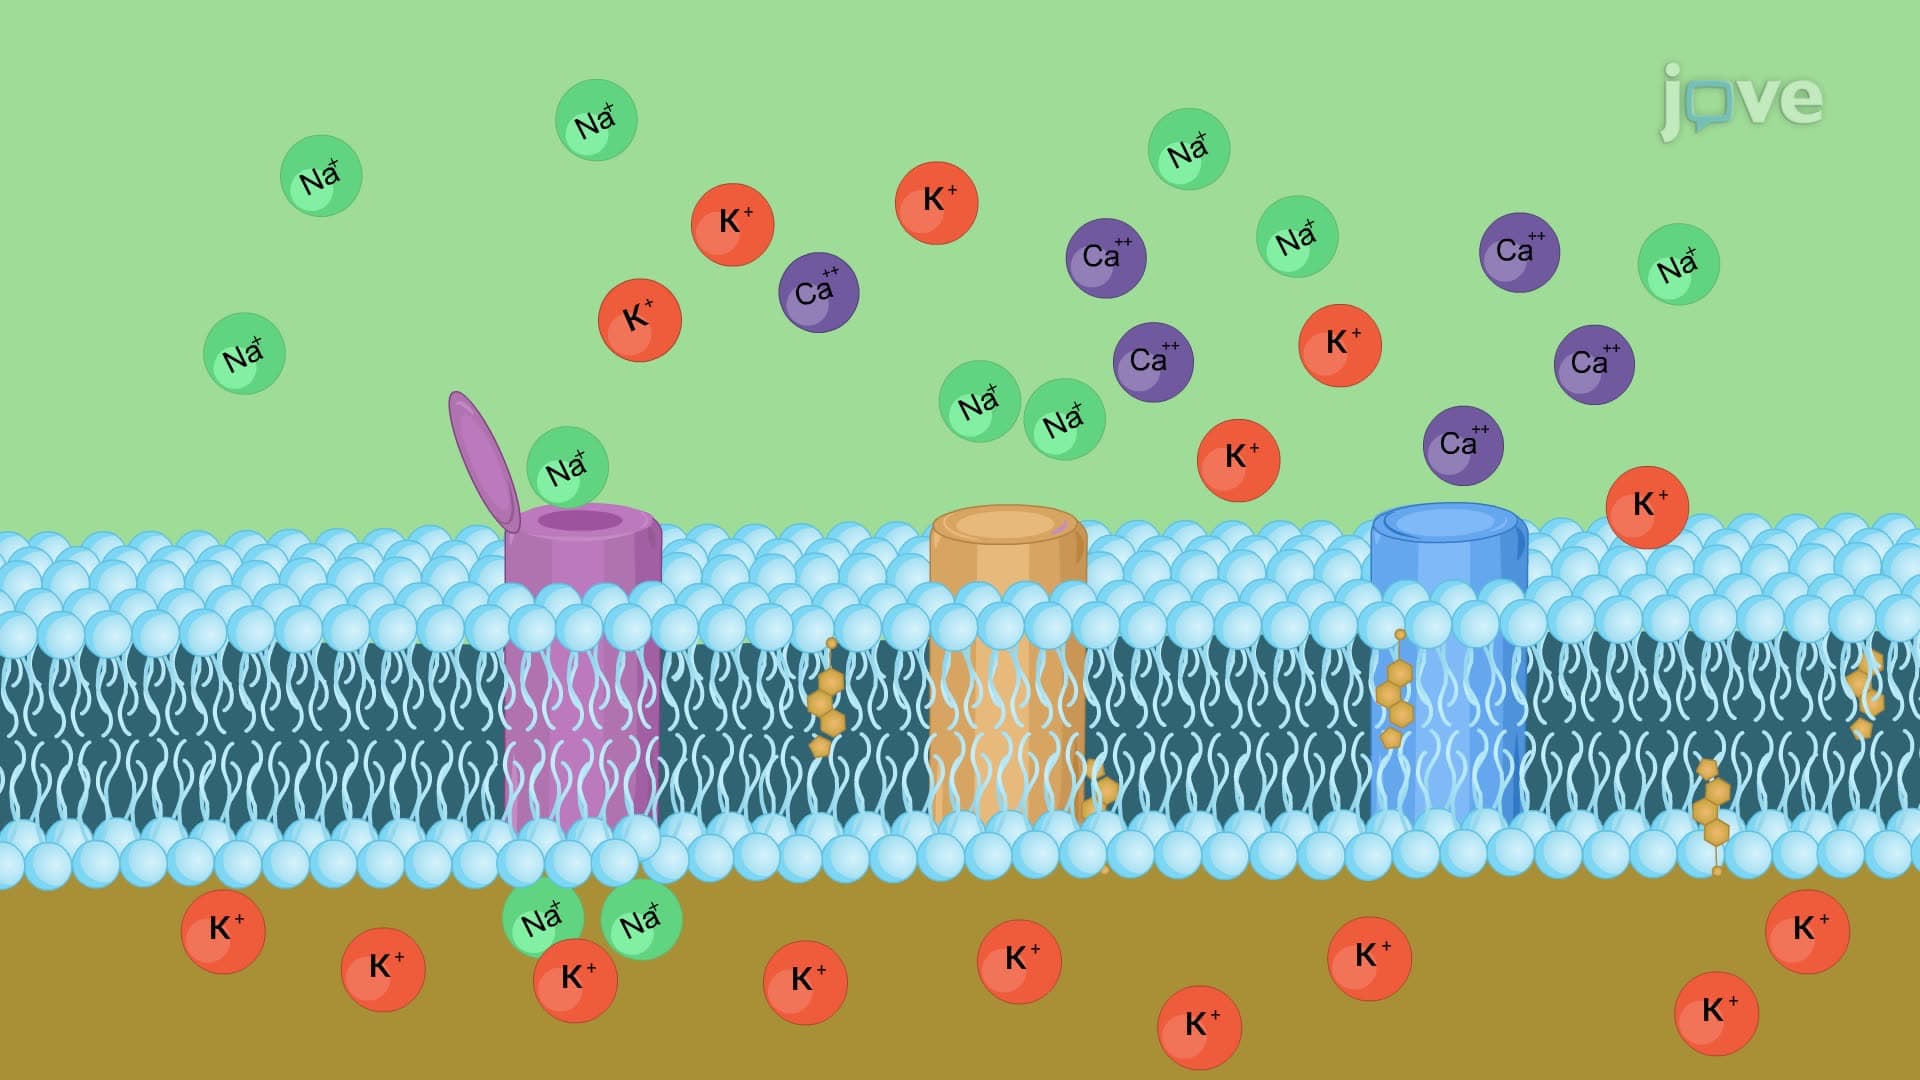
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...
 01:28
Mechanism of Cardiac Arrhythmias
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias