Related Experiment Video
Updated: Oct 13, 2026
Guide Wire Assisted Catheterization and Colored Dye Injection for Vascular Mapping of Monochorionic Twin Placentas
Published on: September 5, 2011
[Intrauterine death in twin pregnancies]
1Département de Gynécologie-Obstétrique, Centre Hospitalier Universitaire Vaudois, Lausanne. Yvan.Vial@chuv.hospvd.ch

The loss of a fetus in a multiple pregnancy is relatively frequent. The main risk factor is a monochorionic twin pregnancy. If fetal loss occurs after 16 weeks of pregnancy, the survivor is also at increased risk of intrauterine death. In monochorionic twins, the risk of neurological sequelae can be as high as 25%. These lesions are due to acute episodes of hypoperfusion immediately following the death of the co-twin. Maternal complications including coagulation disorders are rare. The management will vary according to the type of placenta, the gestational age and the condition of the surviving twin. When the last trimenon has been reached, rapid delivery is probably the safest management. In monochorinoic biamniotic twins, the risk to the survivor often justifies the induction of delivery between 28 and 32 weeks of gestation after steroids have been administered. In most cases, before the 28th week of gestation, a conservative management will be proposed. In monochorionic monoamniotic twins, immediate delivery should be considered as soon as fetal viability is reached.
The loss of a fetus in a multiple pregnancy is relatively frequent. The main risk factor is a monochorionic twin pregnancy. If fetal loss occurs after 16 weeks of pregnancy, the survivor is also at increased risk of intrauterine death. In monochorionic twins, the risk of neurological sequelae can be as high as 25%. These lesions are due to acute episodes of hypoperfusion immediately following the death of the co-twin. Maternal complications including coagulation disorders are rare. The management will vary according to the type of placenta, the gestational age and the condition of the surviving twin. When the last trimenon has been reached, rapid delivery is probably the safest management. In monochorinoic biamniotic twins, the risk to the survivor often justifies the induction of delivery between 28 and 32 weeks of gestation after steroids have been administered. In most cases, before the 28th week of gestation, a conservative management will be proposed. In monochorionic monoamniotic twins, immediate delivery should be considered as soon as fetal viability is reached.
More Related Videos
 09:52
Accurate and Simple Evaluation of Vascular Anastomoses in Monochorionic Placenta using Colored Dye
Published on: September 5, 2011
 09:51
Model Surgical Training: Skills Acquisition in Fetoscopic Laser Photocoagulation of Monochorionic Diamniotic Twin Placenta Using Realistic Simulators
Published on: March 21, 2018
Related Concept Videos
 02:57
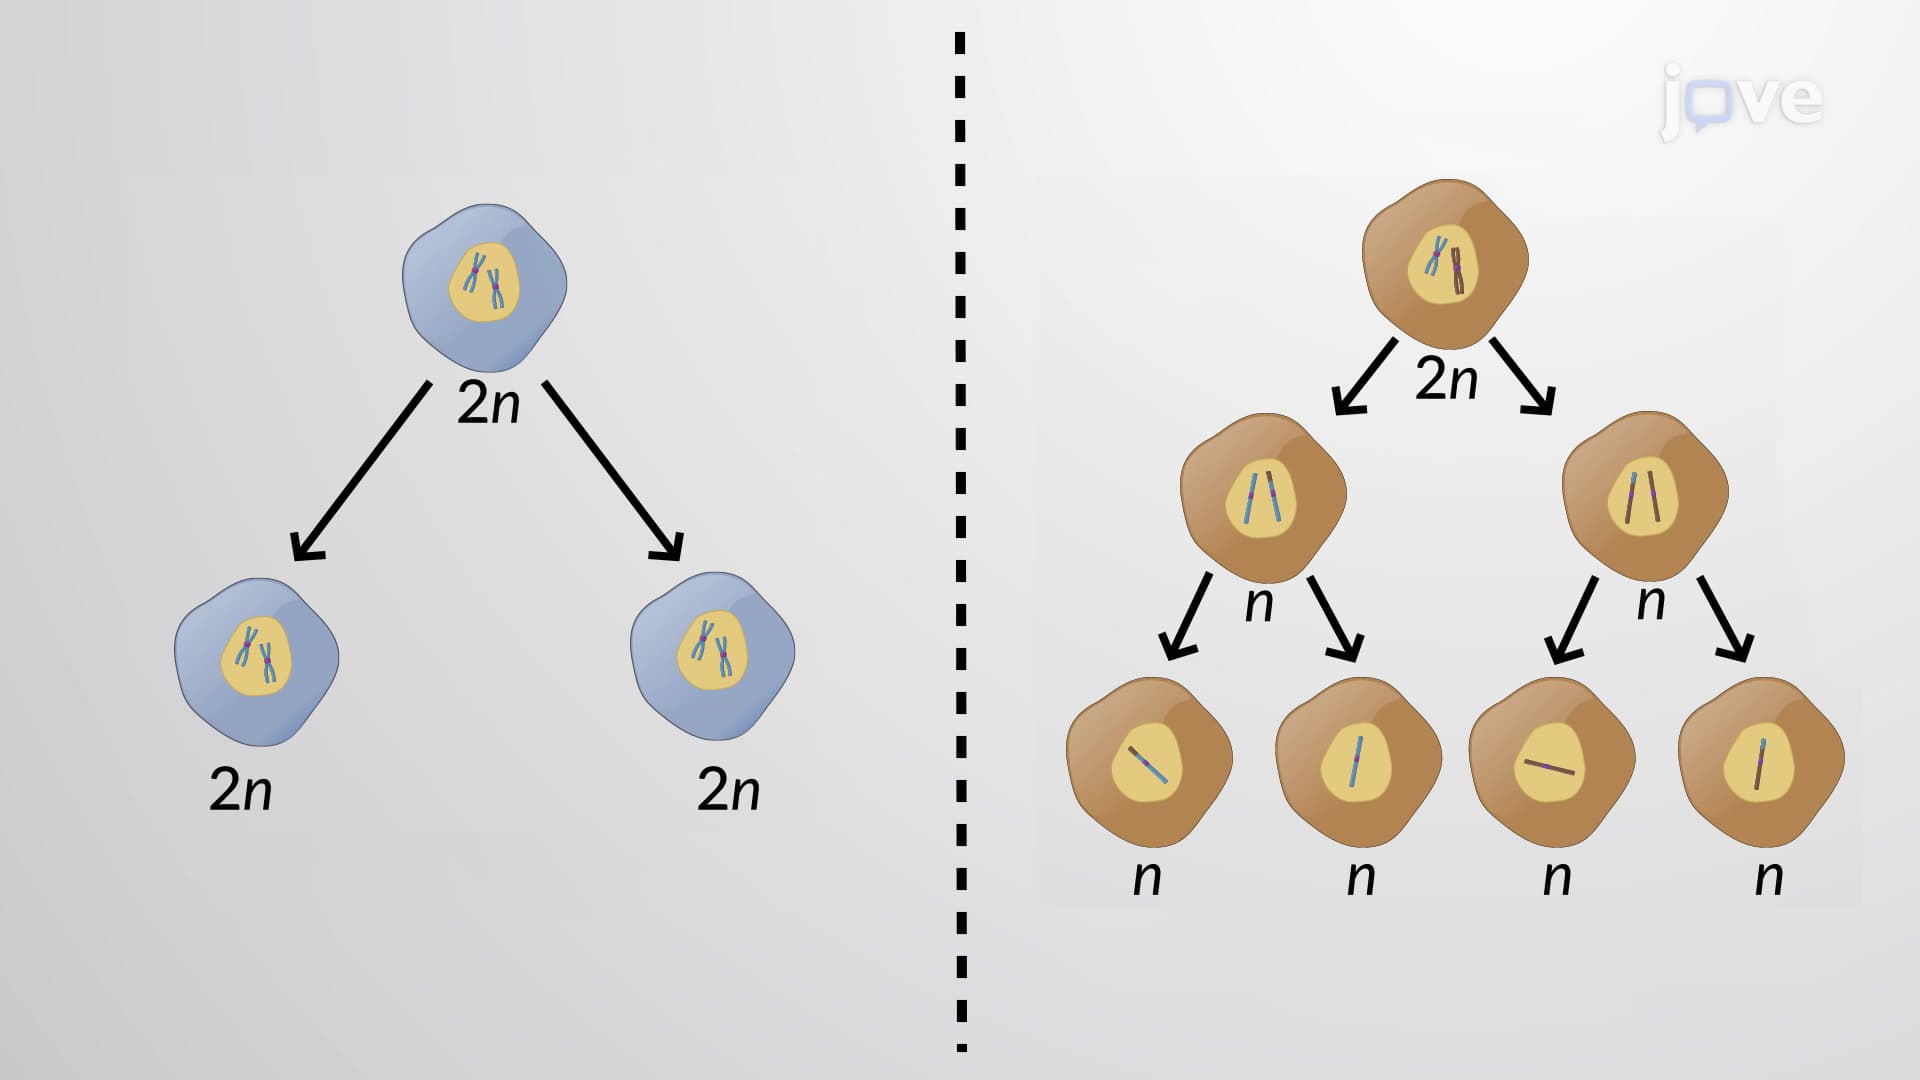
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:07
Teratogenicity
 01:24
In Vitro Fertilization
The IVF process begins with ovarian stimulation, during which reproductive endocrinologists prescribe hormonal medications to stimulate the ovaries to produce multiple eggs instead of the single...
 01:21
Intrauterine Drug Delivery Systems