Related Experiment Video
Updated: Oct 13, 2026

Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Optimal dosing of intravenous tacrolimus following pediatric heart transplantation
B V Robinson1, G J Boyle, S A Miller
1Department of Pediatrics, University of Pittsburgh School of Medicine, Pennsylvania, USA.

Background:
Early experience with intravenous tacrolimus at high doses (0.1-0.15 mg/kg/day) was associated with frequent clinical toxicity. The optimal dosing regimen after pediatric heart transplantation is unknown.
Methods:
We retrospectively reviewed data on the last 45 pediatric heart transplant recipients to document the time required to achieve therapeutic blood levels and the safety of 2 differing intravenous dosing regimens (tacrolimus 0.03 & 0.05 mg/kg/day as continuous i.v. infusion). Target plasma levels were (1.2-1.7 ng/ml) with levels >2.0 ng/ ml considered toxic, and target whole blood levels were 15-20 ng/ml with levels >25 ng/ml considered toxic.
Results:
Mean age at transplantation was 7.5 +/- 5.6 years (0.1-18), and 14 were infants. Intravenous tacrolimus was commenced at a mean of 7 +/- 3 hours (range 2-16) after arrival in the ICU. Eight patients were excluded from analysis because of protocol modifications. Of the remaining 37 pts, 9 received initial infusion at 0.03 mg/kg/day; 3 (33%) achieved 'therapeutic' levels within 48 hours and 1 patient had a toxic level (27 ng/ml) at 36 hours. Twenty-eight patients received 0.05 mg/kg/day; 18 (64%) achieved therapeutic levels within 48 hours and 9 (32%) developed toxic levels. Patients with toxic whole blood levels had higher tacrolimus levels on first blood assay compared to those who did not develop toxicity (16.4 +/- 3.4 vs 9.3 +/- 3.9, p < .0001; level >10 ng/ml on first assay in 7/7 toxic patients vs 7/19 without toxicity, p = .004). Patients receiving the higher dose regimen had fewer episodes of moderate or severe rejection (> or =Grade 3A) at first biopsy than those receiving the lower dose infusion (32% vs 75%; p = .046). No patient required renal dialysis.
Conclusions:
Dosing below 0.05 mg/kg/day may result in clinically important delay in achieving therapeutic levels. Toxicity may be reduced by frequent monitoring of levels for the first 48 hours after transplantation especially when the initial level is >10 ng/ml.
Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:15
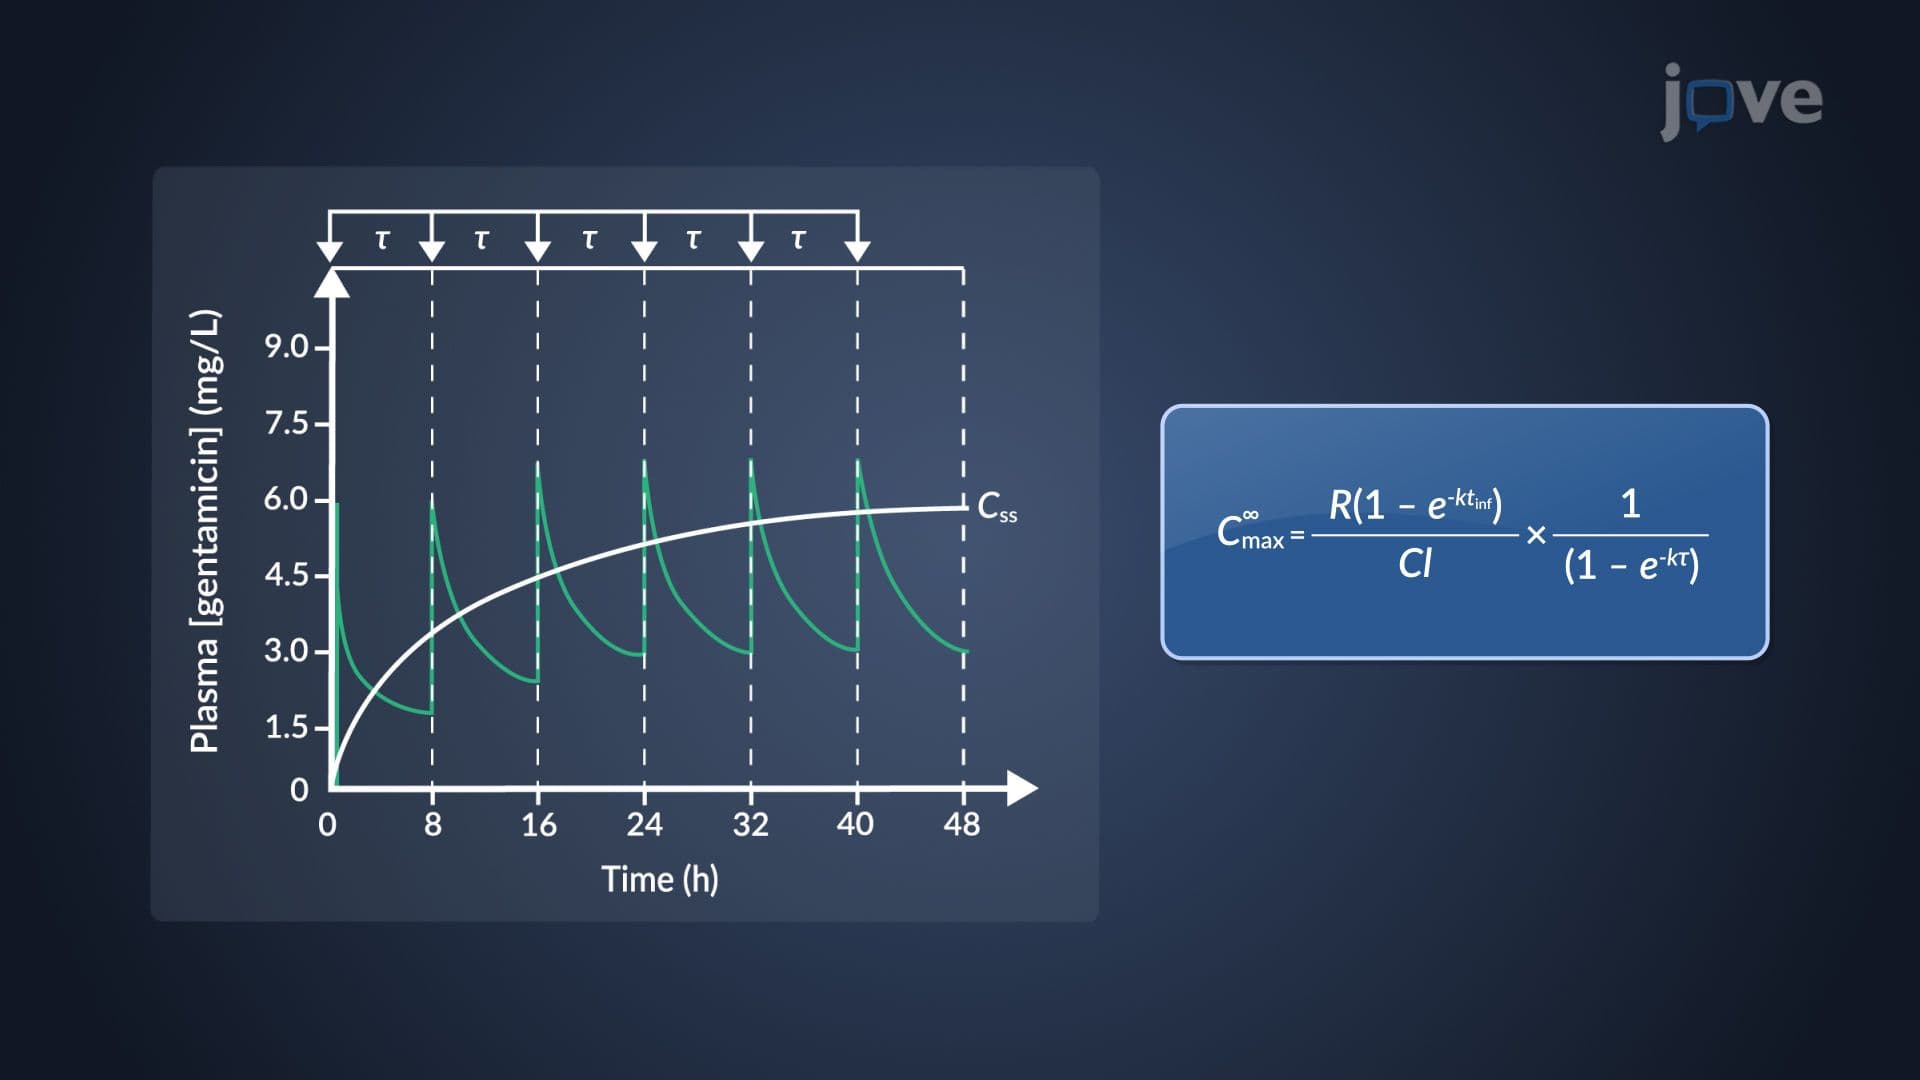
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:29
Drug Dosing: Infants and Children
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:26
Kidney Transplant II: Surgical Procedure