Related Experiment Video
Updated: Aug 19, 2026

04:44

Imaging Features of Systemic Sclerosis-Associated Interstitial Lung Disease
Published on: June 16, 2020
Pneumatosis cystoides intestinalis: a pathophysiologic explanation of the roentgenographic signs
Gastrointestinal Radiology
|January 1, 1976

Abstract:
Pneumatosis intestinalis was first described by DuVernoi in 1730. The roentgenographic, gross, and microscopic apthologic changes are secondary to noncommunicating gas-filled cysts which occur either in submucosa or subserosa. The clinical findings, roentgenologic signs, and treatment are discussed. A differential diagnosis and pathophysiologic explanation for the changes are presented.


Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Evaluating the rectum and anus plays a crucial role in conducting a thorough physical examination of the gastrointestinal system. Although it may be uncomfortable and often embarrassing for the patient, it holds immense diagnostic value, particularly in detecting gastrointestinal diseases and abnormalities. This guide will explain how to perform this assessment using inspection and palpation methods.
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:08
Pneumothorax II: Pathophysiology
Pneumothorax means the presence of air in the pleural space — the thin potential gap between the visceral and parietal pleura. This condition disrupts the normal pressure balance that keeps the lungs inflated, leading to partial or complete collapse of the affected lung.Normal physiologyUnder normal conditions, the pleural space maintains a slightly negative intrapleural pressure, which keeps the lungs expanded against the chest wall. This negative pressure creates a delicate balance between...
 01:10
Atelectasis II: Pathophysiology
Atelectasis develops when alveoli lose their air and collapse inward. Because lung tissue is naturally elastic, these air sacs shrink rather than remaining open. Collapsed alveoli are no longer ventilated, reducing their role in gas exchange. Blood flow may continue in these regions, creating a ventilation–perfusion mismatch. Clinical findings include decreased breath sounds, dullness to percussion, reduced chest expansion, and decreased tactile fremitus as sound transmission through collapsed...
 01:07
Intestinal Obstruction II: Pathophysiology
Intestinal obstruction triggers a series of physiological responses, starting with gas and fluid accumulation in the bowel segment proximal to the obstruction, leading to distension. This distended intestine compresses the diaphragm, hindering lung expansion and potentially leading to reduced respiratory effort, atelectasis, and pneumonia.To overcome the blockage, the gut intensifies contractions, causing colicky abdominal pain, nausea, and vomiting, which reduces fluid and food intake and...
 01:20
Inflammatory Bowel Disease II: Ulcerative Colitis
Ulcerative colitis is a chronic inflammatory disorder of the colon characterized by continuous mucosal inflammation that typically begins in the rectum and extends proximally in a uniform pattern. Its pathogenesis involves a complex interplay of genetic predisposition, immune dysregulation, and environmental influences. These factors converge to impair the colon’s epithelial defenses and promote an exaggerated inflammatory response against luminal contents.Breakdown of the Mucosal BarrierA...
 01:27
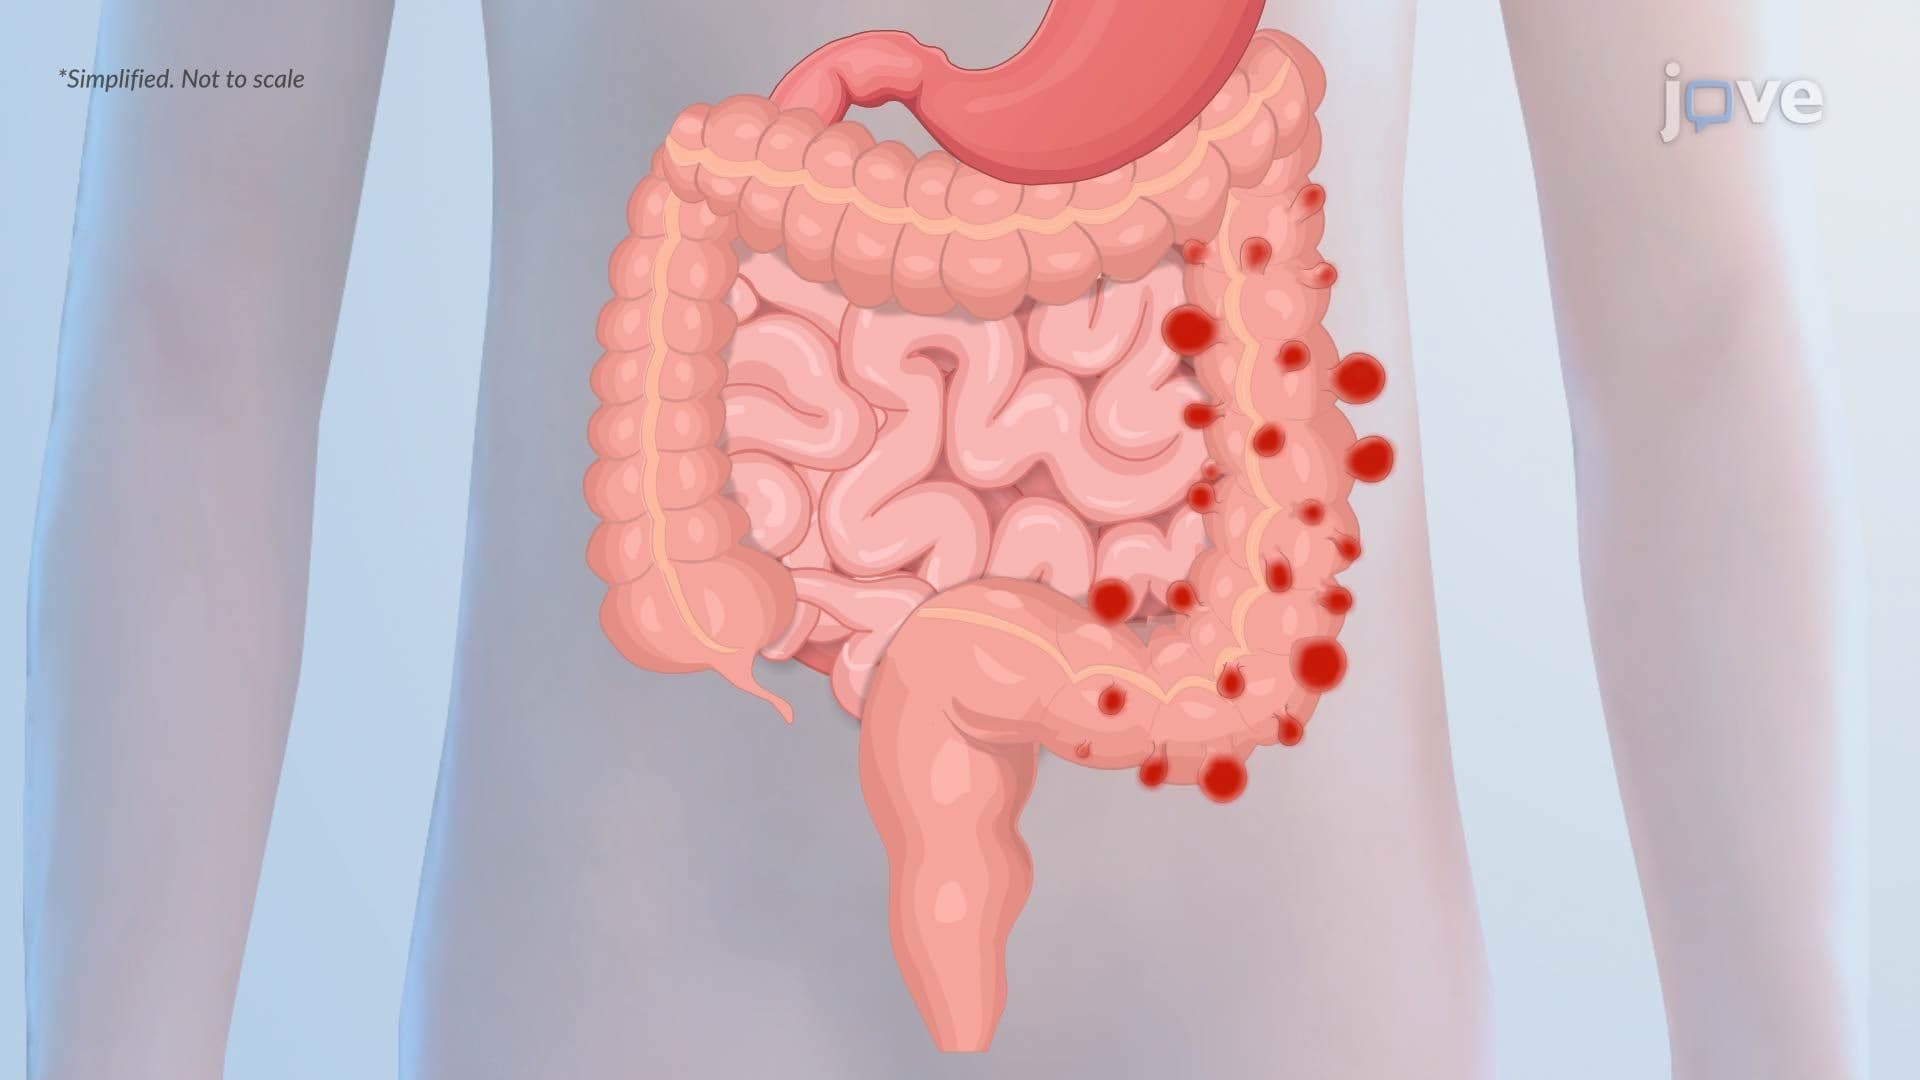
Diverticular Disease of the Colon
Diverticular disease involves the formation of diverticula—small sac-like outpouchings of the colonic wall—and their complications. It most commonly affects the sigmoid colon due to higher intraluminal pressure and structural vulnerability. It results from structural weakness and increased pressure in the colon, producing pseudodiverticula that may remain silent or progress to inflammation and serious complications.Structure of DiverticulaIn diverticulosis, these outpouchings are...