Related Experiment Video
Updated: Oct 17, 2026

Minimally Invasive Endoscopic Intracerebral Hemorrhage Evacuation
Published on: October 15, 2021
Safety of acute normovolemic haemodilution with hydroxyethyl starch during intracranial surgery
K M Kiran Prasad1, T S Devaragudi, R Christopher
1Department of Neuroanaesthesia, National Institute of Mental Health and Neurosciences, Bangalore, 560029, India.

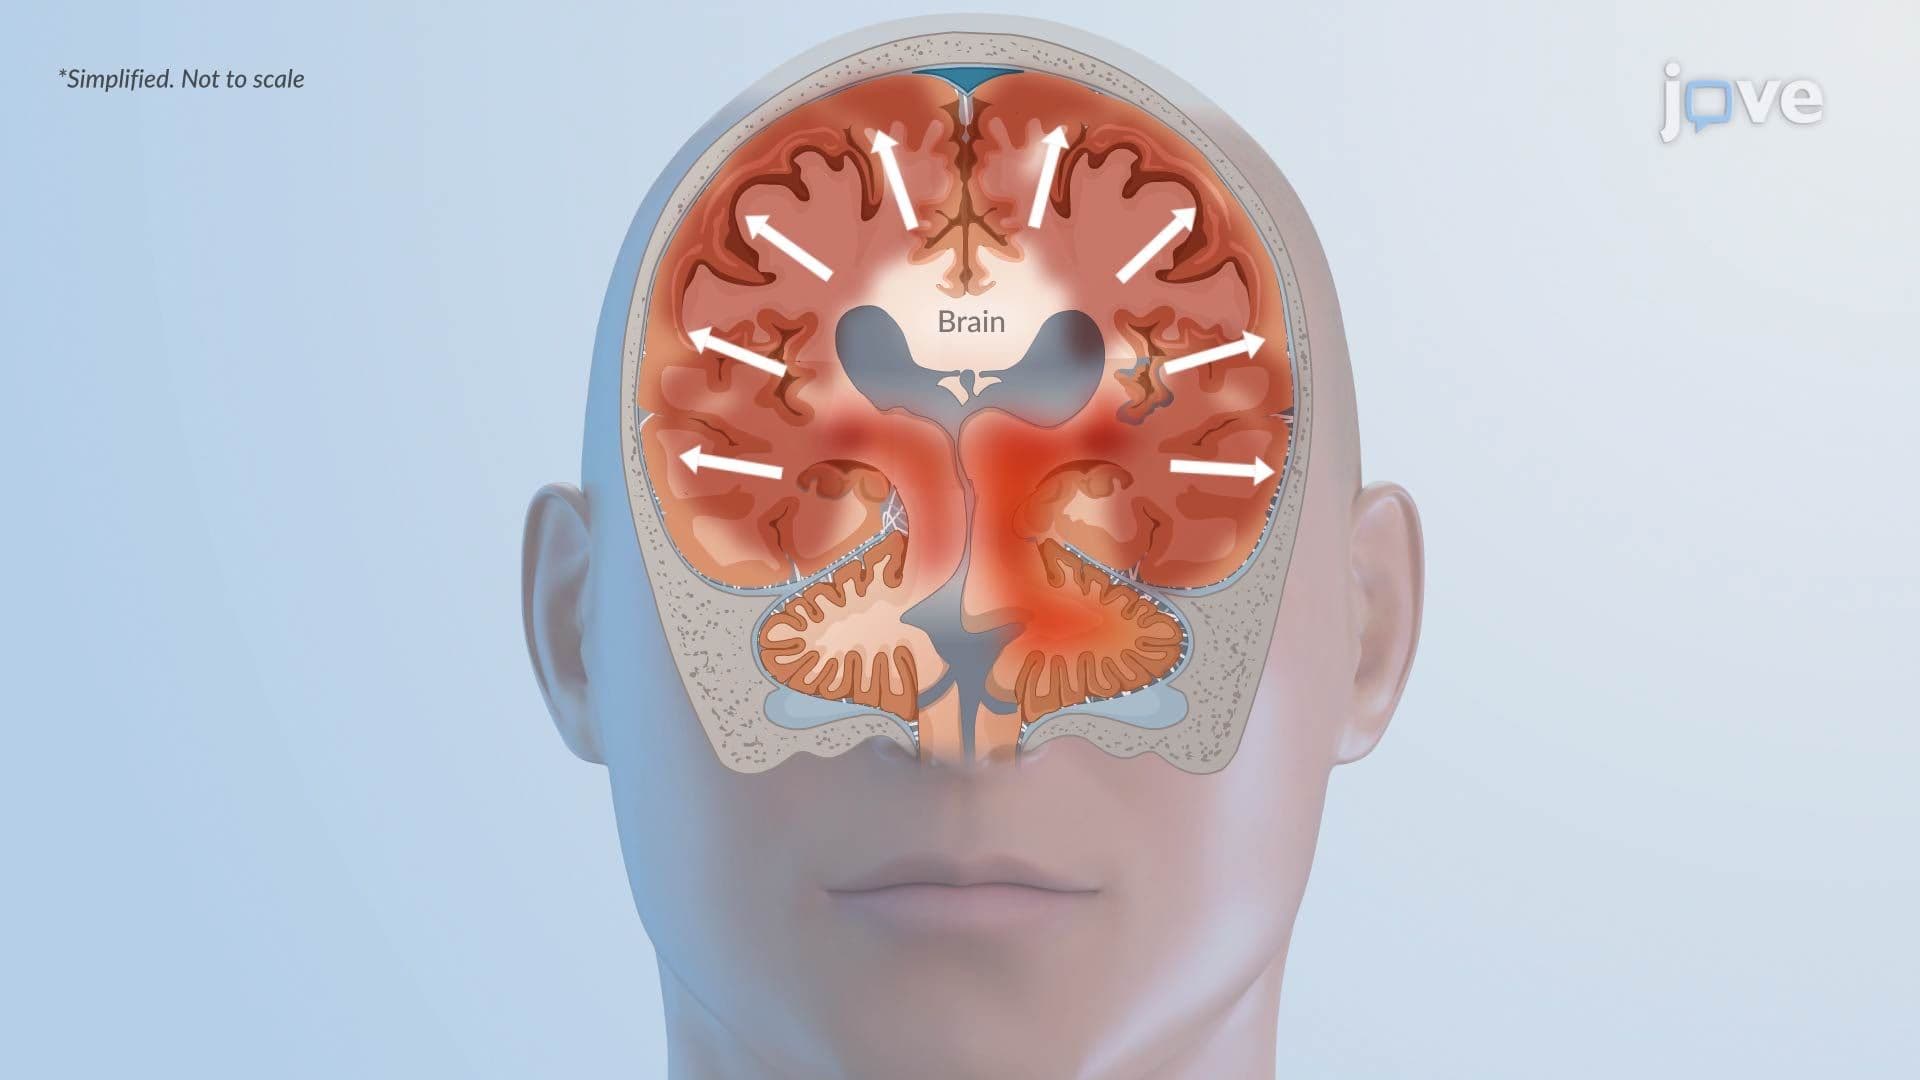
The effect of acute normovolemic haemodilution on haemodynamics, serum osmolality and coagulation parameters was studied in 20 patients undergoing intracranial surgical procedures. After induction of anaesthesia, 740+/-153 ml of blood was collected and the same was replaced with an equal volume of 6% hexaethyl starch. Heart rate (HR), blood pressure (BP), central venous pressure (CVP) and end tidal carbon dioxide tension (Et CO2) were monitored for 45 min. Haemoglobin concentration (Hb), haematocrit (Hct), serum osmolality (Osm), bleeding time (BT), prothrombin time (PT) and platelet count were determined before and 45 min after haemodilution. Hb and Hct were significantly lower following haemodilution (13.1+/-1.8 and 10.3+/-1.7 g/dL for Hb and 38.0+/-4.6%. and 30.1+/-4.5% for Hct). There was no significant change in the HR, BP and Et CO2 throughout the study period. CVP increased marginally from 35 to 45 min but was within normal limits. There was no significant change in serum osmolality, bleeding time and prothrombin time following haemodilution. Platelet count decreased following haemodilution but the values were within normal limits. The brain relaxation, as assessed by a semiquantitative scale, was satisfactory in all cases. None of the patients developed intraoperative brain swelling. In conclusion, acute normovolemic haemodilution with hexaethyl starch is tolerated well haemodynamically. It does not cause changes in serum osmolality which can increase brain oedema. It has no adverse effect on intraoperative haemostasis. It is a safe technique to decrease homologous blood transfusion during intracranial surgery.
The effect of acute normovolemic haemodilution on haemodynamics, serum osmolality and coagulation parameters was studied in 20 patients undergoing intracranial surgical procedures. After induction of anaesthesia, 740+/-153 ml of blood was collected and the same was replaced with an equal volume of 6% hexaethyl starch. Heart rate (HR), blood pressure (BP), central venous pressure (CVP) and end tidal carbon dioxide tension (Et CO2) were monitored for 45 min. Haemoglobin concentration (Hb), haematocrit (Hct), serum osmolality (Osm), bleeding time (BT), prothrombin time (PT) and platelet count were determined before and 45 min after haemodilution. Hb and Hct were significantly lower following haemodilution (13.1+/-1.8 and 10.3+/-1.7 g/dL for Hb and 38.0+/-4.6%. and 30.1+/-4.5% for Hct). There was no significant change in the HR, BP and Et CO2 throughout the study period. CVP increased marginally from 35 to 45 min but was within normal limits. There was no significant change in serum osmolality, bleeding time and prothrombin time following haemodilution. Platelet count decreased following haemodilution but the values were within normal limits. The brain relaxation, as assessed by a semiquantitative scale, was satisfactory in all cases. None of the patients developed intraoperative brain swelling. In conclusion, acute normovolemic haemodilution with hexaethyl starch is tolerated well haemodynamically. It does not cause changes in serum osmolality which can increase brain oedema. It has no adverse effect on intraoperative haemostasis. It is a safe technique to decrease homologous blood transfusion during intracranial surgery.
Related Concept Videos
 01:24
Hemodialysis II: Procedure and Complications
 01:21
Cytotoxic Edema: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction