Chest physiotherapy for preventing morbidity in babies being extubated from mechanical ventilation
Related Experiment Video
Updated: Aug 13, 2026
The Perinatal Asphyxiated Lamb Model: A Model for Newborn Resuscitation
Published on: August 15, 2018
1Perinatal Epidemiology Unit, Mater Hospital, Raymond Terrace, South Brisbane, Queensland, Australia, 4101. vflenady@mater.org.au

Insights
Active chest physiotherapy for extubating babies showed no clear benefits for preventing lung collapse. While it may reduce reintubation rates, more research is needed due to small trial sizes and limited safety data.
Area of Science:
- Neonatal Medicine
- Respiratory Therapy
- Evidence-Based Practice
Background:
- Neonatal respiratory failure often requires mechanical ventilation.
- Extubation carries risks such as lung collapse and reintubation.
- Active chest physiotherapy is a potential intervention to aid in the extubation process.
Purpose of the Study:
- To evaluate the effectiveness of active chest physiotherapy in neonates undergoing extubation from mechanical ventilation.
- To assess the impact on postextubation outcomes like lobar collapse and reintubation rates.
Main Methods:
- Systematic review of randomized or quasi-random trials comparing active chest physiotherapy with non-active methods or no intervention.
- Searches conducted using the Neonatal Review Group's standard strategy.
- Methodological quality assessed by two independent reviewers; data extracted independently.
Main Results:
- Analysis of 3 small, older trials revealed no significant reduction in postextubation lobar collapse.
- A significant reduction in reintubation rates was observed in the overall analysis.
- More frequent physiotherapy (1-2 hourly) showed similar effects, while less frequent (4 hourly) trended towards increased collapse and no reintubation benefit.
Conclusions:
- Current evidence is insufficient to establish clear clinical guidelines for active chest physiotherapy during extubation.
- Caution is advised due to small sample sizes, inconsistent results, and limited safety data.
- The applicability of findings to current clinical practice may be restricted.
Background:
This section is under preparation and will be included in the next issue.
Objectives:
To assess the effects of active chest physiotherapy on babies being extubated from mechanical ventilation for neonatal respiratory failure.
Search Strategy:
The standard search strategy for the Neonatal Review Group was used as outlined in the Cochrane Handbook in the Cochrane Library.
Selection Criteria:
All trials utilising random or quasi-random patient allocation, in which active chest physiotherapy was compared with non-active techniques (eg positioning and suction alone) or no intervention in the periextubation period. The methodological quality of each trial was assessed by two independent authors.
Data Collection And Analysis:
Data were extracted independently by two authors. The data were analysed from 3 trials. Subgroup analysis was performed on different treatment frequencies.
Main Results:
In this review of 3 small trials, 2 of which were carried out 10 & 20 years ago, no clear benefit of periextubation active chest physiotherapy can be seen. Active chest physiotherapy did not significantly reduce the rate of postextubation lobar collapse (RR 0.69;0.33,1.45), though a reduction in the use of reintubation was shown in the overall analysis (RR 0.24;0.08,0.75). Subgroup analysis of different treatment frequencies showed the same effect with more frequent treatment (1 & 2 hourly) but showed a trend to increased lobar collapse, and no reduction in the use of reintubation, with less frequent treatment (4 hourly). There is insufficient information to assess other important short and long term outcomes, including adverse effects.
Reviewer'S Conclusions:
The results of this review do not allow development of clear guidelines for clinical practice. Caution is required when interpreting the possible positive effects of chest physiotherapy of a reduction in the use of reintubation and the trend for decreased post-extubation atelectasis as the numbers of babies studied are small, the results are not consistent across trials, data on safety are insufficient, and applicability to current practice may be limited.
More Related Videos

Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:24
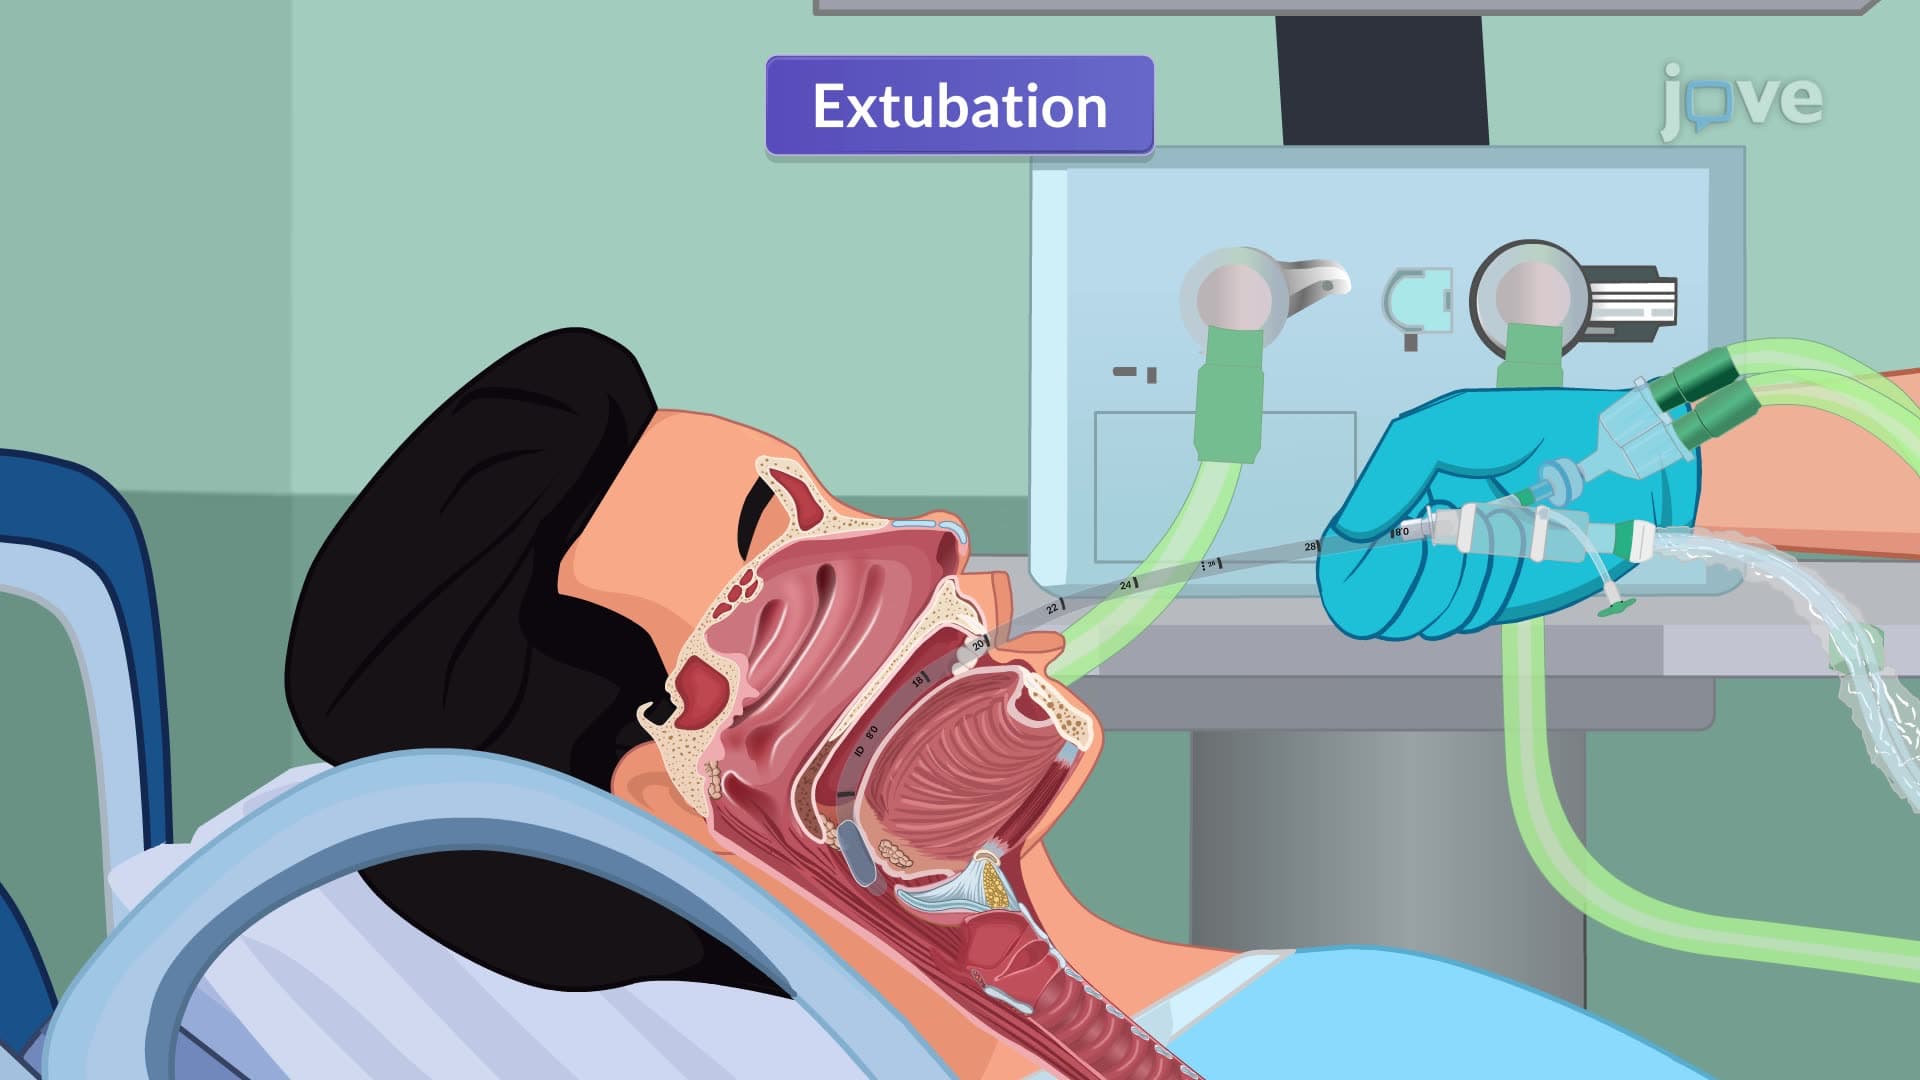
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management