Related Experiment Video
Updated: Oct 16, 2026
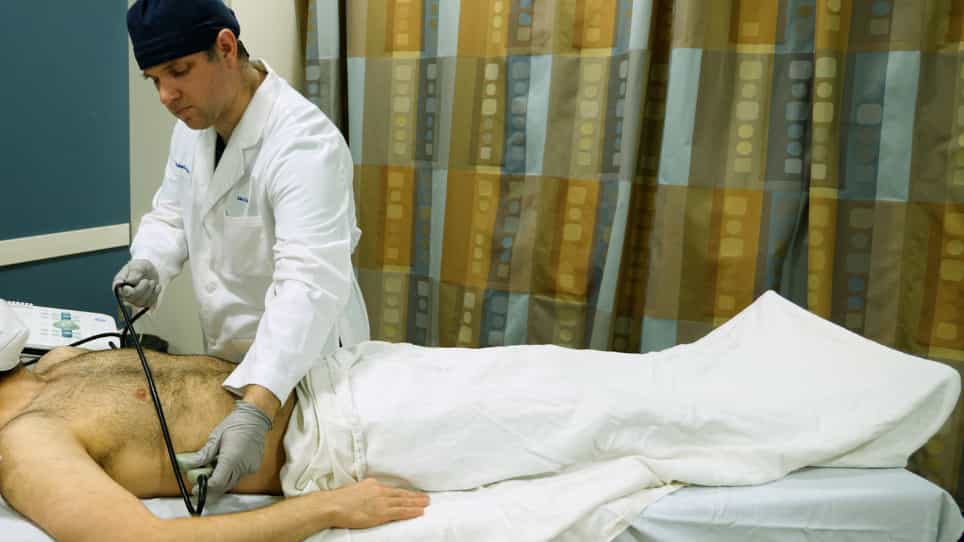
Focused Assessment with Sonography for Trauma (FAST) Exam: Image Acquisition
Published on: September 22, 2023
Isolated intraperitoneal fluid on abdominal computed tomography in children with blunt trauma
J F Holmes1, K L London, W E Brant
1Department of Internal Medicine, University of California, Davis, School of Medicine, Sacramento, USA. jfholmes@ucdavis.edu

Insights
Isolated intraperitoneal fluid (IIF) is found in 8% of pediatric blunt trauma patients. Most patients with IIF and no abdominal tenderness have no significant injuries, indicating a low risk.
Area of Science:
- Pediatric Traumatology
- Emergency Medicine
- Radiology
Background:
- Blunt trauma in children can lead to intra-abdominal injuries (IAIs).
- Abdominal computed tomography (CT) is crucial for diagnosing injuries.
- Isolated intraperitoneal fluid (IIF) on CT requires careful evaluation for associated injuries.
Purpose of the Study:
- To determine the frequency of IIF on abdominal CT in pediatric blunt trauma.
- To assess the association between IIF and clinically identifiable IAIs in children.
Main Methods:
- Prospective observational study of children (<16 years) with blunt torso trauma.
- Abdominal CT scans were interpreted by a radiologist masked to clinical data.
- Intraperitoneal fluid volume was quantified, and organ injury was noted.
Main Results:
- 527 children were enrolled; 17% had intraperitoneal fluid on CT.
- 42 patients (8% of total) had IIF.
- Of those with IIF, 17% had subsequent gastrointestinal injuries identified; most lacked abdominal tenderness.
Conclusions:
- IIF occurs in 8% of pediatric blunt trauma patients undergoing abdominal CT.
- IAIs are identified in 17% of patients with IIF.
- Small amounts of IIF without abdominal tenderness indicate low risk for IAIs.
Objective:
To determine the frequency of isolated intraperitoneal fluid (IIF) on abdominal computed tomography (CT) in pediatric blunt trauma patients and the association between IIF and clinically identifiable intra-abdominal injuries (IAIs) in these patients.
Methods:
The authors conducted a prospective observational study of consecutive children <16 years old with blunt torso trauma who underwent abdominal CT scanning while in the emergency department (ED). All patients were evaluated by a faculty emergency physician who documented the patient's physical examination. All CTs were interpreted by a single faculty radiologist masked to clinical data. The volume of intraperitoneal fluid was quantified (small, moderate, large) and the presence of organ injury visible on CT was noted. Patients were considered to have IIF if the CT demonstrated intraperitoneal fluid and no solid organ injury. Patients with IIF were followed through their hospitalizations or telephoned in one week if discharged home from the ED.
Results:
Five hundred twenty-seven children with blunt trauma were enrolled into the study. The mean age (+/-SD) was 7.4 +/- 4.7 years, and the median pediatric trauma score was 10 (range -2 to 12). Eighty-eight patients (17%; 95% CI = 14% to 20%) had intraperitoneal fluid on CT scan and 42 (48%; 95% CI = 37% to 59%) of these patients had IIF. Of the 42 patients with IIF, five patients (all without abdominal tenderness and with a small amount of IIF on CT scan) were discharged to home from the ED and were well at telephone follow-up; the remaining 37 patients were hospitalized. Of the 42 patients with IIF, 7 patients (17%, 95% CI = 7 to 31%) had IAIs subsequently identified (all gastrointestinal injuries) during their evaluations. Six of the seven patients with IIF and subsequently identified IAIs had abdominal tenderness on examination in the ED. The remaining patient had a decreased level of consciousness.
Conclusions:
Isolated intraperitoneal fluid occurs in 8% of pediatric blunt trauma patients undergoing abdominal CT, and IAIs are subsequently identified in 17% of these patients. Patients with a small amount of IIF on CT who lack abdominal tenderness and have a normal level of consciousness are at low risk for subsequently identified IAIs.
Related Concept Videos
 01:27
Imaging Studies III: Computed Tomography
 01:10
Computed Tomography
The technique was invented in the 1970s and is based on the principle that as X-rays pass through the body, they are absorbed or reflected at different levels. In the technique, a patient lies on a motorized platform while a computerized axial tomography (CAT) scanner rotates...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
Appendicitis
 01:07
Intestinal Obstruction II: Pathophysiology