Related Experiment Video
Updated: Jul 10, 2026
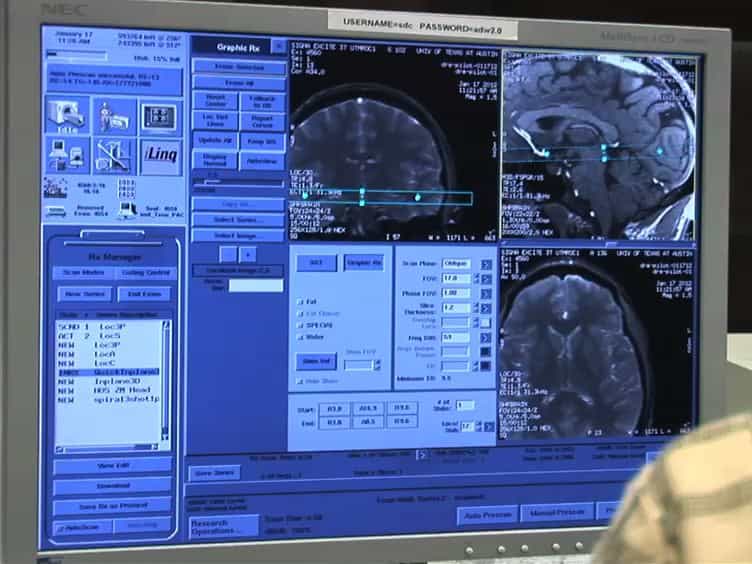
High-resolution Functional Magnetic Resonance Imaging Methods for Human Midbrain
Published on: May 10, 2012
The pedunculopontine nucleus: its role in the genesis of movement disorders
M S Lee1, J O Rinne, C D Marsden
1Department of Neurology, Yongdong Severance Hospital, Yonsei University College of Medicine, Seoul, Korea. myungs56@yumc.yonsei.ac.kr

Abstract:
The pedunculopontine nucleus (PPN) is located in the dorso-lateral part of the ponto-mesencephalic tegmentum. The PPN is composed of two groups of neurons: one containing acetylcholine, and the other containing non-cholinergic neurotransmitters (GABA, glutamate). The PPN is connected reciprocally with the limbic system, the basal ganglia nuclei (globus pallidus, substantia nigra, subthalamic nucleus), and the brainstem reticular formation. The caudally directed corticolimbic-ventral striatal-ventral pallidal-PPN-pontomedullary reticular nuclei-spinal cord pathway seems to be involved in the initiation, acceleration, deceleration, and termination of locomotion. This pathway is under the control of the deep cerebellar and basal ganglia nuclei at the level of the PPN, particularly via potent inputs from the medial globus pallidus, substantia nigra pars reticulata and subthalamic nucleus. The PPN sends profuse ascending cholinergic efferent fibers to almost all the thalamic nuclei, to mediate phasic events in rapid-eye-movement sleep. Experimental evidence suggests that the PPN, along with other brain stem nuclei, is also involved in anti-nociception and startle reactions. In idiopathic Parkinson's disease (IPD) and parkinson plus syndrome, overactive pallidal and nigral inhibitory inputs to the PPN may cause sequential occurrences of PPN hypofunction, decreased excitatory PPN input to the substantia nigra, and aggravation of striatal dopamine deficiency. In addition, neuronal loss in the PPN itself may cause dopamine-resistant parkinsonian deficits, including gait disorders, postural instability and sleep disturbances. In patients with IPD, such deficits may improve after posteroventral pallidotomy, but not after thalamotomy. One of the possible explanations for such differences is that dopamine-resistant parkinsonian deficits are mediated to the PPN by the descending pallido-PPN inhibitory fibers, which leave the pallido-thalamic pathways before they reach the thalamic targets.


Related Concept Videos
 01:30
Diencephalon: Anatomical Regions
 01:27
Diencephalon: Thalamus and Information Relay
 01:17
Cerebellum: Anatomical Regions
Cerebellar Structure
Externally, the cerebellum features a highly convoluted surface with numerous folia (narrow ridges) separated by shallow sulci (grooves). The cerebellum is divided into two hemispheres by a thin median structure known as the vermis. The...
 01:19
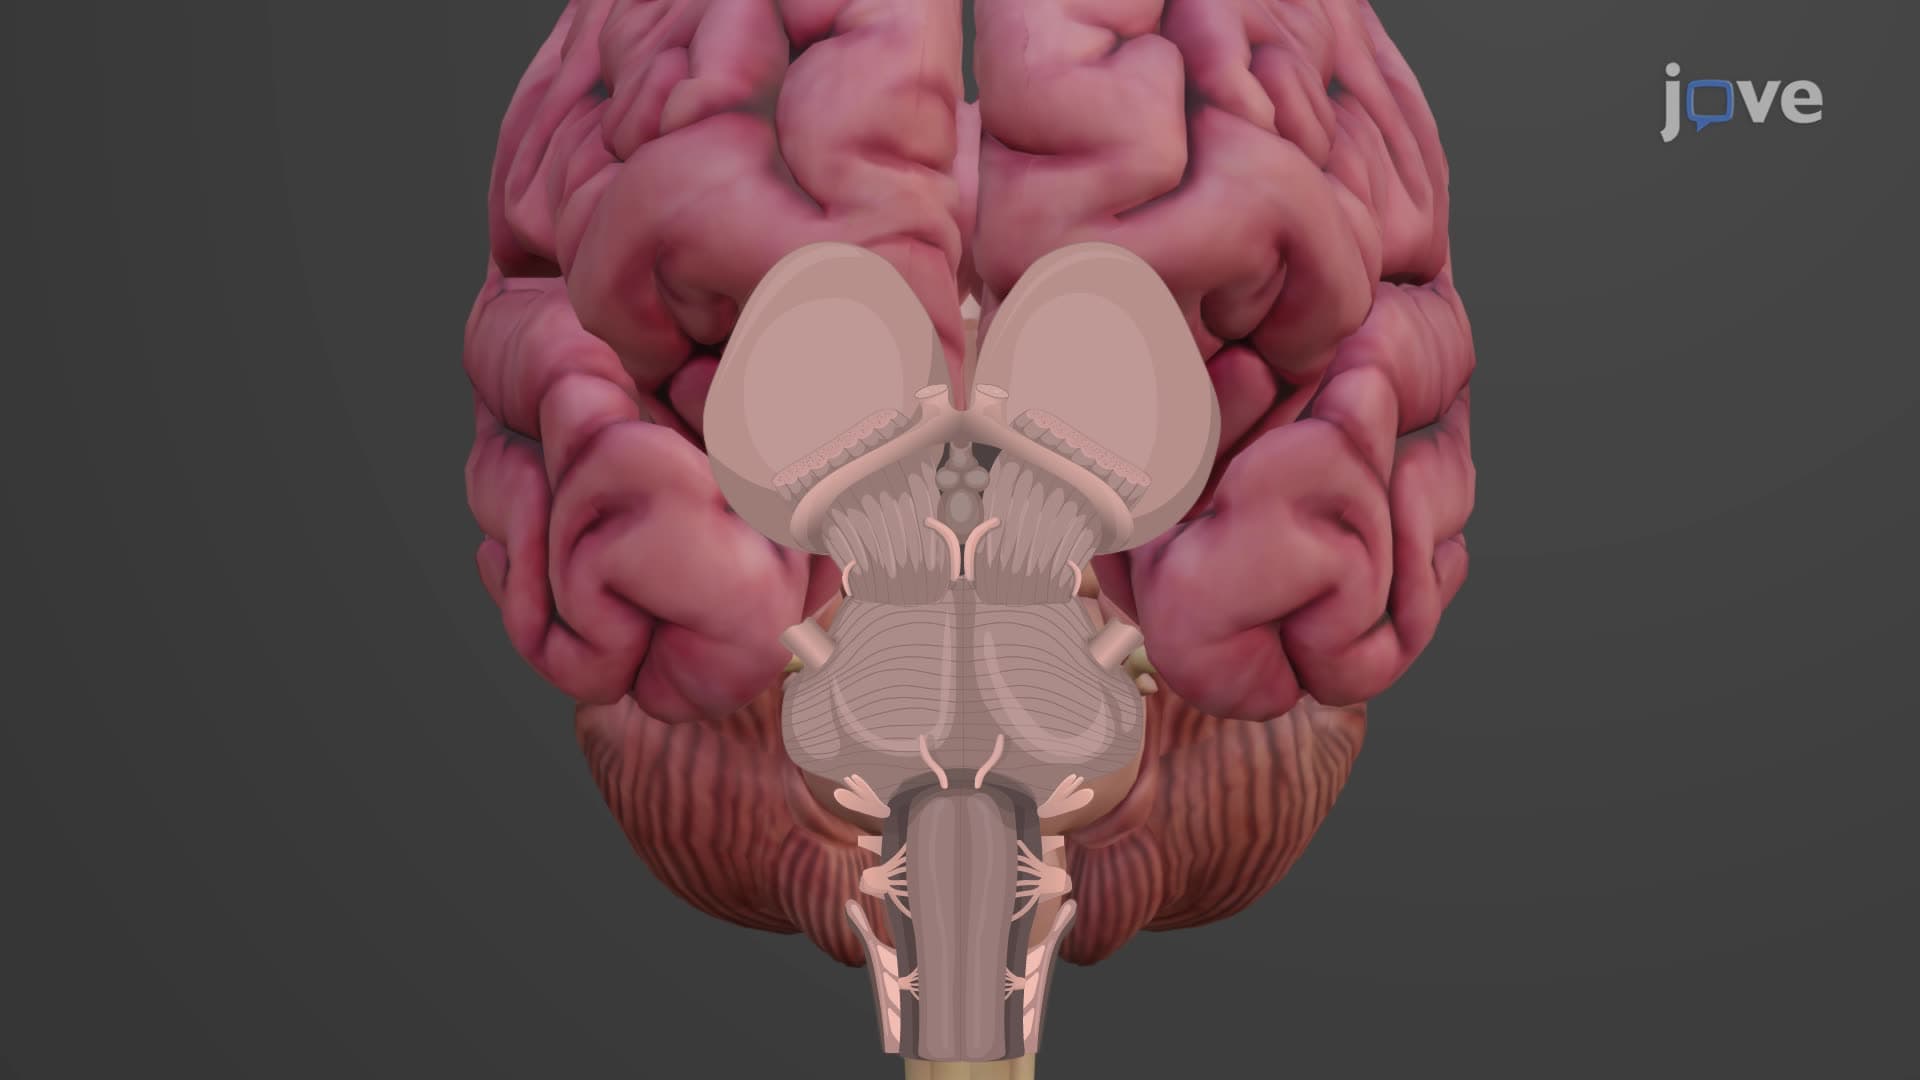
Brainstem
The Midbrain
The midbrain is located beneath the diencephalon and connects the cerebrum with the lower parts of the brain. The cerebral peduncles are prominent midbrain structures that house the...
 01:21
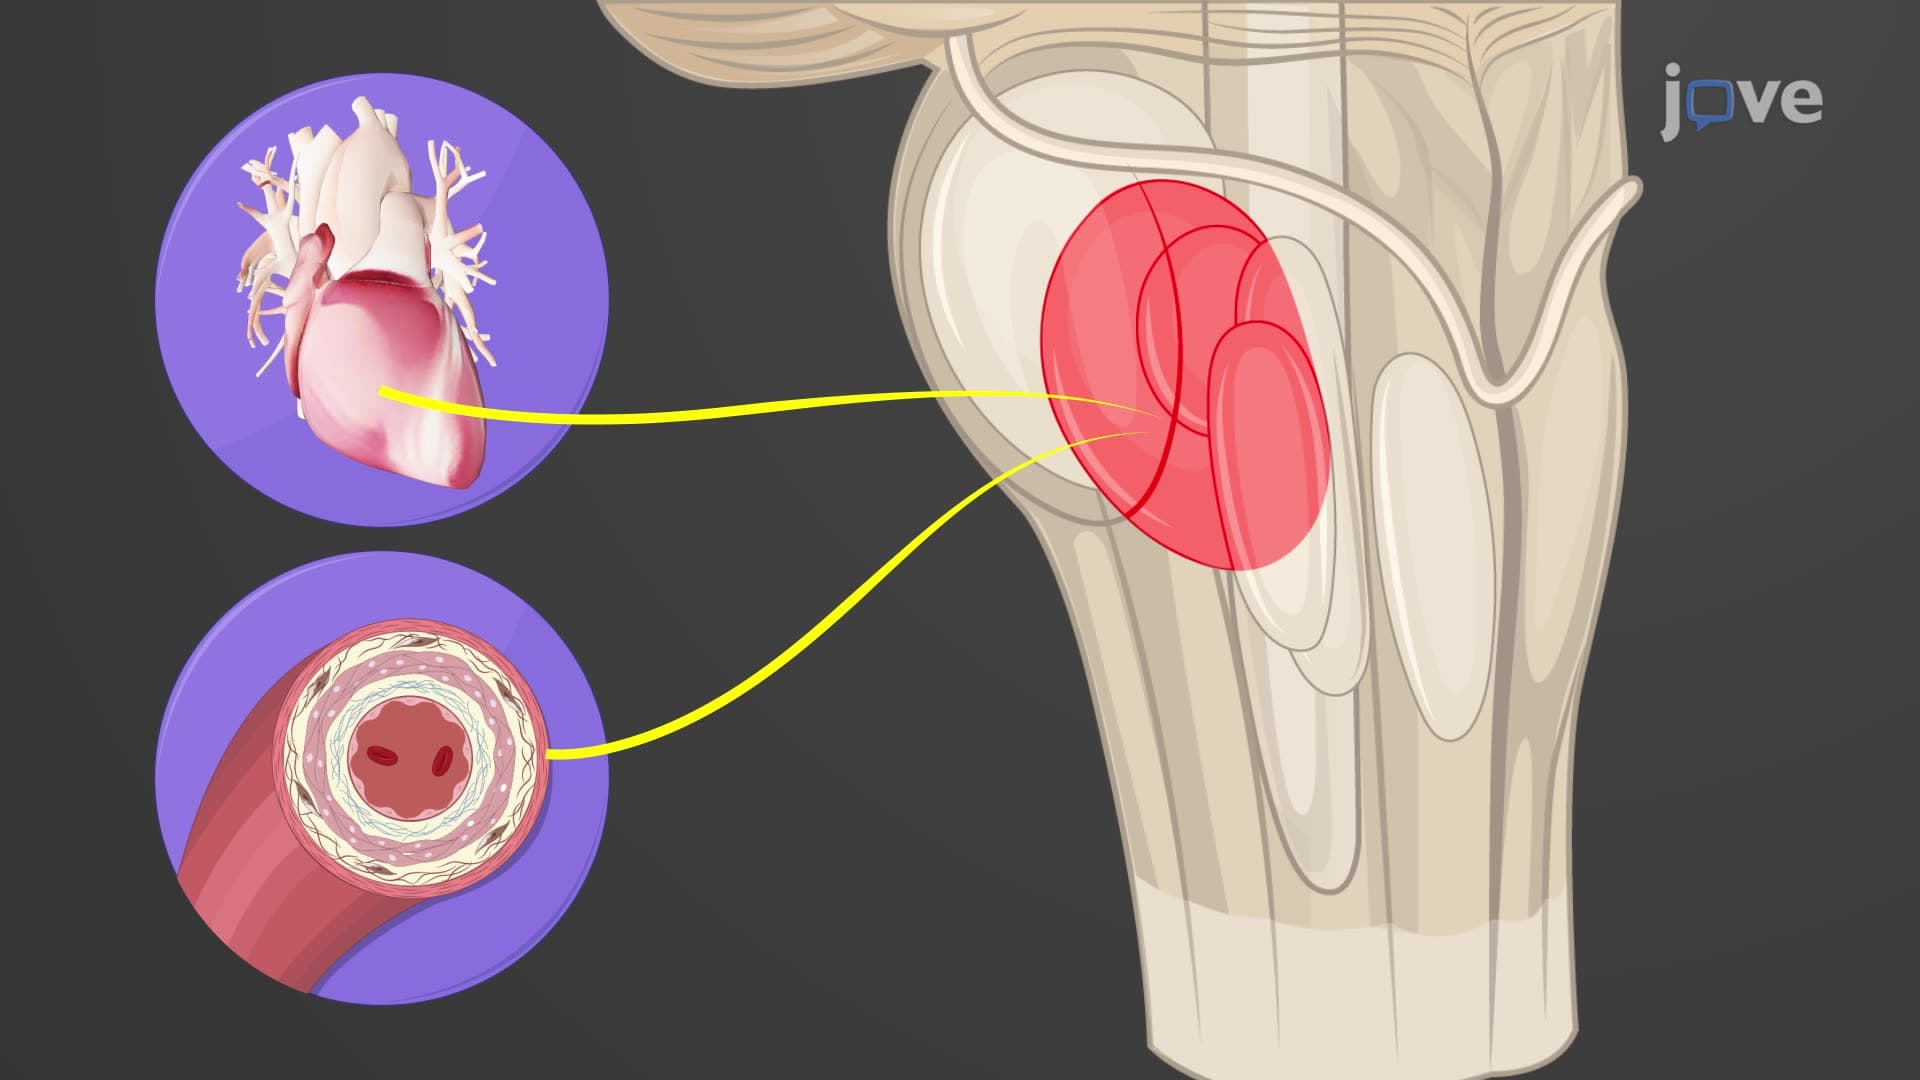
Brainstem: Control Centers of Medulla
Olivary Nucleus
The olivary nucleus, or inferior olivary nucleus, is located within the ventrolateral part of the medulla oblongata. It is primarily involved in motor coordination and motor learning. The olivary nucleus receives input from the spinal cord, cerebellum, and motor...
 01:22
Indirect Motor Pathways
The vestibulospinal tract originates in the vestibular nuclei of the brainstem. The vestibular system detects changes in...