Related Experiment Video
Updated: Oct 13, 2026

Sustained Administration of β-cell Mitogens to Intact Mouse Islets Ex Vivo Using Biodegradable Poly(lactic-co-glycolic acid) Microspheres
Published on: November 5, 2016
[Insulin Lispro (Lys B28, Pro B29) treatment in adolescents and young people with type 1 diabetes]
M J Tuset Castellano1, I Martínez Badás, M Alonso Blanco
1Unidad de Endocrinología Pediátrica, Servicio de Pediatría, Hospital Ramón y Cajal, Madrid.

Background:
The human insulin analogue, Lispro (Lys B28, Pro B29), is more similar to normal pancreatic insulin response to ingestion. Therefore, it could provide an alternative to the classical treatment of type-1 diabetes in childhood. The aim of this study was to analyze the response to insulin treatment with this analogue during 1 year.
Patients And Methods:
In a study group of twenty puberal diabetic patients (nine male and 11 female) with a mean age of 15.6 years (+/- SD) and with diabetes of a mean of 8.3 years (+/- 4.3 SD), classical intensive treatment, a combination of regular insulin (HR) and NPH insulin (Humulin NPH) was substituted for a new treatment with Lispro and NPH insulin in 3-4 doses. All patients had received diabetic education and performed at least four blood glucose tests daily and self monitoring. We analyzed the 6 months prior to the change in treatment (Group A) and the 12 months after the change (Group B). The amount of insulin (u/kg/day), the fast/intermediate insulin ratio in each dose, dietary modifications, the level of metabolic control given by the HbA1C average measured every 2 months, severe hypoglycemia and the patient s level of satisfaction with the new treatment were compared between the two groups.
Results:
The number of daily doses, as well as the daily insulin intake, was the same in both groups (3.7 [+/- 0.6] doses/day; 0.9 [+/- 0.2] u/kg/day). With Lispro treatment the ratio fast/intermediate insulin was reduced. This reduction was statistically significant for the pre-breakfast dose (Classical = 65. 4 +/- 30% vs Lispro = 47.1 +/- 19.6%), and for the pre-lunch dose (Classical = 58.1 +/- 29.3% vs Lispro = 39 +/- 12.8%). Most patients did not need neither mid-morning or mid-afternoon doses. There were no modifications in body mass index. Although metabolic control improved slightly (Classical X A(b) A(1)c = 7 +/- 1.2 vs Lispro X A(b) A(1c) = 6.6 +/- 1.1), the difference was not statistically significant. Three patients had a severe hypoglycemic episode in the first 6 months with the new treatment pattern. All of them were satisfied with the new insulin.
Conclusions:
Intensive therapy with Lispro insulin combined with appropriate doses of basal insulin (NPH) can provide a good alternative in the treatment of diabetic teenagers.
Related Concept Videos
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:25
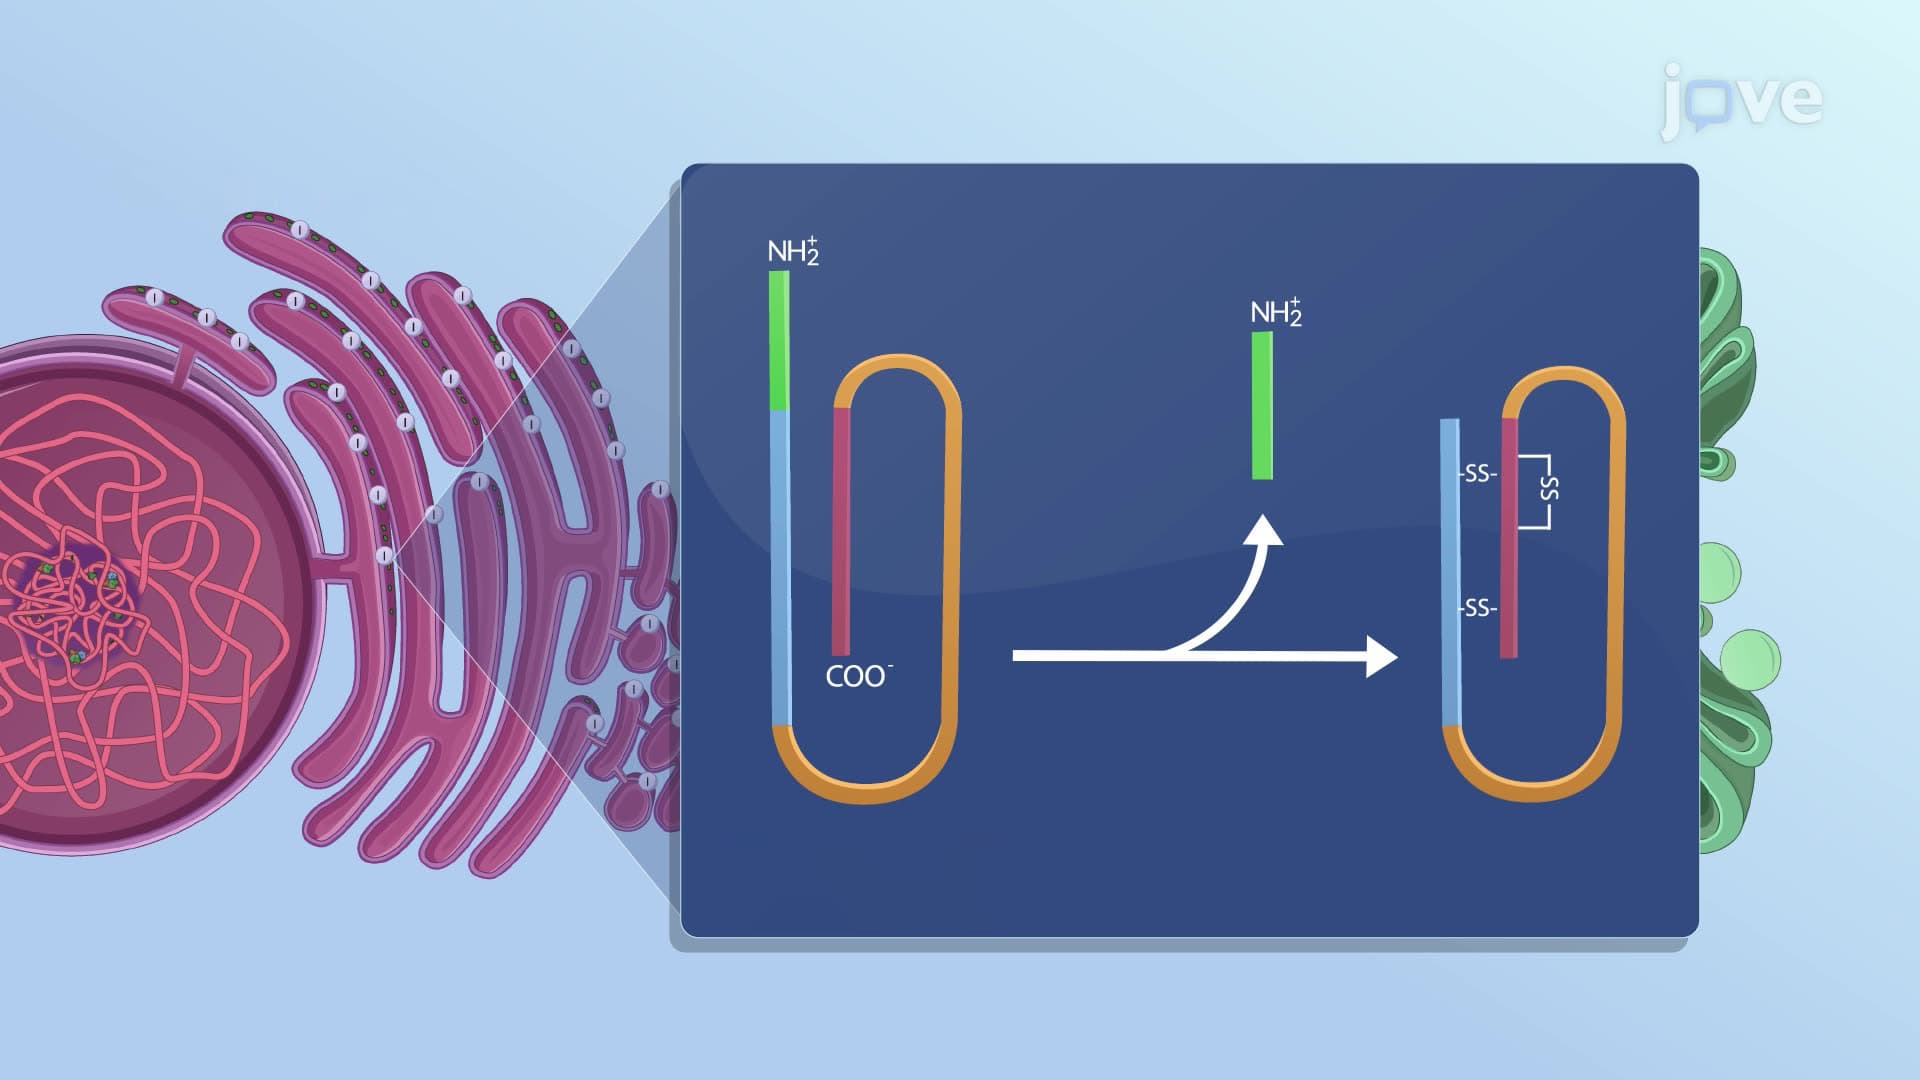
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...