Effects of alpha(1)-adrenoceptor (alpha(1)-AR) antagonists on cell proliferation and apoptosis in the prostate: therapeutic implications in prostatic disease
Related Experiment Video
Updated: Aug 4, 2026
Murine Prostate Micro-dissection and Surgical Castration
Published on: May 11, 2016
N Kyprianou1, J Chon, C M Benning
1Division of Urology, University of Maryland School of Medicine, Baltimore, Maryland 21201, USA. NKyprianou@smail.umaryland.edu

Background:
Benign prostate hyperplasia (BPH) and prostate cancer established that disruption of the molecular mechanisms that regulate apoptosis and cell proliferation among the stromal and epithelial cell populations, may underlie the neoplastic development that characterizes the aging gland. This work examined the effects of selected alpha(1)-adrenoceptor (alpha(1)-AR) antagonists (blockers) on cellular dynamics to determine whether induction of apoptosis or inhibition of proliferation could contribute to the overall clinical profile.
Methods:
Our efforts were focused on investigating whether alpha(1)-AR antagonists of two different chemical classes affect prostate pathophysiology via mechanisms other than smooth muscle contraction. In in vitro experiments, the two clinically used quinazoline alpha(1)-adrenoceptor antagonists terazosin and doxazosin and the chemically-distinct sulphonamide, tamsulosin, were examined for effects on prostatic tumor growth, by inhibiting cell proliferation and'or inducing apoptosis.
Results:
Our findings suggest that alpha(1)-AR antagonists, terazosin and doxazosin, suppress prostatic growth by inducing apoptosis in a dose-dependent manner and without affecting cell proliferation. Tamsulosin exerted no effect on prostate cancer cell growth. The apoptotic effect of terazosin and doxazosin appears to be independent of the alpha(1)-adrenoceptor block.
Conclusions:
Taken together, our findings demonstrate the ability of the quinazoline alpha-blockers, terazosin and doxazosin, but not the sulphonamide, tamsulosin, to suppress prostate growth by inducing apoptosis among the epithelial cells in the benign and malignant prostate. These studies underwrite the durability of the response seen in long-term studies with terazosin, and suggest the potential of this drug in the treatment of prostate carcinoma.
Insights
Alpha(1)-adrenoceptor antagonists terazosin and doxazosin induce apoptosis, suppressing benign prostate hyperplasia and prostate cancer growth. Tamsulosin showed no effect on prostate cancer cell growth.
Area of Science:
- Urology
- Pharmacology
- Oncology
Background:
- Disruption of apoptosis and cell proliferation mechanisms contributes to neoplastic development in the aging prostate.
- Benign prostate hyperplasia (BPH) and prostate cancer involve dysregulated cellular dynamics.
Purpose of the Study:
- To investigate the effects of alpha(1)-adrenoceptor (alpha(1)-AR) antagonists on prostate cellular dynamics beyond smooth muscle relaxation.
- To determine if inducing apoptosis or inhibiting proliferation by alpha(1)-AR antagonists contributes to their clinical efficacy.
Main Methods:
- In vitro examination of quinazoline (terazosin, doxazosin) and sulphonamide (tamsulosin) alpha(1)-AR antagonists.
- Assessing effects on prostatic tumor growth, cell proliferation, and apoptosis.
Main Results:
- Terazosin and doxazosin dose-dependently suppressed prostate growth by inducing apoptosis, independent of alpha(1)-AR block.
- Tamsulosin did not affect prostate cancer cell growth or proliferation.
Conclusions:
- Quinazoline alpha-blockers (terazosin, doxazosin) induce apoptosis in benign and malignant prostate epithelial cells, suppressing growth.
- These findings support the long-term efficacy of terazosin and suggest its potential in treating prostate carcinoma.
More Related Videos
 07:25
A Bioluminescent and Fluorescent Orthotopic Syngeneic Murine Model of Androgen-dependent and Castration-resistant Prostate Cancer
Published on: March 6, 2018
 09:49
Isolation of Adipose Derived Regenerative Cells for the Treatment of Erectile Dysfunction Following Radical Prostatectomy
Published on: December 28, 2021
Related Concept Videos
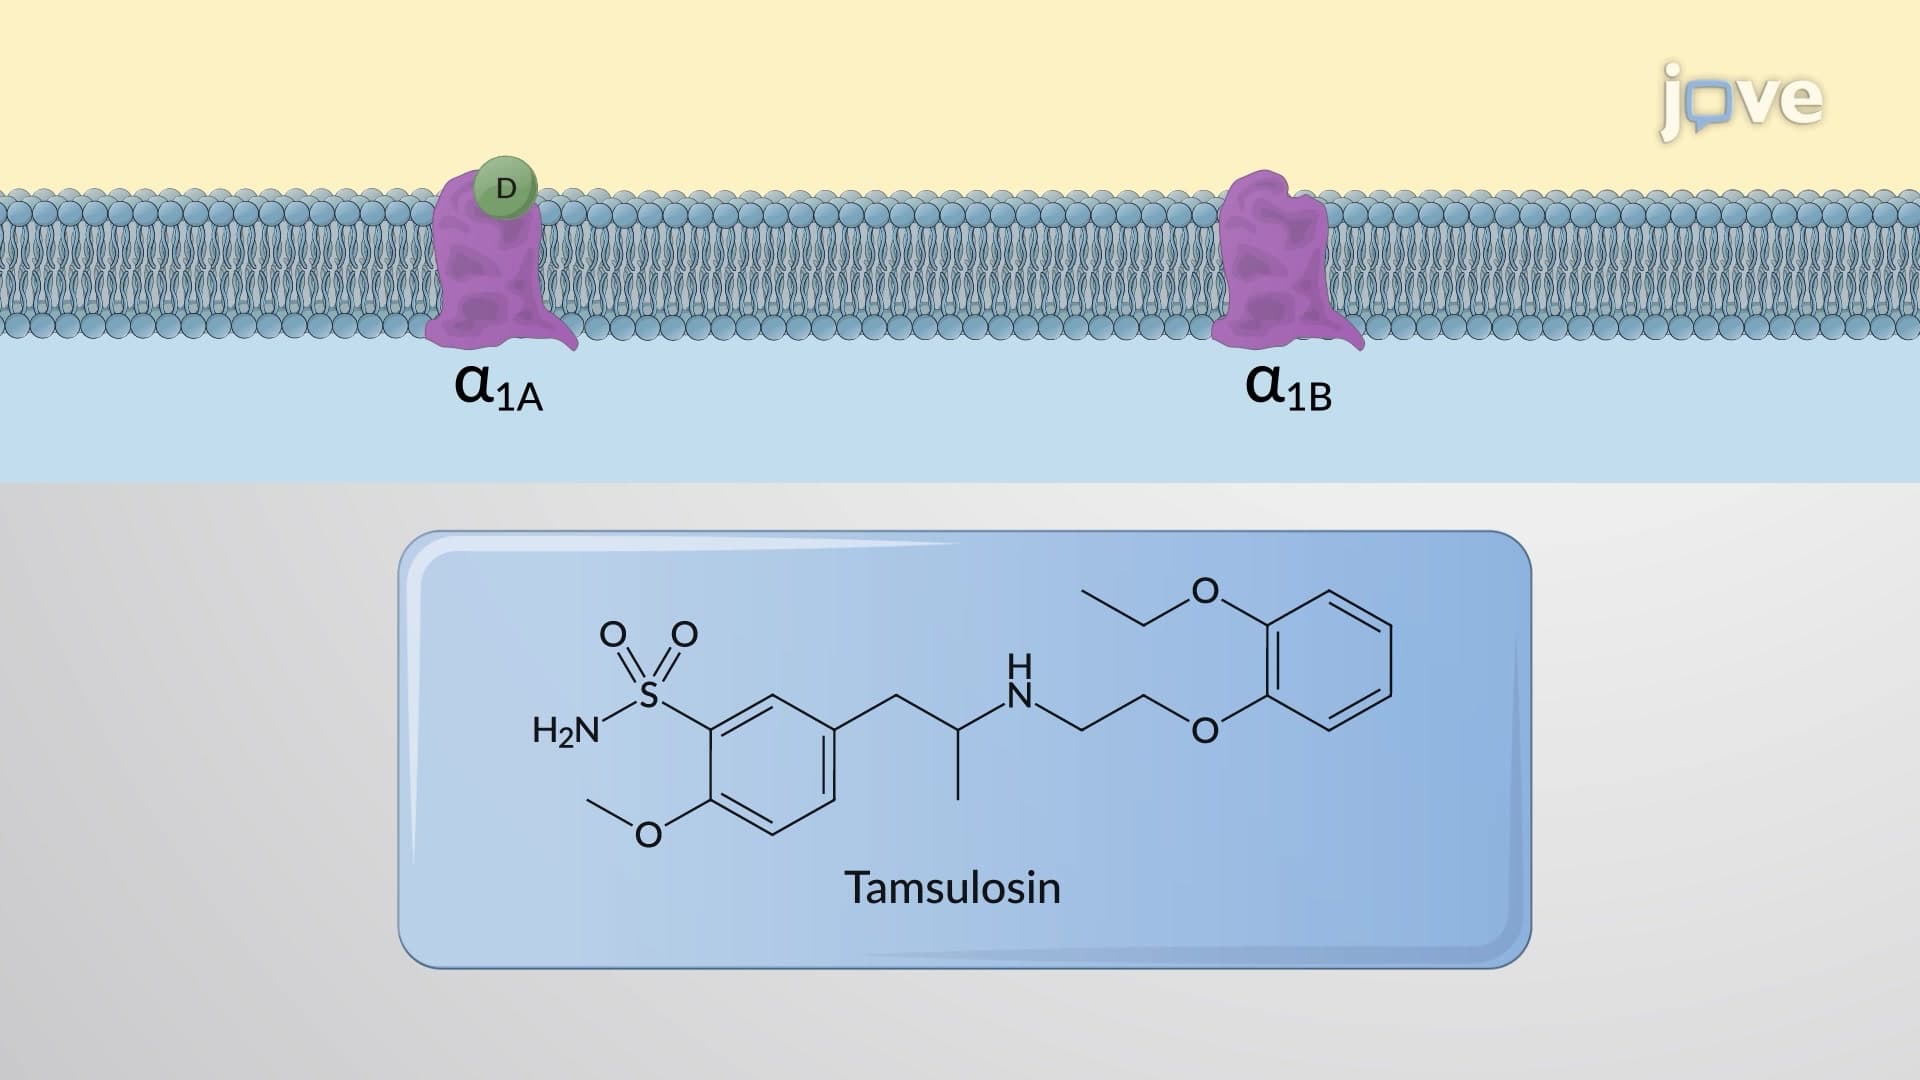 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:17
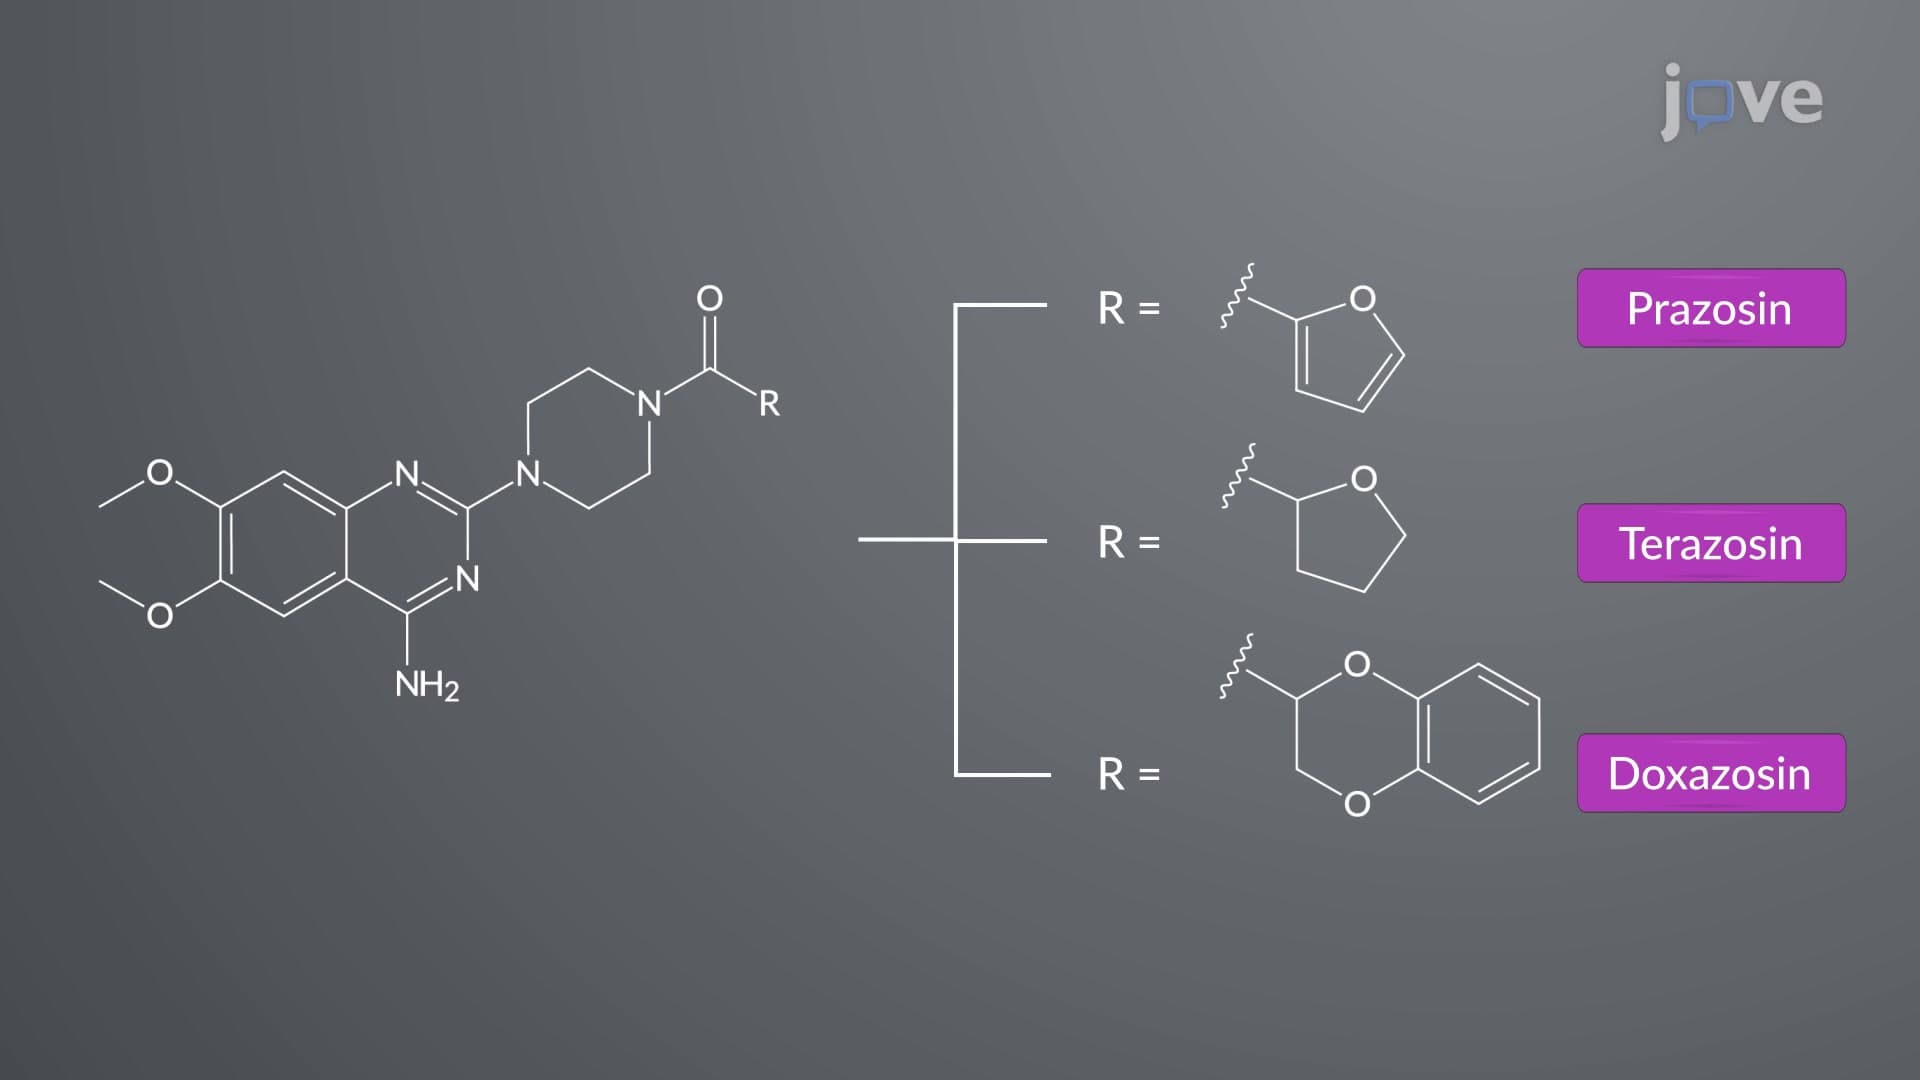
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System