Related Experiment Video
Updated: Jul 19, 2026

Infant Auditory Processing and Event-related Brain Oscillations
Published on: July 1, 2015
Identification of neonatal hearing impairment: auditory brain stem responses in the perinatal period
Y S Sininger1, B Cone-Wesson, R C Folsom
1Multicenter Consortium on Identification of Neonatal Hearing Impairment, Seattle, Washington, USA.

Insights
Automated auditory brain stem response (ABR) is a reliable method for newborn hearing screening, accurately assessing auditory status in most infants. Factors like infant state and electrode impedance can influence results, but the technique proves effective for rapid evaluation.
Area of Science:
- Neonatal audiology
- Neuroscience
- Public health
Background:
- Newborn hearing screening is crucial for early detection of hearing loss.
- Auditory Brainstem Response (ABR) is a key diagnostic tool for assessing auditory function in infants.
Purpose of the Study:
- To detail the auditory brain stem response (ABR) system and methods for newborn hearing screening.
- To analyze how recording and infant factors influence ABR screening outcomes.
Main Methods:
- An automated ABR protocol was used on 7,179 infants (NICU and well-baby nursery).
- Two-channel recordings were obtained using click stimuli at varying dB nHL levels.
- Criteria for response included F(SP) > or =3.1 and tester judgment, with a maximum of 6144 sweeps per test.
Main Results:
- Over 99% of infants completed the ABR protocol; >90% passed screening.
- Factors influencing ABR results included noise levels, infant state, electrode impedance, and stimulus level.
- The automated ABR test averaged under 8 minutes for both ears at 30 dB nHL.
Conclusions:
- Automated ABR with a 30 dB nHL click stimulus is a reliable and rapid method for newborn hearing assessment.
- Infant state, electrode factors, testing site, and risk status can affect ABR results.
- ABRs were reliably recorded in most infants, demonstrating the technique's efficacy in perinatal settings.
Objectives:
1) To describe the auditory brain stem response (ABR) measurement system and optimized methods used for study of newborn hearing screening. 2) To determine how recording and infant factors related to the screening, using well-defined, specific ABR outcome measures.
Design:
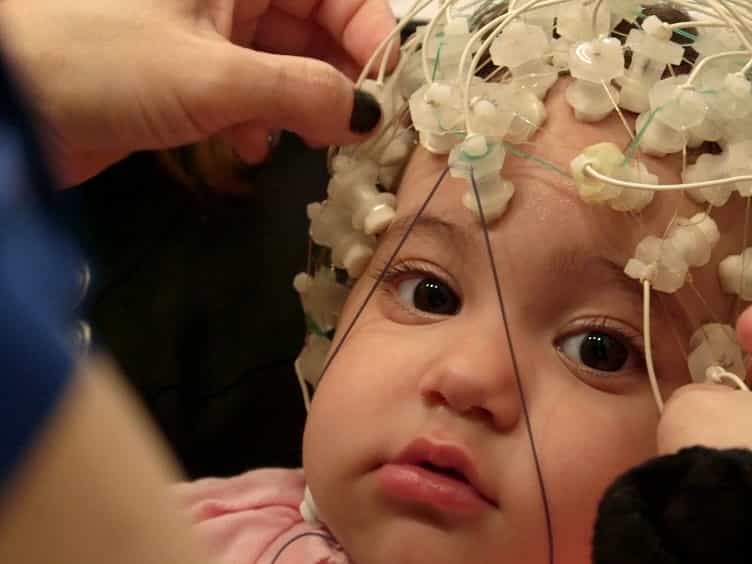
Seven thousand one hundred seventy-nine infants, 4478 from the neonatal intensive care unit (NICU) and the remaining from the well-baby nursery, were evaluated with an automated ABR protocol in each ear. Two channel recordings were obtained (vertex to mastoid or channel A and vertex to nape of neck or channel B) in response to click stimuli of 30 and 69 dB nHL in all infants as well as 50 dB nHL in infants who did not meet criteria for response at 30 dB. Criteria for response included F(SP) > or =3.1 and a tester-judgment of response. Criteria could be met in the first or repeat test with a maximum of 6144 accepted sweeps per test.
Results:
More than 99% of infants could complete the ABR protocol. More than 90% of NICU and well-baby nursery infants "passed" given the strict criteria for response, whereas 86% of those with high risk factors met criterion for ABR response detection. The number of infants who did not meet ABR response criteria in one or both ears was systematically related to stimulus level with the largest group not meeting criteria at 30 dB followed by 50 and 69 dB nHL. Meeting criteria on the ABR was positively correlated with the amplitude of wave V, with low noise and low electrode impedance. Factors that predicted how many sweeps would be needed to reach criterion F(SP) included noise level of the test site, state of the baby (for example, quiet sleep versus crying), recording noise, electrode impedance and response latency. Channel A (vertex to mastoid) reached criterion more often than channel B (vertex to nape of neck) due to higher noise in channel B. Average total test time for 30 dB nHL screening in both ears was under 8 minutes. Well babies with risk factors took slightly longer to evaluate than other groups with this automated ABR procedure and have higher noise levels.
Conclusions:
ABR implemented with an automated detection algorithm using a 30 dB nHL click stimulus is reliable technique for rapid assessment of auditory status in newborns. Factors other than hearing loss that influenced the test result include infant state, electrode location and impedance, testing site, and infant risk status. Even so, ABRs were reliably recorded in the vast majority of babies under circumstances in which most babies are found in the perinatal period.