Related Experiment Video
Updated: Aug 15, 2026


Less-Invasive Technique for Non-stabilized Mandibular Fracture in Mouse Models
Published on: September 27, 2024
[Fractures of the coronoid process]
N Bousselmame1, M Boussouga, S Bouabid
1Service de traumatologie orthopédie I, hôpital militaire Mohamed V, Rabat, Maroc.

Introduction:
A retrospective study has been made of a series of 22 cases, and the classification and treatment of fractures of the coronoid process of the ulna have been discussed.
Material, Methods And Results:
A report has been made of 22 cases of coronoid process fracture (18 males and four females). The mean age was 26 years (range: 19-47 years). According to the Reagan and Morrey Classification, there were 11 type I (avulsion of the tip of the bone), seven type II (a fragment of less than 50% that was detatched from the coronoid process), and four type III cases (a fragment of more than 50% that was detatched from the coronoid process). Elbow dislocation was present in 16 cases, and a radial head fracture was associated in four cases. All type I fractures were treated by immobilization of the elbow in a plaster cast for ten to 15 days, with eight excellent and three good results. In type II fractures, open reduction, internal fixation with antero-posterior lag-screw and early post-operative movement in three patients gave better results than immobilization for three weeks, which was the procedure used in four cases (after transosseous reinsertion in one case). In type III fractures, good results were obtained following open reduction and internal fixation with antero-posterior lag-screw in three patients. The result was average in the fourth case, with immobilization for four weeks.
Conclusion:
The Reagan and Morrey classification is most useful for the classification of coronoid process fractures. If there is no comminution of the detatched fragment, open reduction and internal fixation with antero-posterior lag-screw is the treatment of choice in type I and II fractures. In type I fractures, immobilization for about two weeks gives good results.

Related Concept Videos
 01:27
Growth of Cartilage and Bone Tissue
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:27
Cranial Bones: Lateral View
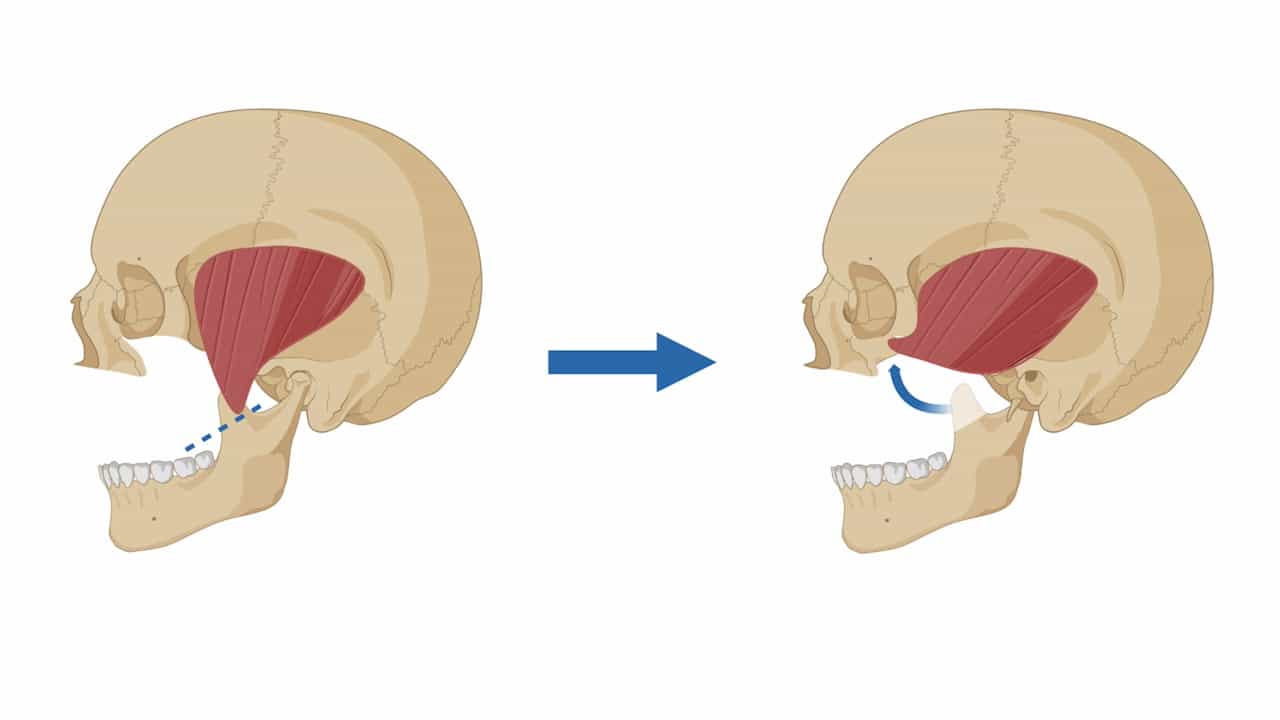
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:15
Bones of the Upper Limb: Ulna
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...