Related Experiment Video
Updated: Aug 4, 2026
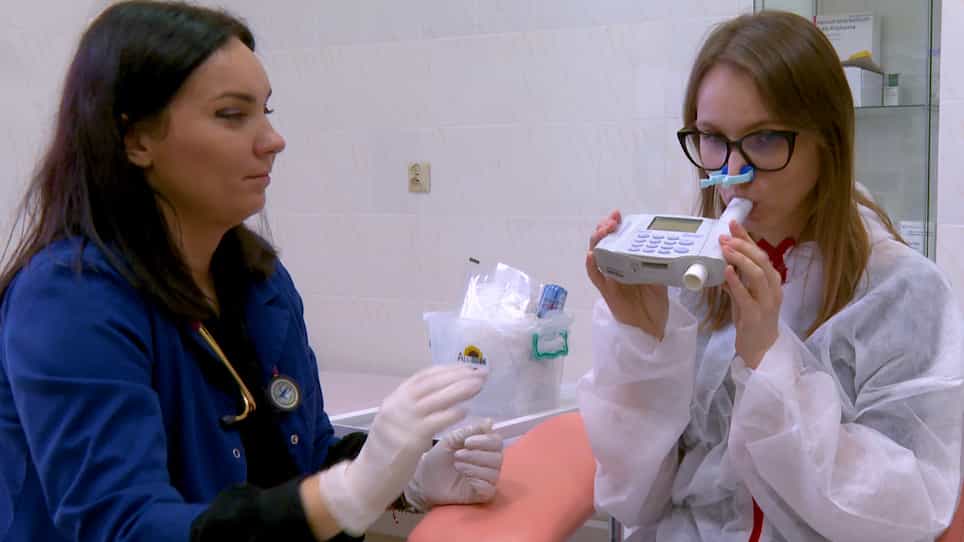

Symptom Assessment of Patients with Allergic Rhinitis Using an Allergen Exposure Chamber
Published on: March 3, 2023
[Can we improve the therapeutic management of allergic rhinitis in primary care?]
J F Menárguez Puche1, M D Lorenzo Zapata, M I Sánchez López
1Centro de Salud Virgen de la Consolación, Molina de Segura, Murcia. palcantaram@papps.org

Objective:
To evaluate improvement in therapeutic management of allergic rhinitis.
Design:
Study of level of quality (longitudinal, prospective, intervention).
Setting:
Primary care.
Patients And Others Participants:
First evaluation (second quarter of 1995): 73 out of 305 patients were sampled (confidence 5%, accuracy 10%). Second evaluation (second quarter of 1996). Sample of 51 patients from a total of 210.
Interventions:
Explicit criteria and standard procedure, based on consensus, for rhinitis treatment and an overall indicator of the general quality of rhinitis management were analysed. Criterion 1 (C1): correctly scaled treatment; criterion 2 (C2): initial treatment of choice with inhaled corticoids; criterion 3 (C3): correct use of oral corticoids or immunotherapy; criterion 4 (C4): coadjutant therapy according to predominant symptoms. Corrective measures: ongoing training and routine use of guide to practice.
Statistics:
index of compliance with criteria, Chi squared and Fisher's Z tests of a tail to compare both evaluations.
Measurements And Main Results:
First evaluation: index of compliance with C1 = 59% (CI +/- 11), C2 = 41% (CI +/- 11), C3 = 90% (CI +/- 6) and C4 = 83% (CI +/- 8). Criteria and summary indicator obtained better results in patients attended by allergists. Second evaluation with overall improvement: C1 = 68.6% (CI +/- 13), C2 = 57% (CI +/- 13), C3 = 94% (CI +/- 6), C4 = 98% (CI +/- 3). Significant differences for C4 and C2 (p < 0.05). Overall quality and quality of criteria improved for patients attended in our environment. The summary indicator went up from 35.6% to 57% (p = 0.019), with the quality levels (C1-C4) becoming the same as those of the patients with allergy attended and with significant differences in the first evaluation disappearing.
Conclusions:
Ongoing training and routine use of guides to practice enables the therapeutic management of allergic rhinitis in primary care to be improved.

Related Concept Videos
 01:16
Drugs Used in Upper Respiratory Disorders: Overview
Antihistamines (e.g., Benadryl) block histamines from binding. Histamines are chemicals released during an allergic reaction in the body. As a...
 01:17
Drugs Used in Lower Respiratory Disorders: Overview
Bronchodilators, the first step of respiration enhancement, come in various forms, each with its own mechanism...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:30
Asthma-IV: Nursing Management
First, in...