Related Experiment Video
Updated: Oct 8, 2026


Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
[Measurement of the Fowler dead space in patients with pulmonary emphysema using C18O2]

Abstract:
In patients with lung emphysema, changes in lung volumes as well as changes in airway resistance are well known. The change in airway resistance is caused by obstruction of central airways, which is supposed to reduce the respiratory dead space. Until now, it was not possible to measure the respiratory dead space in patients with lung emphysema using the method of Fowler [2], because in this method distinction of the three phases of an inert gas expirogram is essential. While this distinction is easy in healthy subjects (fig. 1; expirogram 3), the separation of the three phases in patients with lung emphysema is not possible due to gradual transition of phase II into phase III in these patients (fig. 1; expirogram 2). The use of C18O2 as tracer gas allows to separate phase II and phase III even if the patients have severe emphysema (fig. 1; expirogram 1). CO2 labeled with the stable oxygen isotope 18O (C18O2) is completely taken up in the gas exchanging region of the lung, but not from the conducting airways. Therefore C18O2 is only expired from the dead space of the lung, but not from the alveolar region. Hence, C18O2 allows exact measurement of the respiratory dead space in patients with lung emphysema. 21 healthy nonsmoking subjects and 29 patients with clinical signs of lung emphysema participated in this study. There was a good correlation between respiratory dead space, measured by the use of Ar-gas and C18O2-gas in healthy subjects (fig. 2). This indicates, that the use of C18O2 is a valid method to measure the functional dead space. As expected, there was also a correlation between the airway resistance and respiratory dead space in patients with lung emphysema (fig. 3), but not in healty subjects. There was no significant difference of the mean values of the respiratory dead space between these two groups (223 +/- 43 ml in healthy subjects vs. 227 +/- 52 ml in patients), even though there were large differences in airway resistance (0.20 +/- 0.10 kPa/l/s vs. 0.49 +/- 0.27 kPa/l/s). This may be due to a loss of alveolar function in the area of the terminal bronchioli, which is typical for emphysematous patients. This entails a shift of functional dead space towards lung periphery and therefore causes an increase of the volume of functional dead space. But this enlargement may be compensated by the volume reduction, caused by the airway obstruction. Hence, these two oppositional mechanisms may result in only minimal change of dead space volume.
More Related Videos


Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:15
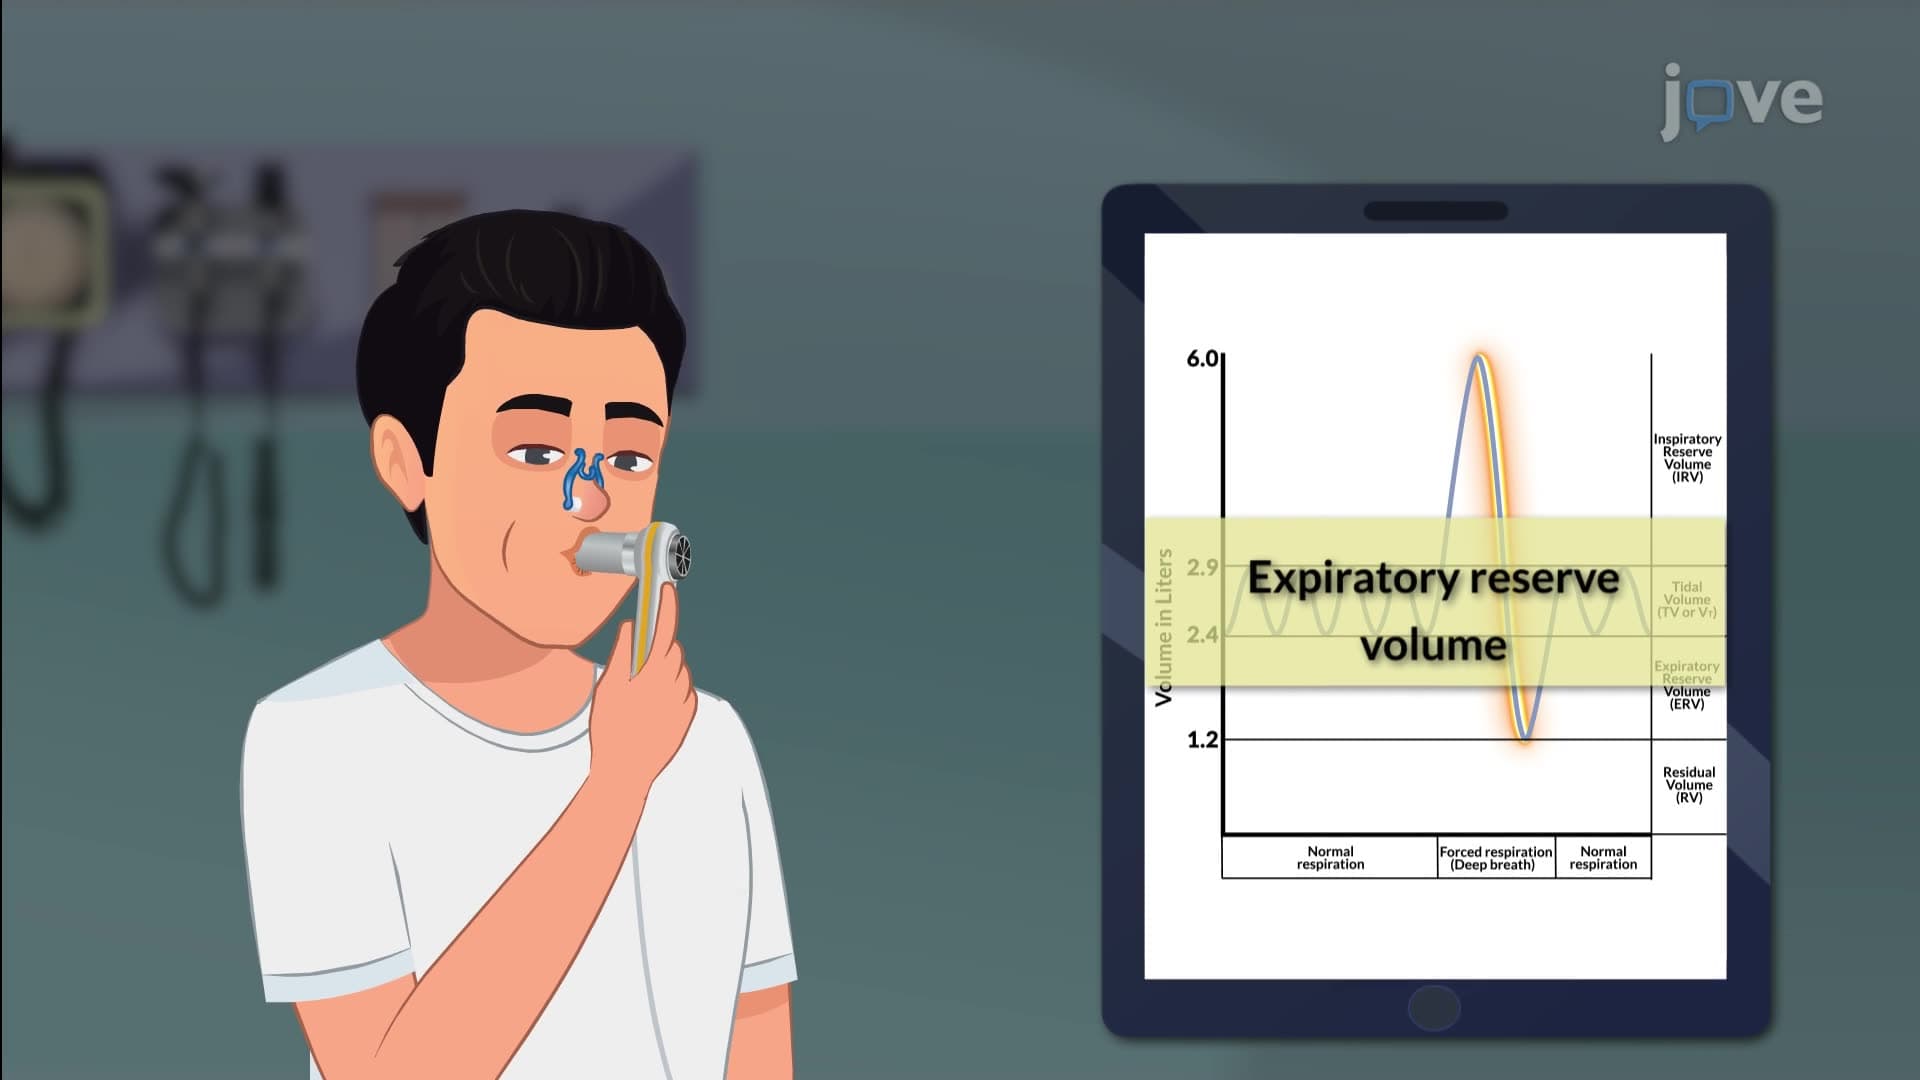
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is important.
 01:22
Respiratory Volumes and Capacities
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:26
Respiratory Volumes and Capacities I