Cranial irradiation and central hypothyroidism
Related Experiment Video
Updated: Oct 8, 2026
Functional Interrogation of Adult Hypothalamic Neurogenesis with Focal Radiological Inhibition
Published on: November 14, 2013
1Children's Hospital Medical Center, Division of Endocrinology, 3333 Burnet Avenue, Cincinnati, OH 45229-3039, USA. susan.rose@chmcc.org

Abstract:
Cranial irradiation causes thyrotropin (TSH)-releasing hormone (TRH) secretory abnormalities. TRH deficiency leads to abnormal glycosylation of TSH alpha and beta subunits and loss of the normal circadian pattern of TSH secretion (low in the afternoon, a surge in the evening, higher at night). This disruption results in either mixed hypothyroidism (raised TSH with abnormal secretory kinetics) or central hypothyroidism (abnormal secretory kinetics without raised TSH). Although primary hypothyroidism is more common in the general population and cancer survivors, the cumulative incidence of central and mixed hypothyroidism is high during the ten years after cranial irradiation. Monitoring for decline in free thyroxine (FT(4)) and rise in serum TSH, and early recognition using TSH surge and TRH tests, are clinically valuable. Early thyroid hormone replacement therapy to achieve serum FT(4) in the upper half of the normal range is crucial for maintaining optimal health and growth in cancer survivors.
Related Concept Videos
 01:23
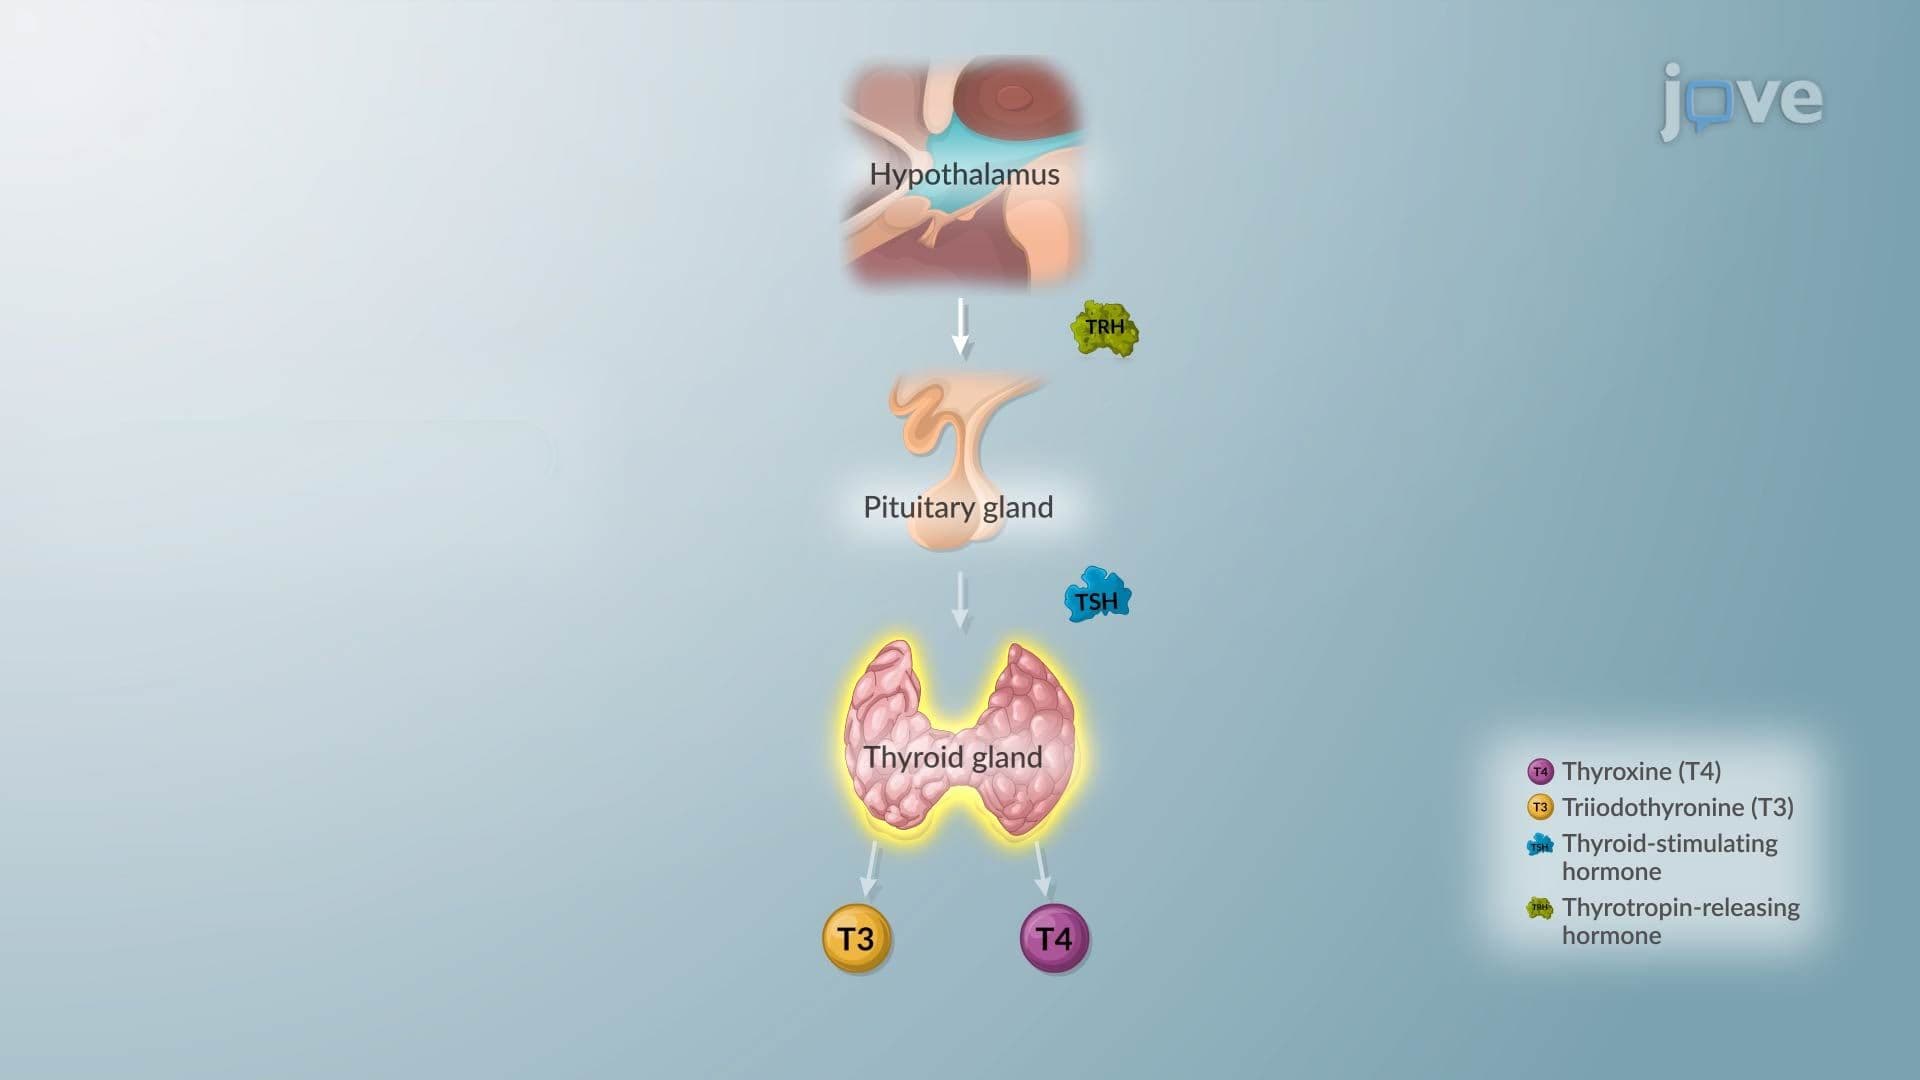
Hypothyroidism II: Pathophysiology
 01:25
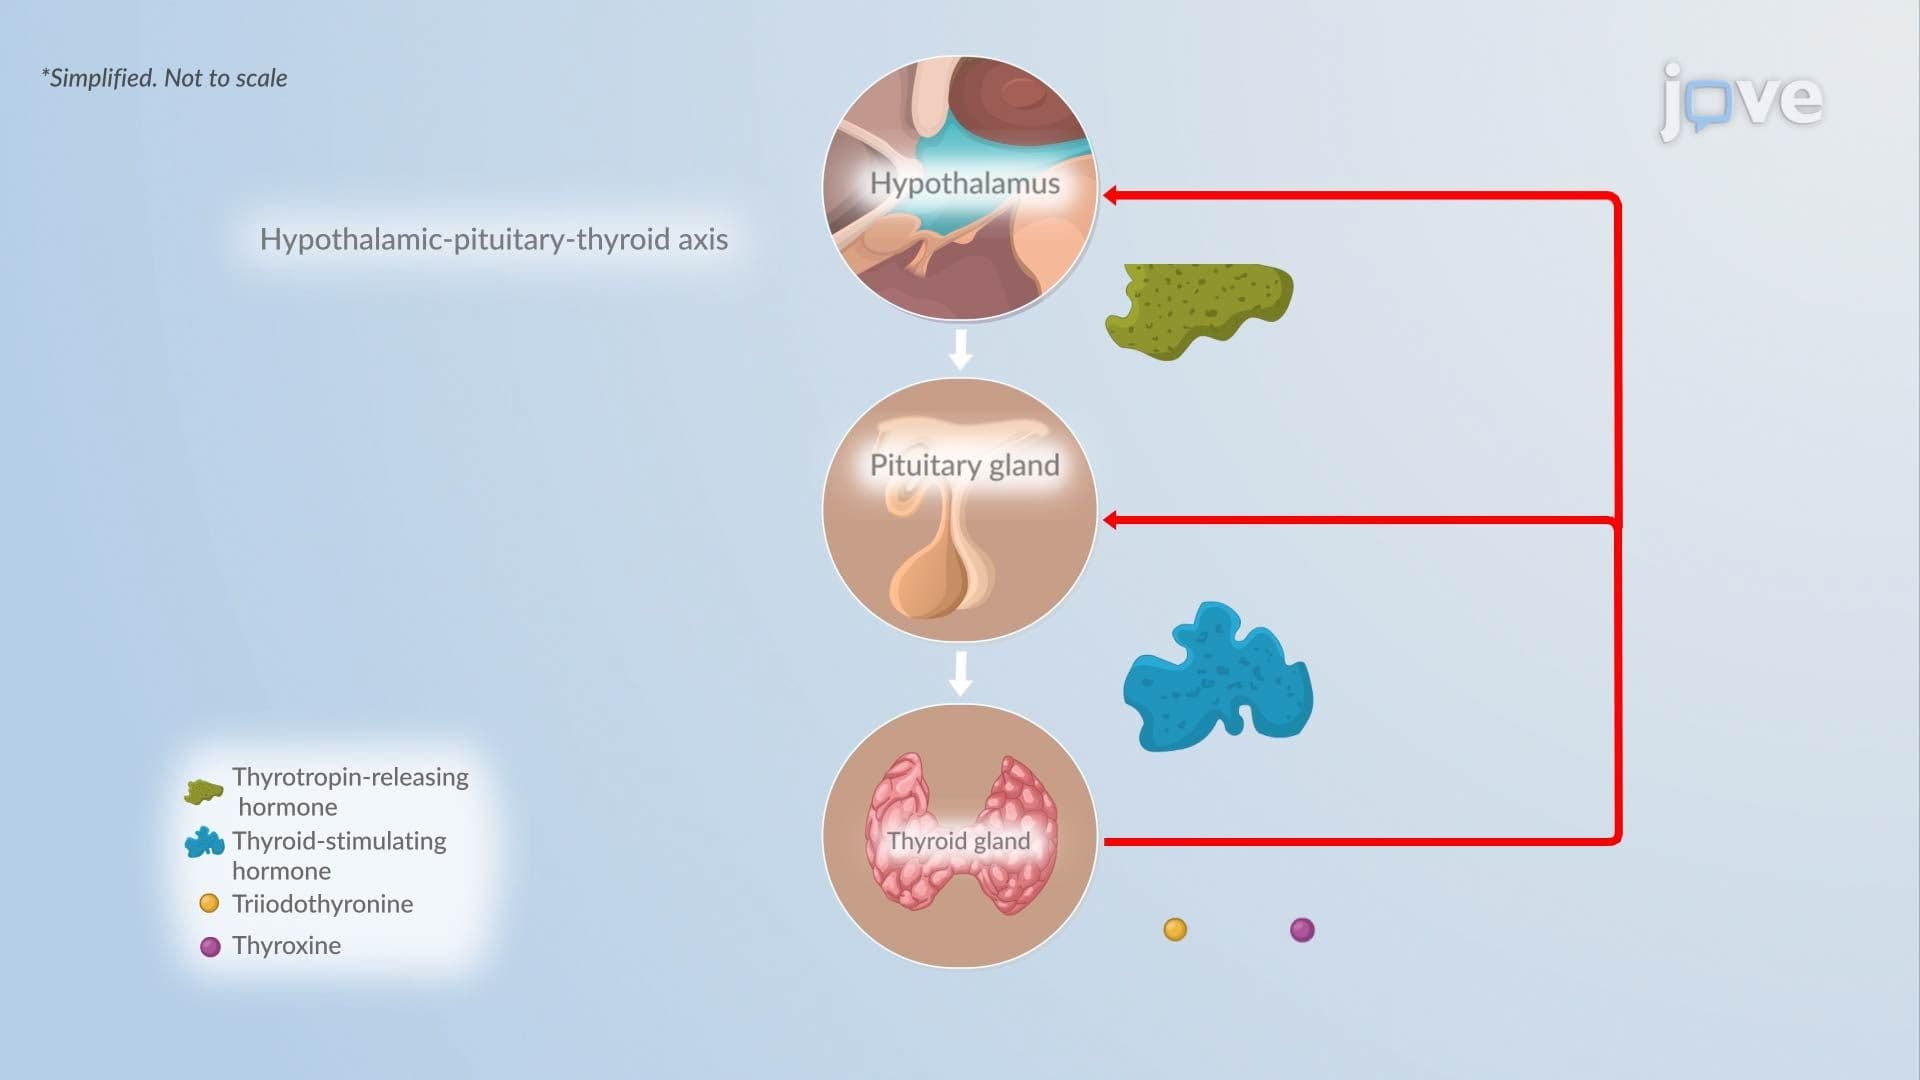
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:27
Goiter