Downregulation of K(+) channel genes expression in type I diabetic cardiomyopathy

D Qin1, B Huang, L Deng

  • 1Department of Veterans Affairs, New York Harbor Healthcare System, Brooklyn Campus, Brooklyn, New York, 11209, USA.

Related Concept Videos

Cardiomyopathy III: Hypertrophic Cardiomyopathy01:29

Cardiomyopathy III: Hypertrophic Cardiomyopathy

Hypertrophic cardiomyopathy, or HCM, is an autosomal dominant genetic disorder characterized by asymmetric left ventricular hypertrophy without ventricular dilation. It is more common in men and is typically diagnosed in young, athletic adults.EtiologyHCM is primarily genetic and is caused by mutations in genes encoding sarcomeric proteins. Researchers have identified over 1400 mutations across at least 11 different genes. Among these, the most frequently occurring mutations are found in the...
Type I Diabetes II: Pathophysiology01:26

Type I Diabetes II: Pathophysiology

Type 1 diabetes mellitus arises from an immune-mediated destruction of pancreatic β-cells, resulting in an absolute deficiency of insulin. This process develops in genetically susceptible individuals when autoimmunity, environmental exposures, and immunologic dysregulation converge to trigger a targeted attack on the insulin-producing cells of the pancreas. The β-cells are located within the islets of Langerhans and are essential for regulating blood glucose by facilitating cellular uptake of...
Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations

Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Type II Diabetes I: Introduction01:26

Type II Diabetes I: Introduction

Type 2 diabetes mellitus (T2DM) is a chronic metabolic disorder characterized by insulin resistance, in which target tissues such as the liver, muscle, and adipose tissue respond poorly to insulin. It is also associated with inadequate compensatory insulin secretion, where pancreatic β-cells fail to produce sufficient insulin. Together, these abnormalities lead to persistent hyperglycemia.EtiologyT2DM develops through a complex interaction of genetic predisposition and environmental or...
Type II Diabetes II: Pathophysiology01:24

Type II Diabetes II: Pathophysiology
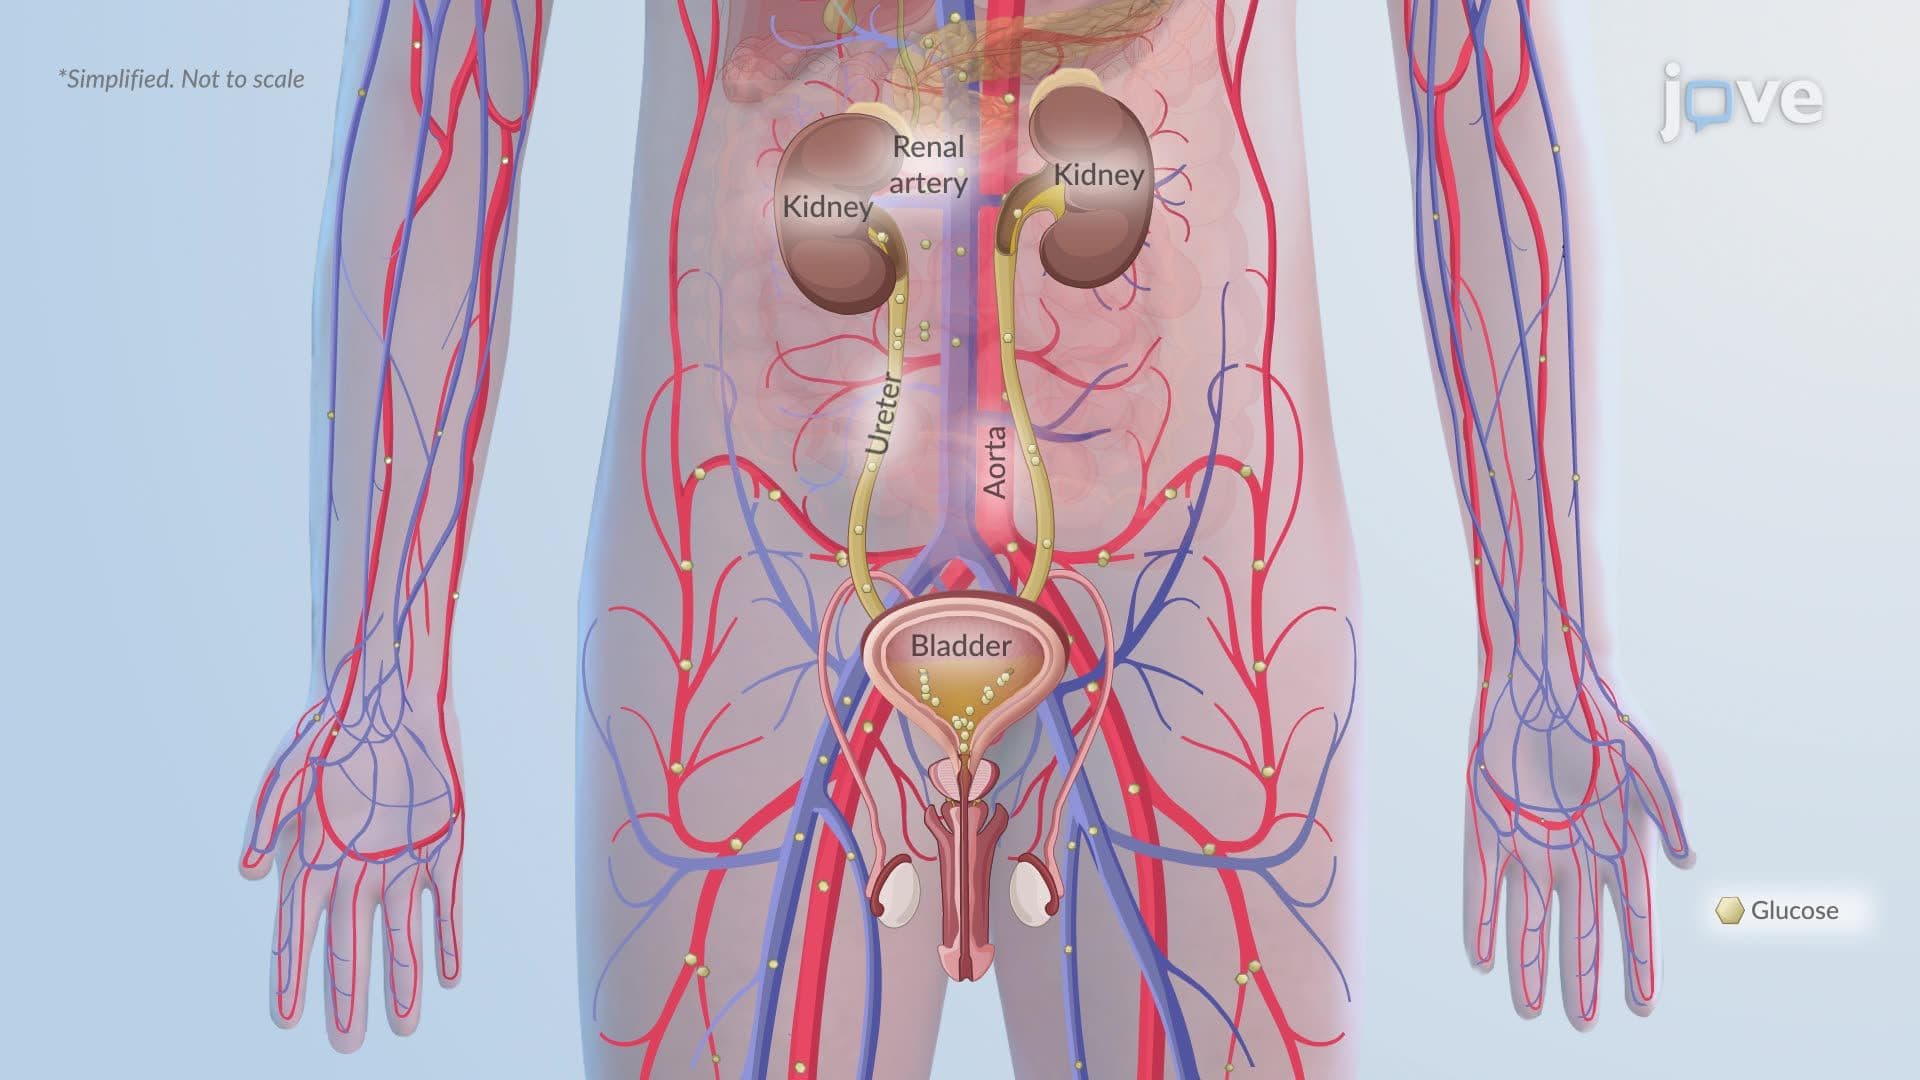
PathophysiologyType 2 diabetes mellitus (T2DM ) is a chronic metabolic disorder characterized by insulin resistance and progressive pancreatic β-cell dysfunction, leading to impaired glucose homeostasis. It results from interactions among genetic predisposition, environmental factors, and metabolic stressors, such as overnutrition and a sedentary lifestyle.Insulin Resistance and Glucose DysregulationEarly T2DM involves insulin resistance in skeletal muscle, adipose tissue, and the liver.
Diabetic Ketoacidosis ll: Pathophysiology01:22

Diabetic Ketoacidosis ll: Pathophysiology

Diabetic ketoacidosis (DKA) is a metabolic emergency characterized by hyperglycemia, ketonemia, and metabolic acidosis. It results from severe insulin deficiency and an excess of counterregulatory hormones, leading to uncontrolled lipolysis, ketogenesis, and widespread electrolyte and fluid disturbances.Pathophysiology The central event in DKA is a profound loss of insulin action. Without insulin, glucose uptake in insulin-dependent tissues is impaired, while hepatic glucose production...