Left-lung-collapse bronchial deformation in giant omphalocele
Related Experiment Video
Updated: Aug 12, 2026
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
B M Headley1, P N McDougall, K B Stokes
1Department of Neonatology, Royal Children's Hospital, Melbourne, Australia.

Insights
Infants with giant omphalocele can experience persistent left lung collapse due to bronchial narrowing. Positive end-expiratory pressure can reverse this narrowing, aiding respiratory support in these critical cases.
Area of Science:
- Pediatric Surgery
- Neonatal Respiratory Medicine
- Thoracic Imaging
Background:
- Giant omphalocele is a complex congenital anomaly requiring specialized neonatal care.
- Persistent lung collapse in neonates necessitates thorough investigation of underlying causes.
- Respiratory support is crucial for managing infants with severe congenital conditions.
Observation:
- Five infants diagnosed with giant omphalocele presented with persistent left lung collapse.
- These infants required extended periods of mechanical ventilation and respiratory support.
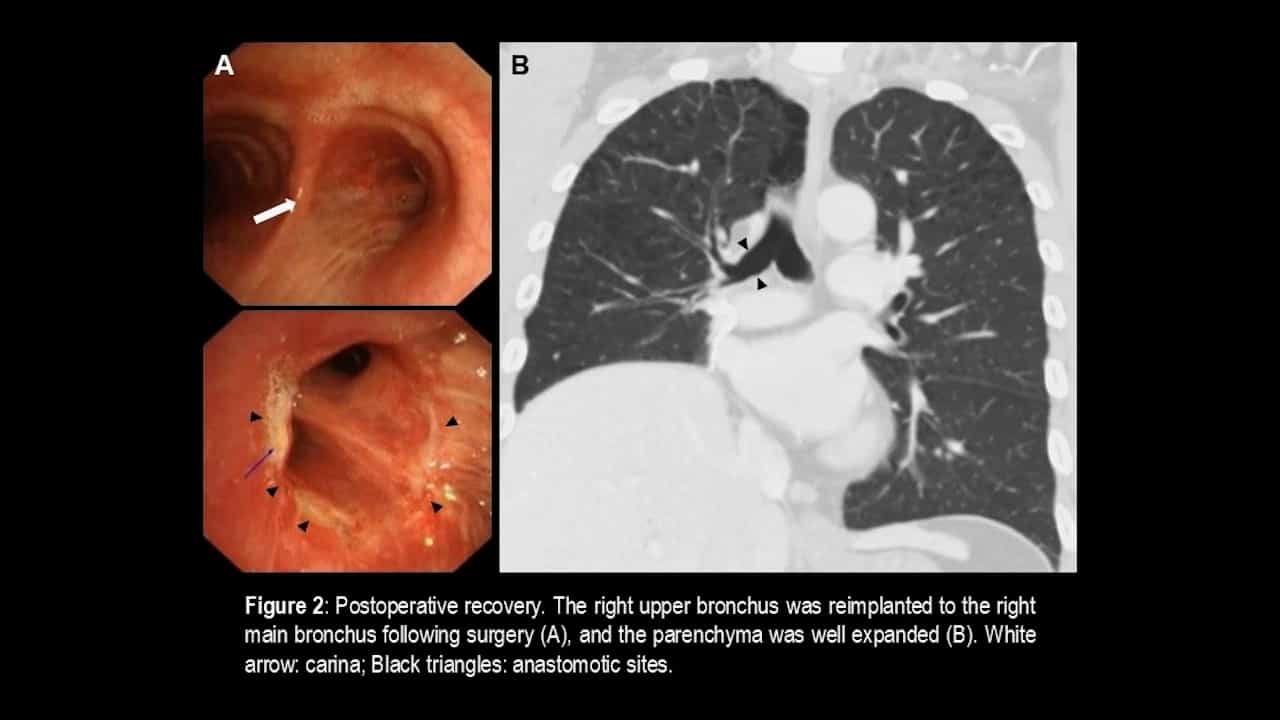
- Radiographic evaluation revealed significant narrowing of the left main bronchus in three of the affected infants.
Findings:
- The left main bronchial narrowing observed was reversible with the application of positive end-expiratory pressure (PEEP).
- We hypothesize that the narrow and elongated thoracic cavity in these patients contributes to bronchial distortion.
- Manipulation or attempted reduction of the giant omphalocele may precipitate or exacerbate lung collapse.
Implications:
- Positive end-expiratory pressure (PEEP) may be a valuable therapeutic strategy for managing bronchial narrowing in this population.
- Understanding the relationship between thoracic cavity dimensions and bronchial anatomy is critical for surgical and medical management.
- This finding highlights a potential mechanism for respiratory compromise in neonates with giant omphalocele, guiding clinical interventions.
Abstract:
Five infants with giant omphalocele had persistent collapse of the left lung and required prolonged respiratory support. Narrowing of the left main bronchus, reversible with positive end-expiratory pressure, was identified radiographically in 3 infants, and we postulate that this relates to distortion of the bronchus within the constraints of the elongated, narrow thoracic cavity characteristic of these patients. The lung collapse may be precipitated by manipulation (reduction or attempted reduction) of the omphalocele. J Pediatr Surg 36:846-850.
Related Concept Videos
 01:17
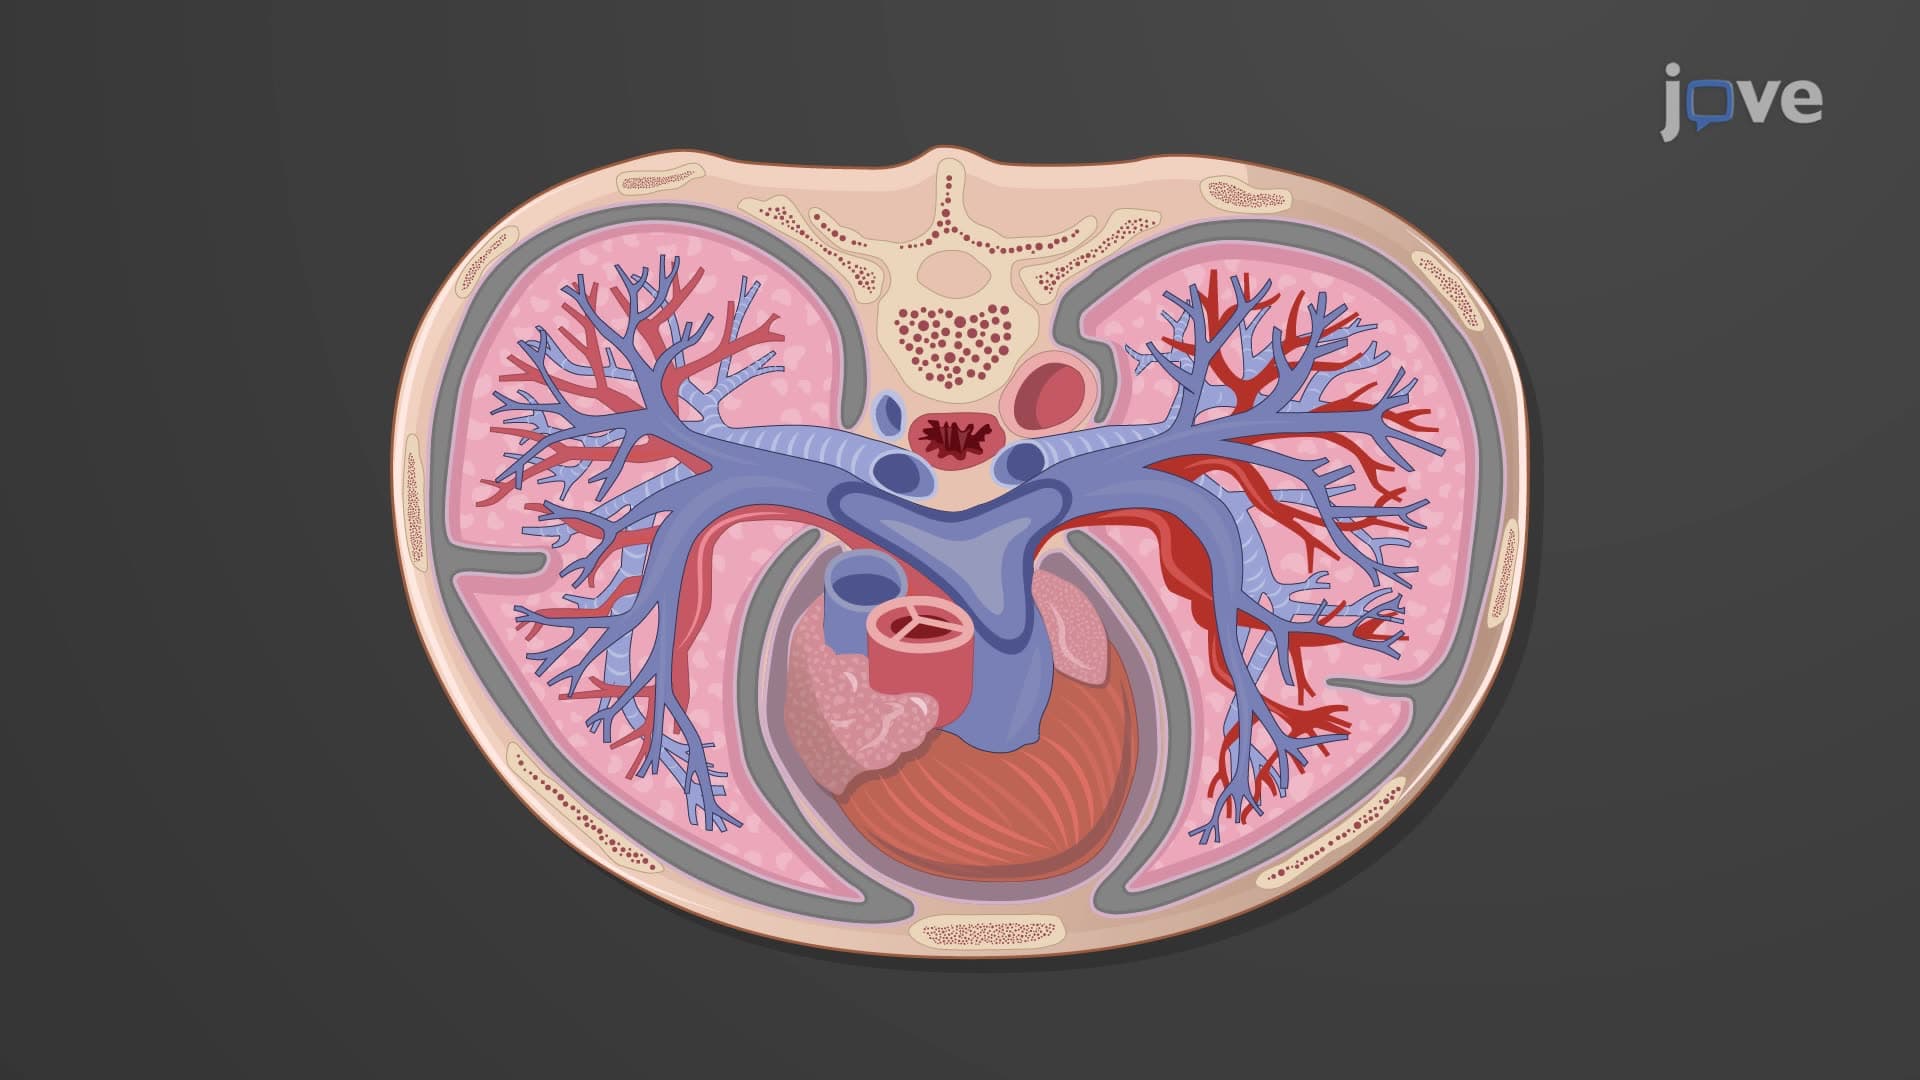
Gross Anatomy of the Lungs
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:08
Pneumothorax II: Pathophysiology
 01:10
Atelectasis II: Pathophysiology
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema