Related Experiment Video
Updated: Aug 13, 2026

Two Methods for Establishing Primary Human Endometrial Stromal Cells from Hysterectomy Specimens
Published on: May 23, 2014
Endometrial effects of lower doses of conjugated equine estrogens and medroxyprogesterone acetate
J H Pickar1, I Yeh, J E Wheeler
1Clinical Research and Development, Wyeth-Ayerst Research, Philadelphia, Pennsylvania, USA. pickarj@war.wyeth.com

Objective:
To determine the endometrial safety of lower doses of continuous combined conjugated equine estrogens (CEE) and medroxyprogesterone acetate (MPA).
Design:
Randomized, double-blind, placebo-controlled study (the Women's Health, Osteoporosis, Progestin, Estrogen study).
Setting:
Study centers across the United States.
Patient(S):
Healthy, postmenopausal women (n = 2,673) with an intact uterus.
Intervention(S):
Patients received CEE 0.625 mg/day, CEE 0.625/MPA 2.5 mg/day, CEE 0.45 mg/day, CEE 0.45/MPA 2.5 mg/day, CEE 0.45/MPA 1.5 mg/day, CEE 0.3 mg/day, CEE 0.3/MPA 1.5 mg/day, or placebo for 1 year. Endometrial biopsies were evaluated at baseline, cycle 6, and year 1 using a centralized protocol.
Main Outcome Measure(S):
Efficacy of lower doses of CEE/MPA in reducing the incidence of endometrial hyperplasia rates associated with unopposed CEE.
Result(S):
Endometrial hyperplasia rates ranged from 0 to 0.37% for all CEE/MPA doses. Twenty-nine of the 32 cases of endometrial hyperplasia developed in women who were administered CEE 0.625 mg or CEE 0.45 mg. The incidence of endometrial hyperplasia increased with age for patients administered CEE alone. As expected, there were some inconsistencies among pathologists' ratings in the numbers of hyperplasias and incidence rates for the CEE-alone regimens. There were too few cases of hyperplasia in the combination groups to evaluate consistency among pathologists.
Conclusion(S):
One year of treatment with lower doses of CEE/MPA provides endometrial protection comparable to commonly prescribed doses. These regimens may be used by clinicians to individualize hormone replacement therapy in postmenopausal women.
More Related Videos
 06:18
An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
 06:22
Ex Vivo Method for Assessing the Mouse Reproductive Tract Spontaneous Motility and a MATLAB-based Uterus Motion Tracking Algorithm for Data Analysis
Published on: September 1, 2019
Related Concept Videos
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:27
Ovarian Cycle
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:21
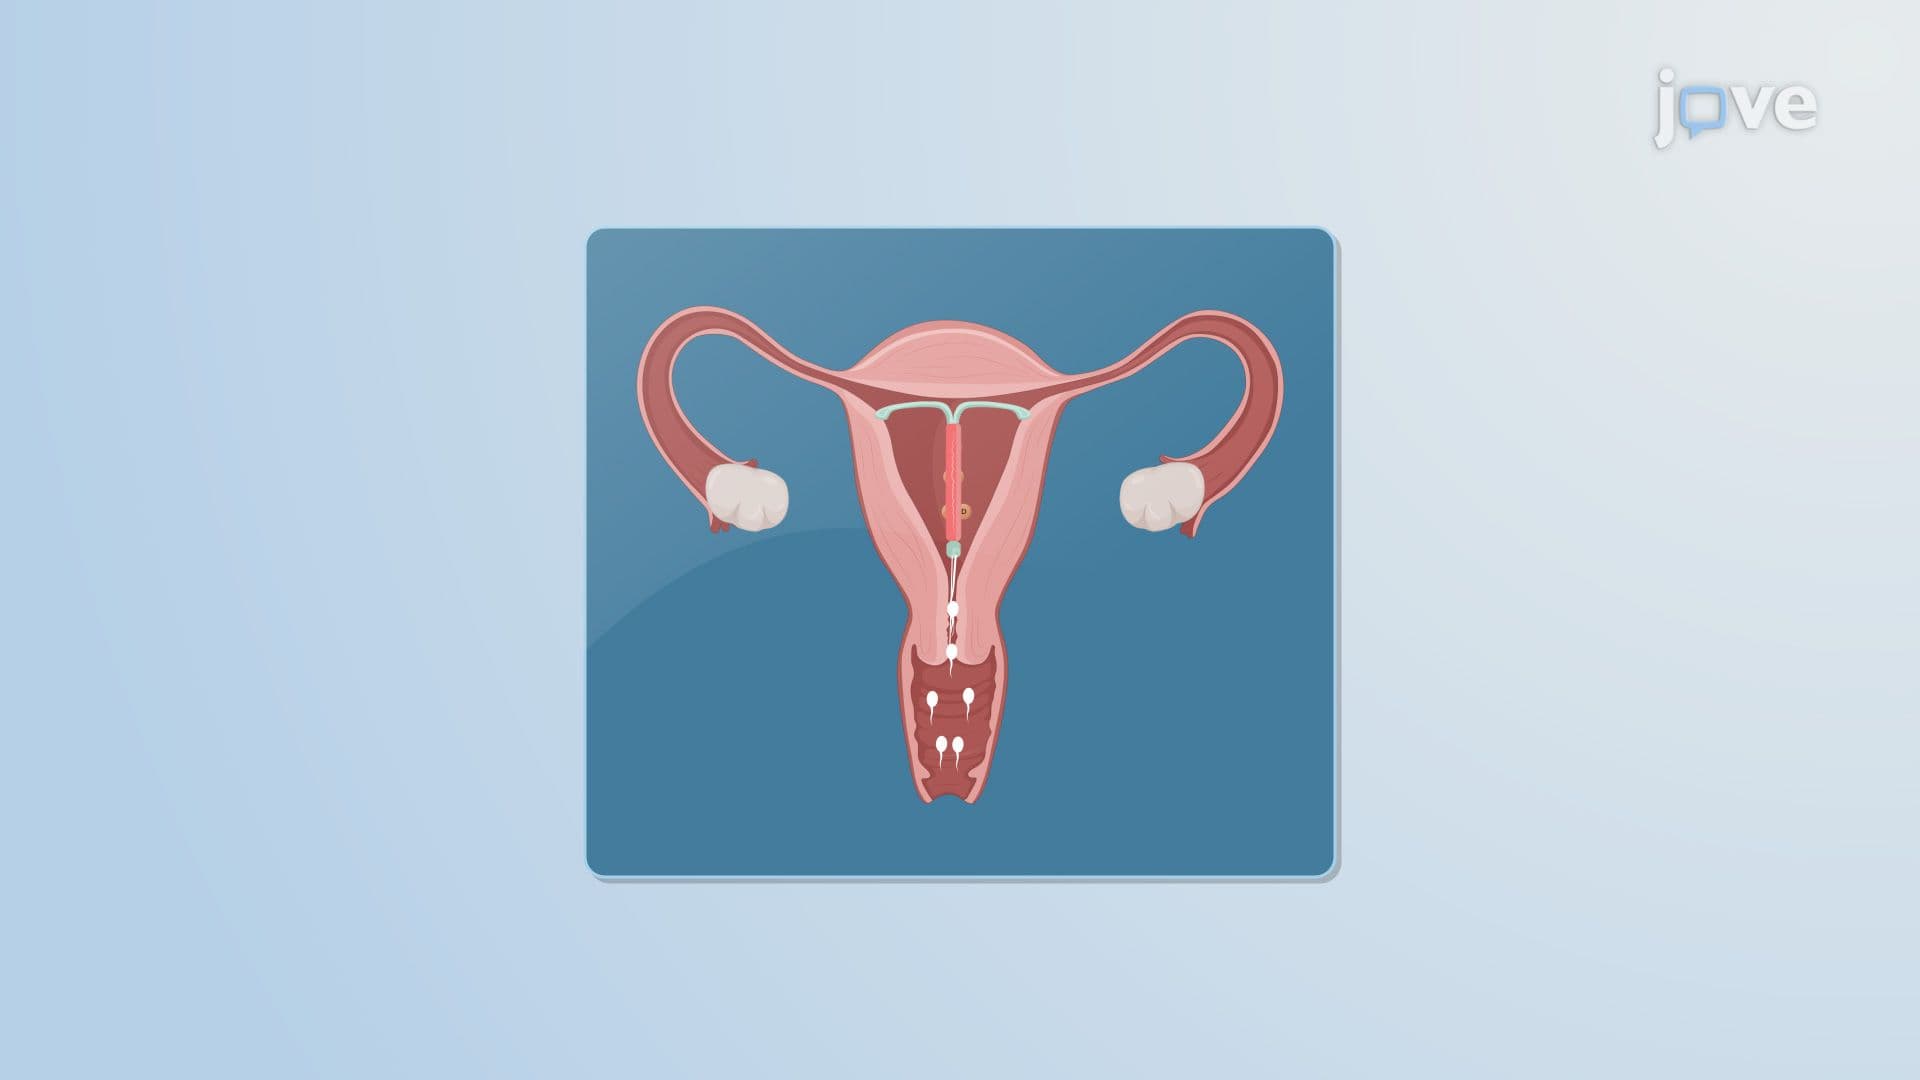
Intrauterine Drug Delivery Systems