Related Experiment Video
Updated: Oct 5, 2026

Ultrasonographic Evaluation of Breast Cancer-related Lymphedema
Published on: January 12, 2017
Differences in lymph drainage between swollen and non-swollen regions in arms with breast-cancer-related lymphoedema
A W Stanton1, W E Svensson, R H Mellor
1Division of Physiological Medicine (Dermatology), Department of Medicine, St George's Hospital Medical School, Cranmer Terrace, London SW170RE, UK. astanton@sghms.ac.uk

Abstract:
Recent research indicates that the pathophysiology of breast-cancer-related lymphoedema (BCRL) is more complex than simple axillary lymphatic obstruction as a result of the cancer treatment. Uneven distribution of swelling (involvement of the mid-arm region is common, but the hand is often spared) is puzzling. Our aim was to test the hypothesis that local differences in lymphatic drainage contribute to the regionality of the oedema. Using lymphoscintigraphy, we measured the removal rate constant, k (representing local lymph flow per unit distribution volume, VD), for 99mTc-labelled human immunoglobulin G in the oedematous proximal forearm, and in the hand (finger web) in women in whom the hand was unaffected. Tracer was injected subcutaneously, and the depot plus the rest of the arm was monitored with a gamma-radiation camera for up to 6 h. VD was assessed from image width. Contralateral arms served as controls. k was 25% lower in oedematous forearm tissue than in the control arm (BCRL, -0.070+/-0.026% x min(-1); control, -0.093+/-0.028% x min(-1); mean+/-S.D.; P=0.012) and VD was greater. In the non-oedematous hand of the BCRL arm, k was 18% higher than in the control hand (BCRL, -0.110+/-0.027% x min(-1); control, -0.095+/-0.028% x min(-1); P=0.057) and 59% higher than forearm k on the BCRL side (P=0.0014). VD did not differ between the hands. Images of the BCRL arm following hand injection showed diffuse activity in the superficial tissues, sometimes extending almost to the shoulder. A possible interpretation is that the hand is spared in some patients because local lymph flow is increased and diverted along collateral dermal routes. The results support the hypothesis that regional differences in surviving lymphatic function contribute to the distribution of swelling.

Related Concept Videos
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular spaces.
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:17
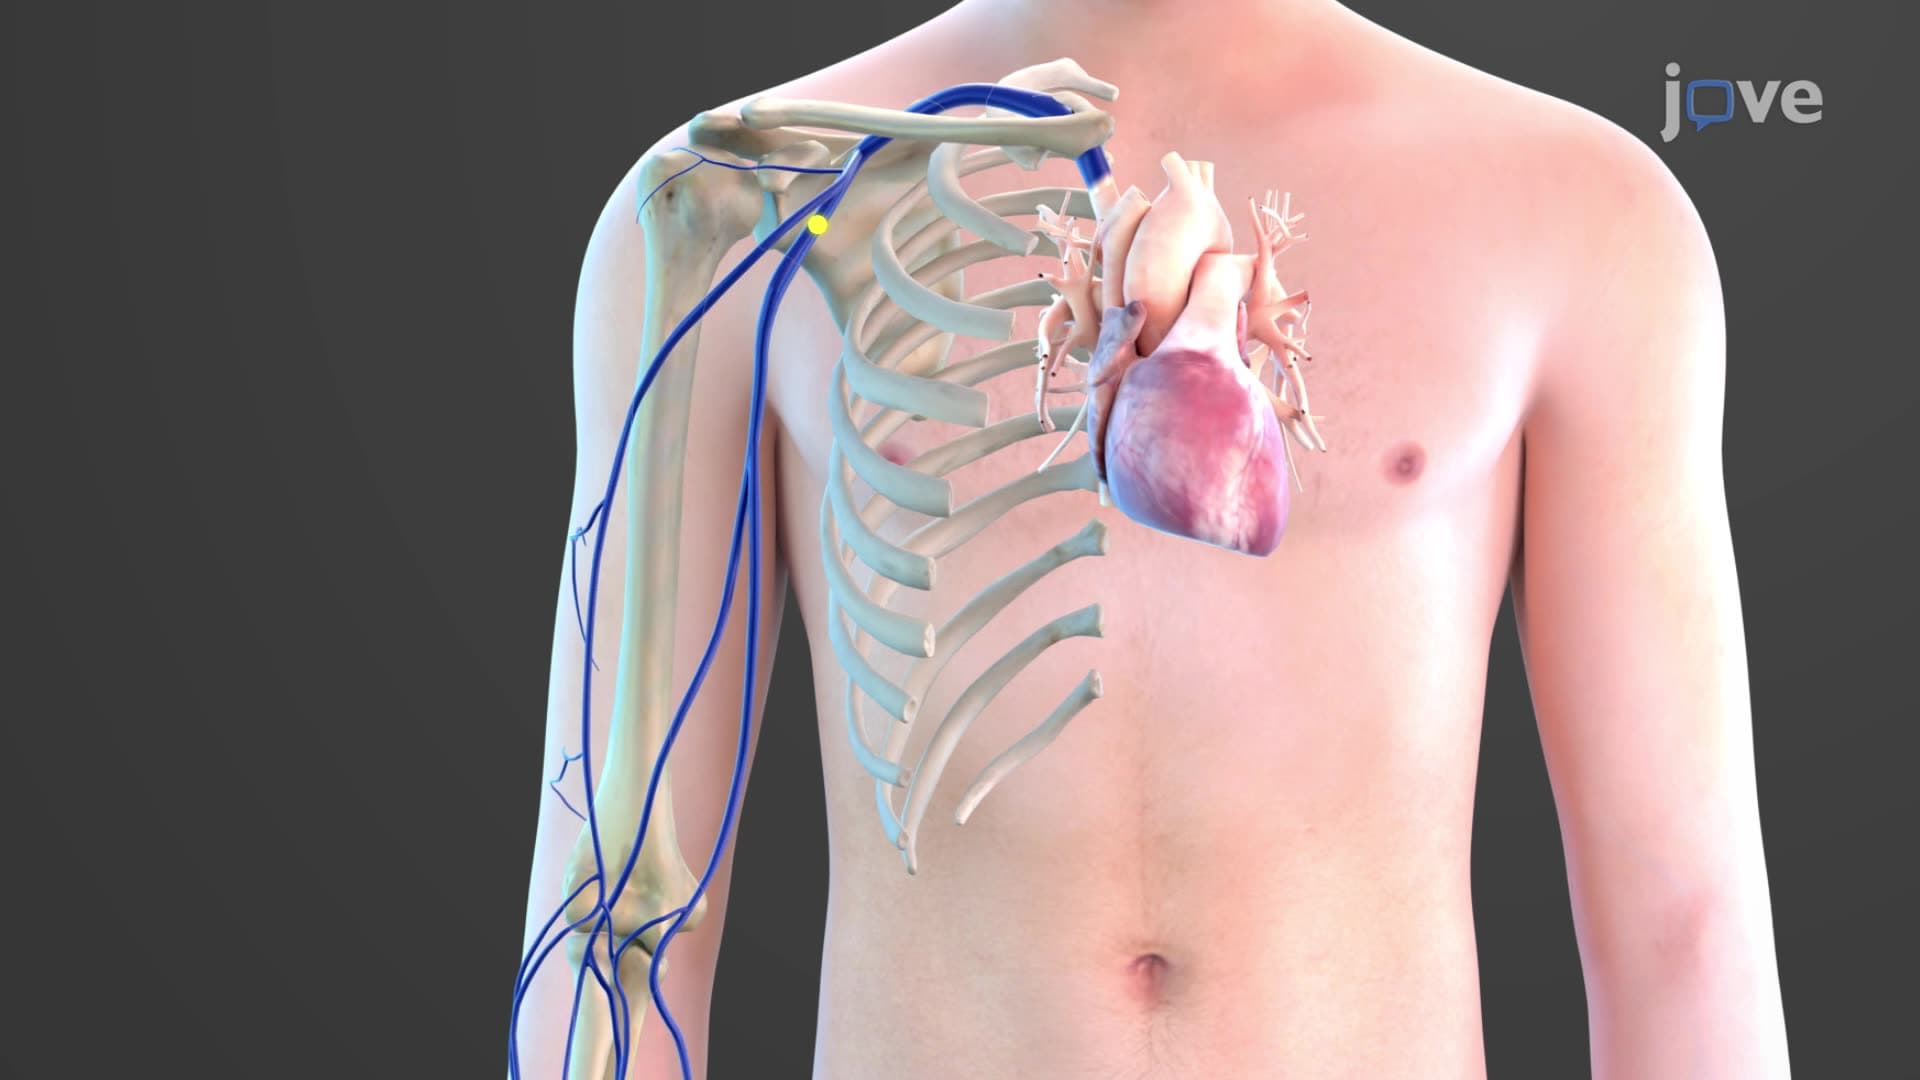
Veins of Upper Limbs
The deep venous system is primarily composed of the ulnar and radial veins. The ulnar vein, which drains the fingers through the superficial palmar venous arches, and the radial vein, which serves the palms via the deep palmar...