Related Experiment Video
Updated: Oct 4, 2026
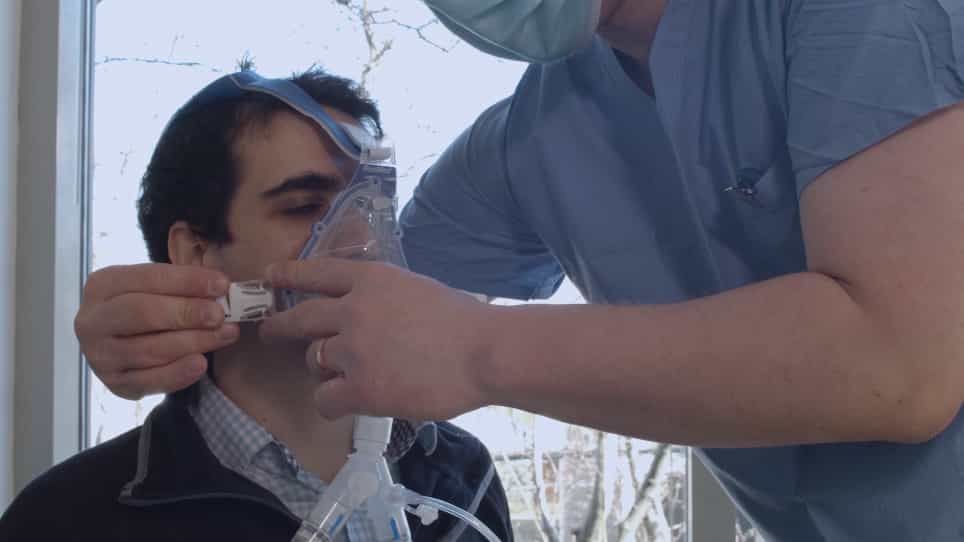
A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Exhaled nitric oxide and asthma in young children
A Avital1, K Uwyyed, N Berkman
1Institute of Pulmonology, Hadassah University Hospital and Hebrew University-Hadassah Medical School, Jerusalem, Israel. avi@lung.hadassah.org.il

Abstract:
Exhaled nitric oxide (eNO) has been used to diagnose asthma in adults and children using either the slow vital capacity method (SVCm) or, in younger children, the tidal breathing method (TBm). Adenosine 5'-monophosphate (AMP) challenge also has been found to be a sensitive and specific test for the diagnosis of asthma. In the present study, we used the AMP provocation concentration that caused wheezing (PCW) to confirm the diagnosis of asthma (PCW < or = 200 mg/mL). We studied 36 children (2-7 years) with mild intermittent asthma, 13 children (3-7 years) with moderate persistent asthma treated with inhaled steroids, 20 nonasthmatic children (2-7 years) with chronic cough and recurrent pneumonia, and 15 healthy children (4-6 years). Expired gas was collected in collection bags by the TBm, and eNO was measured. We evaluated the efficacy of eNO values in diagnosing asthma. The mean eNO level of the mild intermittent asthmatic children (5.6 +/- 0.4 ppb) not receiving inhaled corticosteroids was significantly higher (ANOVA P < 0.0001) than that of the moderate persistent asthmatics who were treated with inhaled steroids, the nonasthmatic children with chronic cough, and the group of healthy children (3.7 +/- 0.6 ppb, P < 0.05; 3.2 +/- 0.3 ppb, P < 0.001; 2.2 +/- 0.2 ppb, P < 0.001, respectively). The points of intersection for sensitivity and specificity curves of eNO to differentiate mild intermittent asthmatics from nonasthmatic children with chronic cough and from healthy children were 77% and 88% for eNO values of 3.8 ppb and 2.9 ppb, respectively. We conclude that eNO collected by the TBm can differentiate steroid-naive young children with intermittent asthma from healthy children, from nonasthmatic children with chronic cough, and from asthmatic children treated with inhaled steroids.
Related Concept Videos
 01:28
Asthma I: Introduction
 01:29
Asthma-I: Introduction
 01:13
Asthma III: Clinical Manifestations
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include: