Related Experiment Video
Updated: Jul 29, 2026
Evaluation of Fluid Overload by Bioelectrical Impedance Vectorial Analysis
Published on: August 17, 2022
Gibbs memorial lecture. Unifying hypothesis of body fluid volume regulation: implications for cardiac failure and
1Department of Medicine, University of Colorado School of Medicine, Denver, CO, USA.

Insights
Body fluid volume is vital for life, regulated by maintaining arterial circulatory integrity. Dysregulation leads to detrimental neurohumoral responses in conditions like heart failure and cirrhosis.
Area of Science:
- Physiology
- Cardiovascular Medicine
- Nephrology
Background:
- Body fluid volume regulation is crucial for maintaining arterial circulatory integrity.
- Arterial circulation integrity, influenced by cardiac output and vascular resistance, dictates renal sodium and water retention.
Discussion:
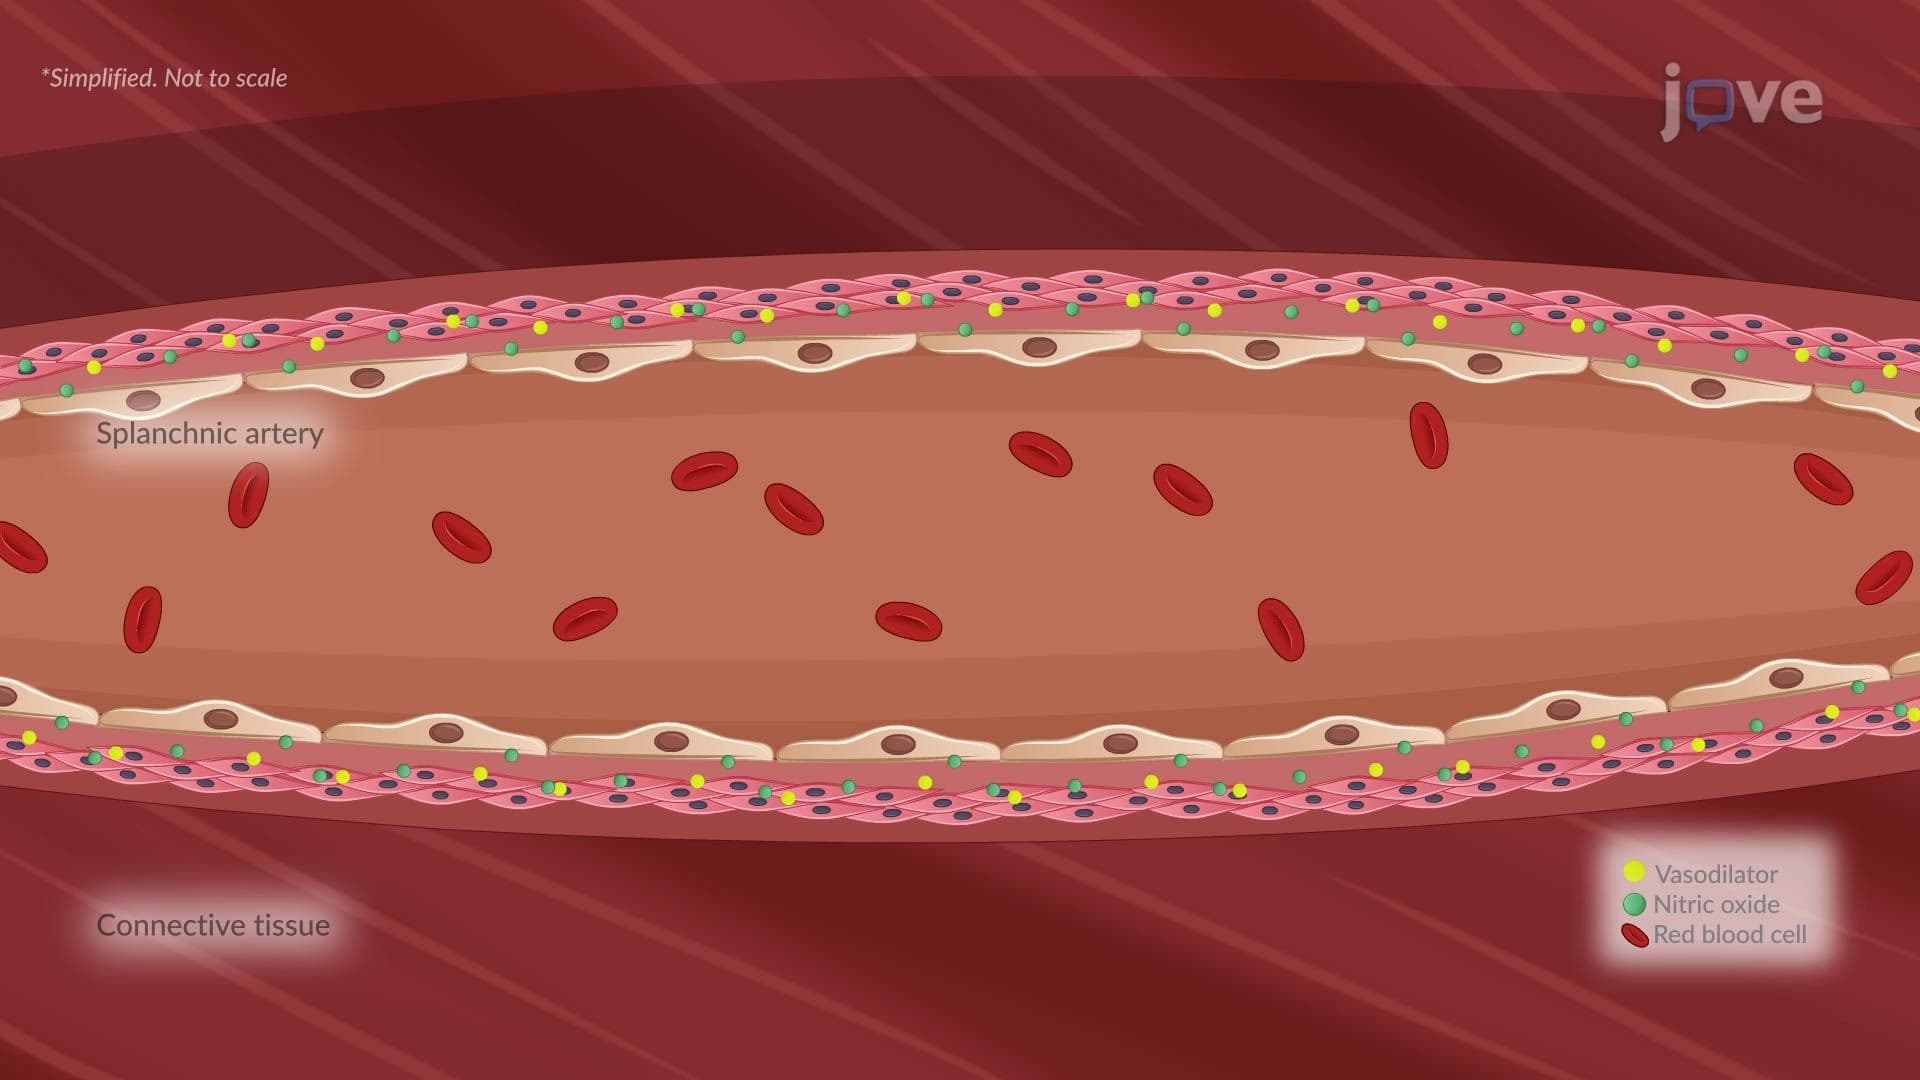
- Arterial underfilling, caused by decreased cardiac output or vascular resistance, activates baroreceptors.
- This triggers compensatory neurohumoral responses: sympathetic nervous system stimulation, renin-angiotensin-aldosterone system (RAAS) activation, and vasopressin release.
- While adaptive, these responses can cause long-term issues like pulmonary congestion, increased cardiac afterload, ascites, and hyponatremia.
Key Insights:
- The intensity of neurohumoral responses correlates with the severity of cardiac failure and cirrhosis.
- Understanding sodium and water retention mechanisms in these diseases is key.
- Therapies targeting these mechanisms improve patient morbidity and mortality.
Outlook:
- Further research into the precise mechanisms of baroreceptor signaling in fluid volume regulation.
- Development of targeted therapies to mitigate detrimental long-term effects of compensatory responses.
- Investigating the role of neurohumoral pathways in other fluid-regulating disorders.
Abstract:
Body fluid volume regulation is critically important in maintaining life. In this paper, we review our unifying hypothesis of body fluid volume regulation, which maintains arterial circulatory integrity in health and disease. The integrity of the arterial circulation, as determined by cardiac output and peripheral vascular resistance, is the predominant determinant of renal sodium and water retention. Arterial circulatory integrity can be disturbed either by a decrease in cardiac output, as in low-output cardiac failure, or by a decrease in peripheral vascular resistance, as in high-output states such as high-output cardiac failure and cirrhosis. The resulting arterial underfilling is sensed by baroreceptors that are located in the left ventricle, the aortic arch, the carotid sinus and the renal afferent arterioles. Decreased activation of these receptors during arterial underfilling leads to neurohumoral compensatory responses, which include the stimulation of the sympathetic nervous system, activation of the renin-angiotensin-aldosterone system (RAAS) and the non-osmotic release of vasopressin. These compensatory responses maintain arterial circulatory integrity by increasing peripheral and renal arterial vascular resistance together with renal sodium and water retention. However, over the long term, these adaptive responses may have detrimental effects, such as pulmonary congestion, increased myocardial demand, increased cardiac afterload, ascites and hyponatremia. The intensity of the neurohumoral responses correlates with the progression and severity of both cardiac failure and cirrhosis. The understanding of the pathogenesis of sodium and water retention in cardiac failure and cirrhosis has led to therapies that favorably affect the morbidity and mortality of these patients.
Related Concept Videos
 01:17
Pathophysiology of Heart Failure
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:29
Heart Failure II: Pathophysiology
 01:18
Pulmonary Edema II: Pathophysiology
 01:24
Cirrhosis II: Pathophysiology
 01:19
Ascites