Related Experiment Video
Updated: Jul 11, 2026
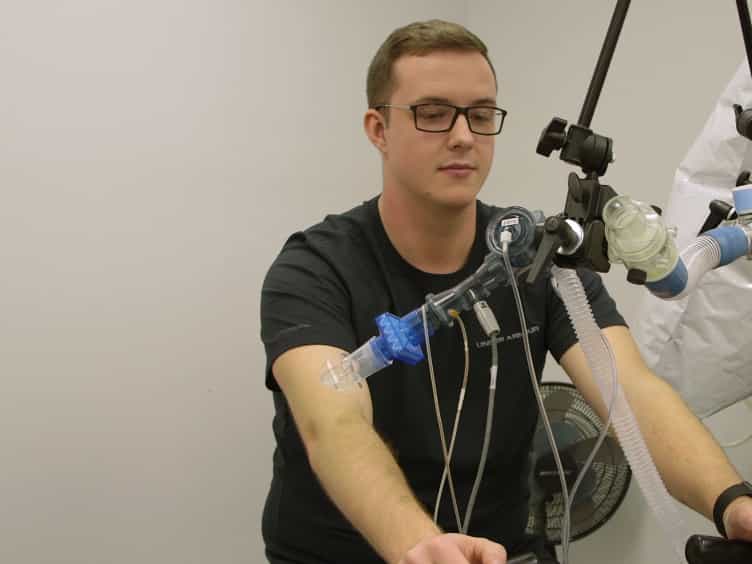

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
[Exercise tolerance in relation to ventilatory drive and respiratory muscle function in COPD]
1Institute of the Respiratory Disease, China Medical University, Shenyang 110001, China.

Objective:
To assess the relationships between exercise tolerance and respiratory drive and respiratory muscle function in COPD.
Methods:
28 patients with COPD and 26 normal subjects were involved in the study. Routine pulmonary function, pulmonary diffusing capacity, P0.1, PImax were measured at rest. Oxygen consumption (VO2), carbon dioxide production (VCO2), minute ventilation (VE) etc were measured during exercise testing. Borg Scale was recorded simultaneously. Arterial blood gases were measured before and after exercise.
Results:
(1) PImax in COPD group (40 +/- 15 mm Hg) was significantly lower than that in the normal group [(53 +/- 19) mm Hg, P < 0.05]. P0.1 in COPD group [(2.8 +/- 0.9) mm Hg] was significantly higher than that in the normal group [(2.0 +/- 0.7) mm Hg, P < 0.05]. Inspiratory drive efficacy (VT/P0.1) in COPD group [(0.21 +/- 0.04) L/mm Hg] was significantly lower than that in the normal group [(0.28 +/- 0.07) L/mm Hg, P < 0.05]. P0.1/PImax in COPD group was (0.069 +/- 0.021), significantly higher than that in the normal group [(0.037 +/- 0.009), P < 0.01]. (2) VO2max was correlated with P0.1/Pimax and Borg Scale in COPD patients (r = 0.66, P < 0.01, and r = 0.53, P < 0.05 respectively). Borg Scale was also positively correlated with P0.1/PImax in COPD group (r = 0.49, P < 0.05).
Conclusion:
In addition to airway obstruction and the damaged gas exchange, exercise intolerance in COPD may also be related to the increased respiratory drive and dysfunction of respiratory muscle.
More Related Videos


Related Concept Videos
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction