Angiooedema due to acquired deficiency of C1-esterase inhibitor associated with leucocytoclastic vasculitis

H Farkas1, M Szongoth, M Bély

  • 1Allergology and Angioedema Outpatient Clinic, Semmelweis University, Kútvölgyi Centre, Budapest, Hungary. farkash@kut.sote.hu

Acta Dermato-Venereologica
|November 27, 2001
PubMed

Related Concept Videos

Rheumatic Heart Disease I: Introduction01:23

Rheumatic Heart Disease I: Introduction

Rheumatic heart disease or RHD is a chronic condition that results from rheumatic fever, causing permanent damage to the heart valves.Etiology and Risk FactorsIt primarily arises from rheumatic fever, an inflammatory disease that can develop after untreated or inadequately treated group A streptococcal (GAS) pharyngitis. Streptococcus spreads through direct contact with oral or respiratory secretions. While the bacteria are the causative agents, factors like malnutrition, overcrowding, poor...
Cerebral Edema l: Introduction01:19

Cerebral Edema l: Introduction

Cerebral edema is a pathological increase in brain water content that disrupts intracranial pressure regulation and impairs neurological function. Because the cranial vault is rigid, even modest increases in tissue volume can compromise cerebral perfusion, distort neural structures, and initiate secondary injury. Cerebral edema develops through four principal mechanisms: vasogenic, cytotoxic, interstitial, and ionic.Vasogenic EdemaVasogenic edema arises from disruption of the blood–brain...
Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology
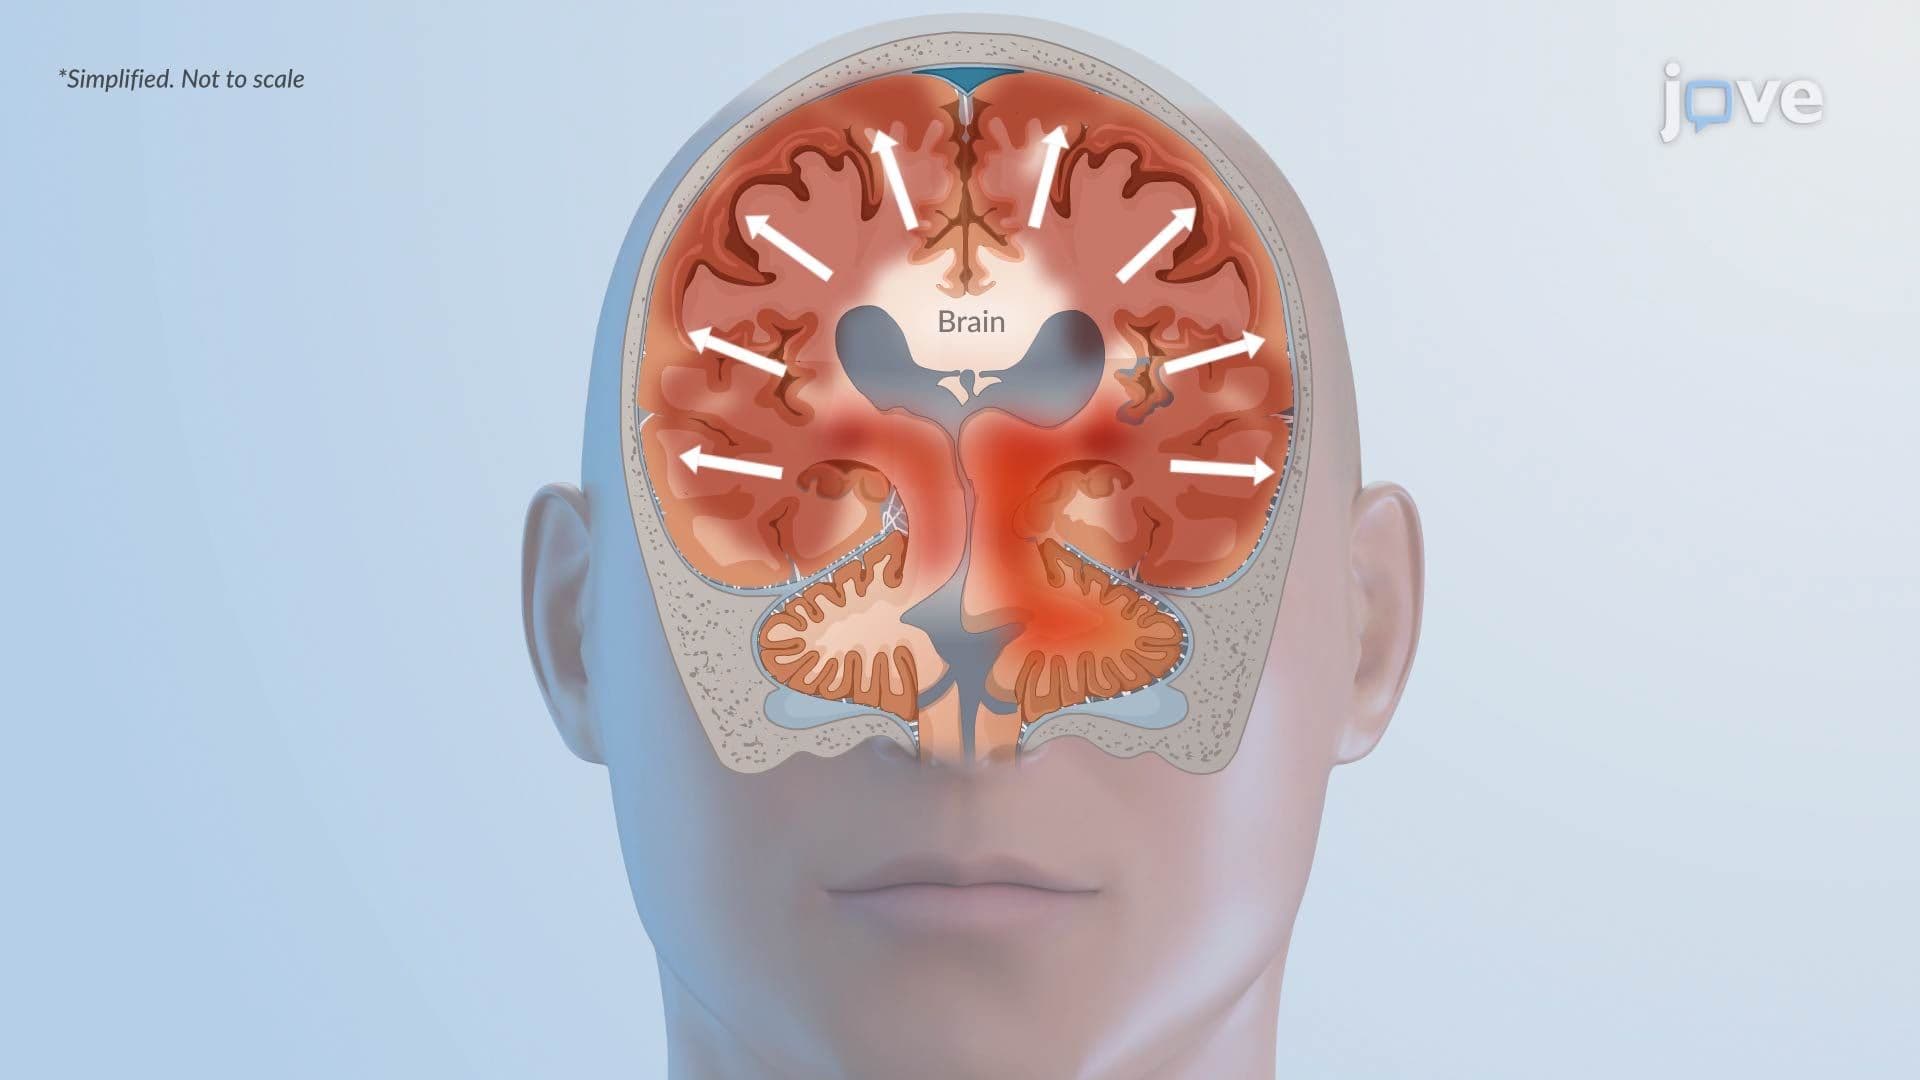
Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
Cytotoxic Edema: Pathophysiology01:21

Cytotoxic Edema: Pathophysiology

Cytotoxic edema is a form of cerebral edema characterized by intracellular swelling of neurons, astrocytes, and other glial cells. It develops when the mechanisms responsible for maintaining ionic gradients across the cell membrane become impaired. Under normal physiological conditions, the sodium–potassium ATPase actively transports sodium ions out of the cell and potassium ions into the cell, preserving osmotic balance and enabling electrical signaling. This pump requires a continuous supply...
Ascites01:19

Ascites

DefinitionAscites is the buildup of fluid inside the peritoneal cavity. It occurs when fluid moves out of the vascular system faster than the peritoneal lymphatics can remove it. This fluid shift is most commonly seen in liver cirrhosis but can also appear in several other systemic disorders.EtiologyCirrhosis remains the leading cause of ascites. Other conditions that can contribute include:Heart failureConstrictive pericarditisAbdominal cancersNephrotic syndromeSevere protein–calorie...
Hypersensitivity Reactions: Immune-Complex Reactions01:19

Hypersensitivity Reactions: Immune-Complex Reactions

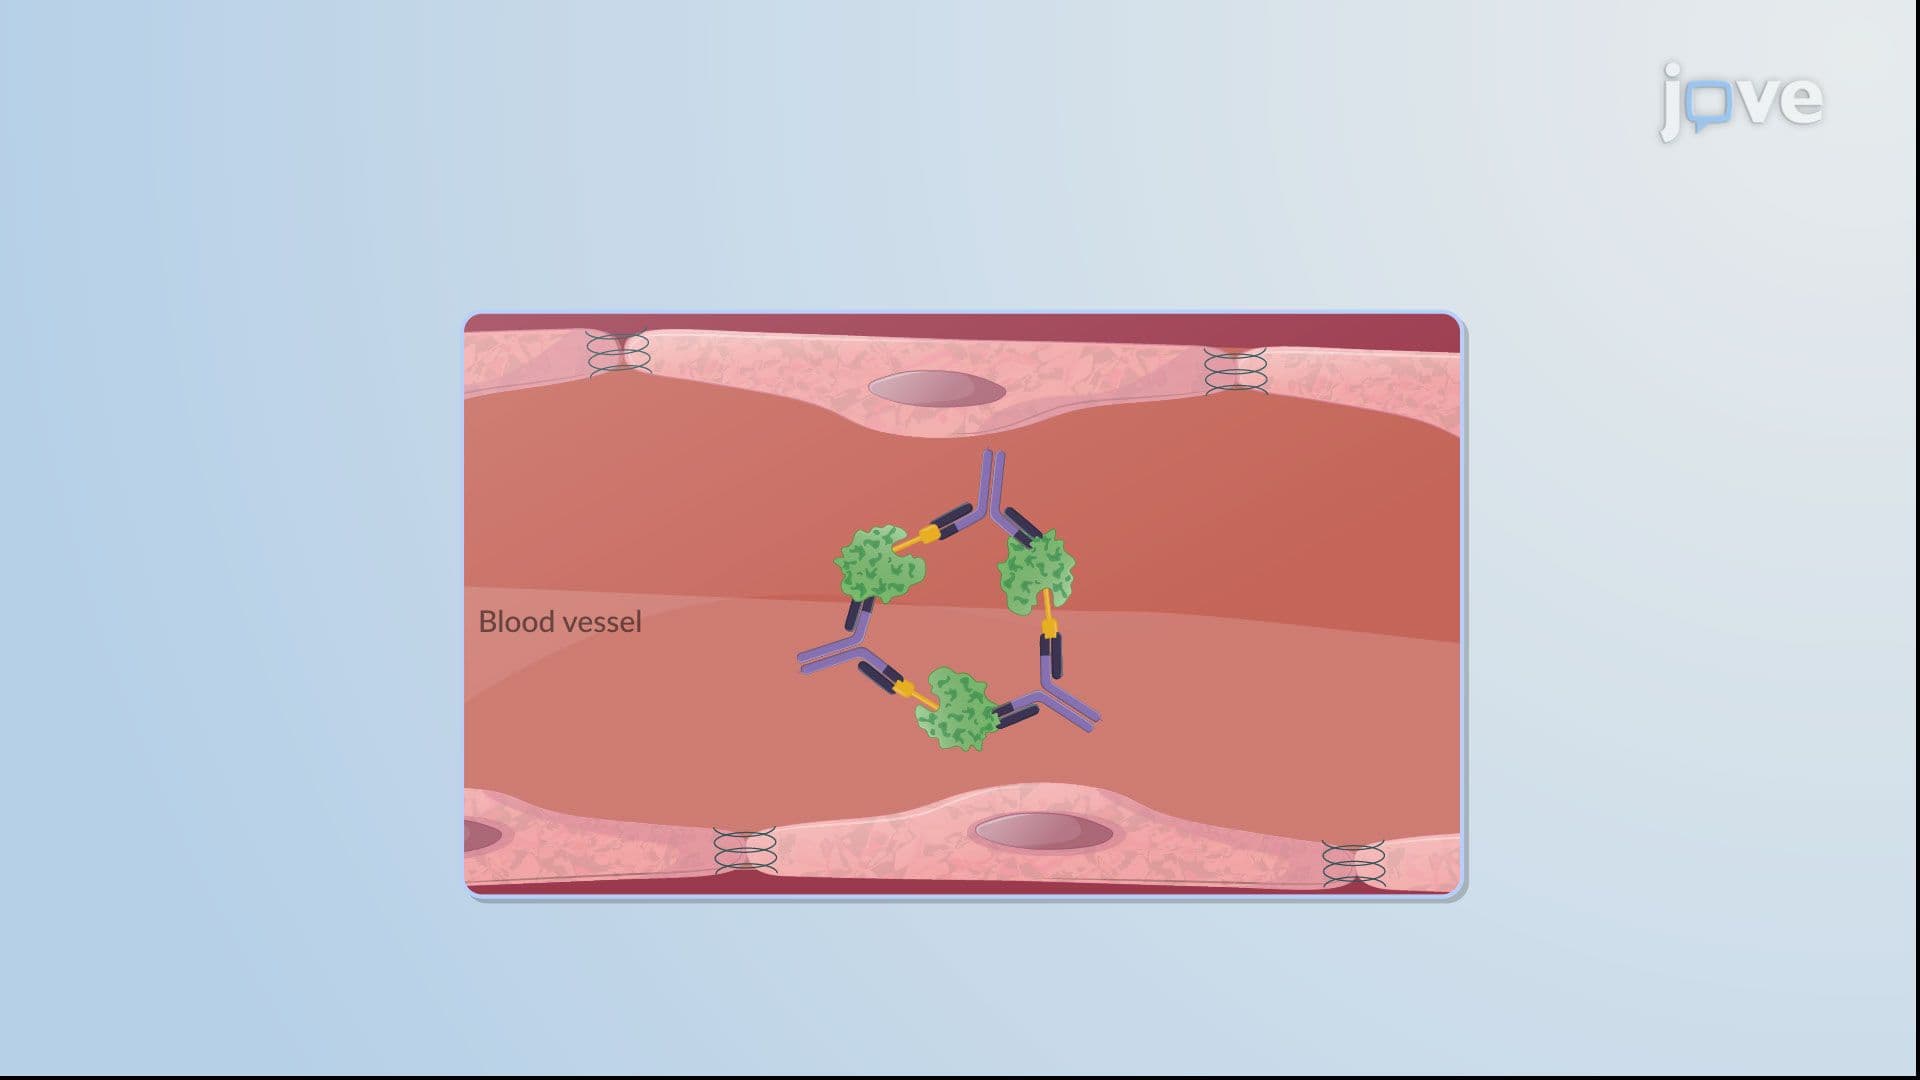
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum sickness, a systemic...