Related Experiment Video
Updated: Jul 14, 2026
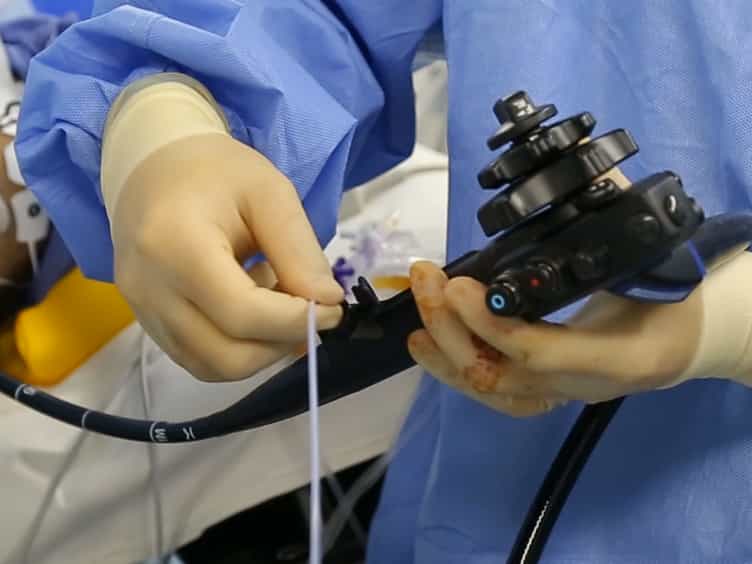
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Gastric surgery is not a risk for Barrett's esophagus or esophageal adenocarcinoma
B Avidan1, A Sonnenberg, T G Schnell
1Gastroenterology Section, Department of Veterans Affairs Medical Center, 1501 San Pedro Drive SE, Albuquerque, New Mexico 87108, USA.

Background & Aims:
The contribution of duodeno-gastroesophageal reflux to the development of Barrett's esophagus has remained an interesting but controversial topic. The present study assessed the risk for Barrett's esophagus after partial gastrectomy.
Methods:
The data of outpatients from a medicine and gastroenterology clinic who underwent upper gastrointestinal endoscopy for any reason were analyzed in a case-control study. A case population of 650 patients with short- segment and 366 patients with long-segment Barrett's esophagus was compared in a multivariate logistic regression to a control population of 3047 subjects without Barrett's esophagus or other types of gastroesophageal reflux disease.
Results:
In the case population, 25 (4%) patients with short-segment and 15 (4%) patients with long-segment Barrett's esophagus presented with a history of gastric surgery compared with 162 (5%) patients in the control population, yielding an adjusted odds ratio of 0.89 with a 95% confidence interval of 0.54-1.46 for short-segment and an adjusted odds ratio of 0.71 (0.30-1.72) for long-segment Barrett's esophagus. Similar results were obtained in separate analyses of 64 patients with Billroth-1 gastrectomy, 105 patients with Billroth-2 gastrectomy, and 33 patients with vagotomy and pyloroplasty for both short- and long-segment Barrett's esophagus. Caucasian ethnicity, the presence of hiatus hernia, and alcohol consumption were all associated with elevated risks for Barrett's esophagus.
Conclusions:
Gastric surgery for benign peptic ulcer disease is not a risk factor for either short- or long-segment Barrett's esophagus. This lack of association between gastric surgery and Barrett's esophagus suggests that reflux of bile without acid is not sufficient to damage the esophageal mucosa.
More Related Videos

Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:11
Pyloric Obstruction