Related Experiment Video
Updated: Oct 3, 2026

A Structured Approach to Extubation in Mechanically Ventilated Rats
Published on: July 18, 2025
Predicting success in weaning from mechanical ventilation

Abstract:
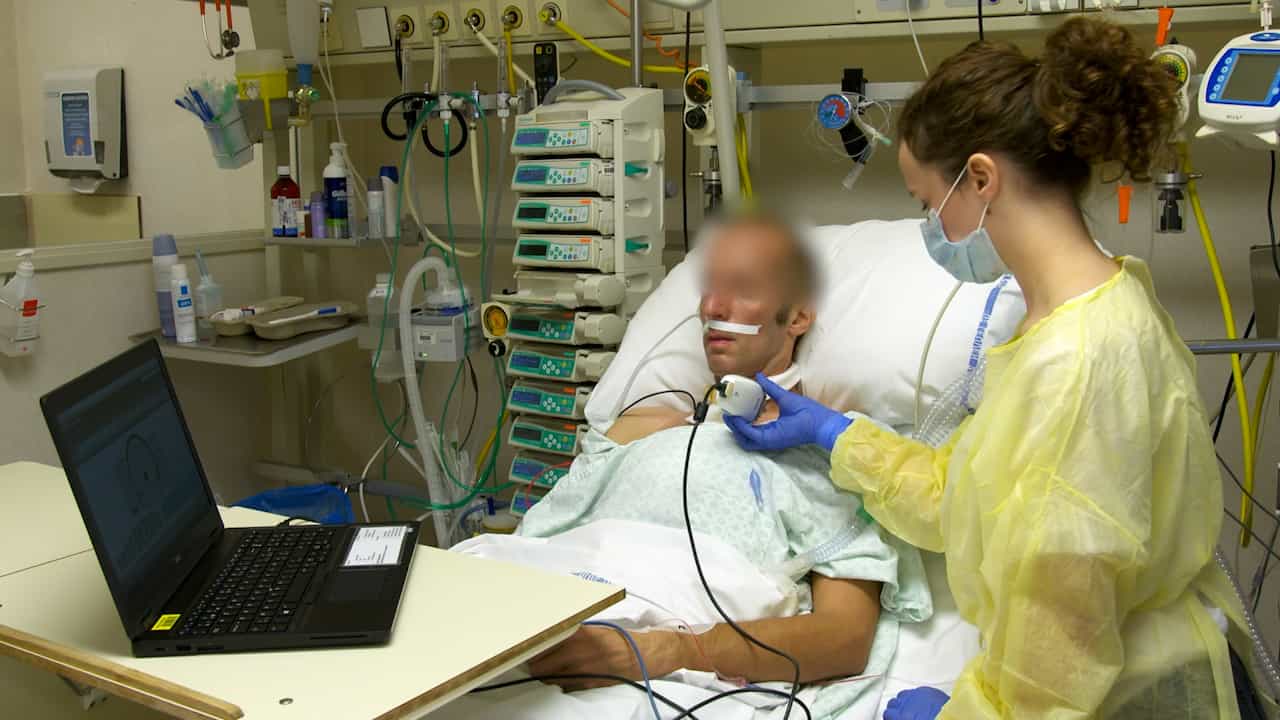
We identified 65 observational studies of weaning predictors that had been reported in 70 publications. After grouping predictors with similar names but different thresholds, the following predictors met our relevance criteria: heterogeneous populations, 51; COPD patients, 21; and cardiovascular ICU patients, 45. Many variables were of no use in predicting the results of weaning. Moreover, few variables had been studied in > 50 patients or had results presented to generate estimates of predictive power. For stepwise reductions in mechanical support, the most promising predictors were a rapid shallow breathing index (RSBI) < 65 breaths/min/L (measured using the ventilator settings that were in effect at the time that the prediction was made) and a pressure time product < 275 cm H2O/L/s. The pooled likelihood ratios (LRs) were 1.1 (95% confidence interval [CI], 0.95 to 1.28) for a respiratory rate [RR] of < 38 breaths/min and 0.32 (95% CI, 0.06 to 1.71) for an RR of > 38 breaths/min, which indicate that an RR of < 38 breaths/min leaves the probability of successful weaning virtually unchanged but that a value of > 38 breaths/min leads to a small reduction in the probability of success in weaning the level of mechanical support. For trials of unassisted breathing, the most promising weaning predictors include the following: RR; RSBI; a product of RSBI and occlusion pressure < 450 cm H2O breaths/min/L; maximal inspiratory pressure (PImax) < 20 cm H2O; and a knowledge-based system for adjusting pressure support. Pooled results for the power of a positive test result for both RR and RSBI were limited (highest LR, 2.23), while the power of a negative test result was substantial (ie, LR, 0.09 to 0.23). Summary data suggest a similar predictive power for RR and RSBI. In the prediction of successful extubation, an RR of < 38 breaths/min (sensitivity, 88%; specificity, 47%), an RSBI < 100 or 105 breaths/min/L (sensitivity, 65 to 96%; specificity, 0 to 73%), PImax, and APACHE (acute physiology and chronic health evaluation) II scores that are obtained at hospital admission appear to be the most promising. After pooling, two variables appeared to have some value. An RR of > 38 breaths/min and an RSBI of > 100 breaths/min/L appear to reduce the probability of successful extubation, and PImax < 0.3, for which the pooled LR is 2.23 (95% CI, 1.15 to 4.34), appears to marginally increase the likelihood of successful extubation. Judging by areas under the receiver operator curve for all variables, none of these variables demonstrate more than modest accuracy in predicting weaning outcome. Why do most of these tests perform so poorly? The likely explanation is that clinicians have already considered the results when they choose patients for trials of weaning.
Related Concept Videos
 01:29
Mechanical Ventilation I: Indication and Settings
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.