Related Experiment Video
Updated: Sep 1, 2026

Magnetic Resonance Imaging Quantification of Pulmonary Perfusion using Calibrated Arterial Spin Labeling
Published on: May 30, 2011
Lung albumin accumulation is spatially heterogeneous but not correlated with regional pulmonary perfusion
Anthony J Gerbino1, Robb W Glenny
1Department of Medicine, University of Washington, Seattle, Washington 98195, USA. anthony.gerbino@vmmc.org

Abstract:
The contribution of pulmonary perfusion heterogeneity to the development of regional differences in lung injury and edema is unknown. To test whether regional differences in pulmonary perfusion are associated with regional differences in microvascular function during lung injury, pigs were mechanically ventilated in the prone position and infused with endotoxin (Escherichia coli 055:B5, 0.15 microg. kg(-1). h(-1); n = 8) or saline (n = 4) for 4 h. Extravascular albumin accumulation and perfusion were measured in multiple approximately 0.7-ml lung regions by injecting pigs with radiolabeled albumin and radioactive microspheres, respectively. Extravascular albumin accumulation was spatially heterogeneous but not correlated with regional perfusion. Extravascular albumin accumulation was greater in dorsal than ventral regions, and regions with similar albumin accumulation were spatially clustered. This spatial organization was less evident in endotoxemic than control pigs. We conclude that there are regional differences in lung albumin accumulation that are spatially organized but not mediated by regional differences in pulmonary perfusion. We speculate that regional differences in microvascular pressure or endothelial function may account for the observed distribution of extravascular albumin accumulation.


Related Concept Videos
 01:20
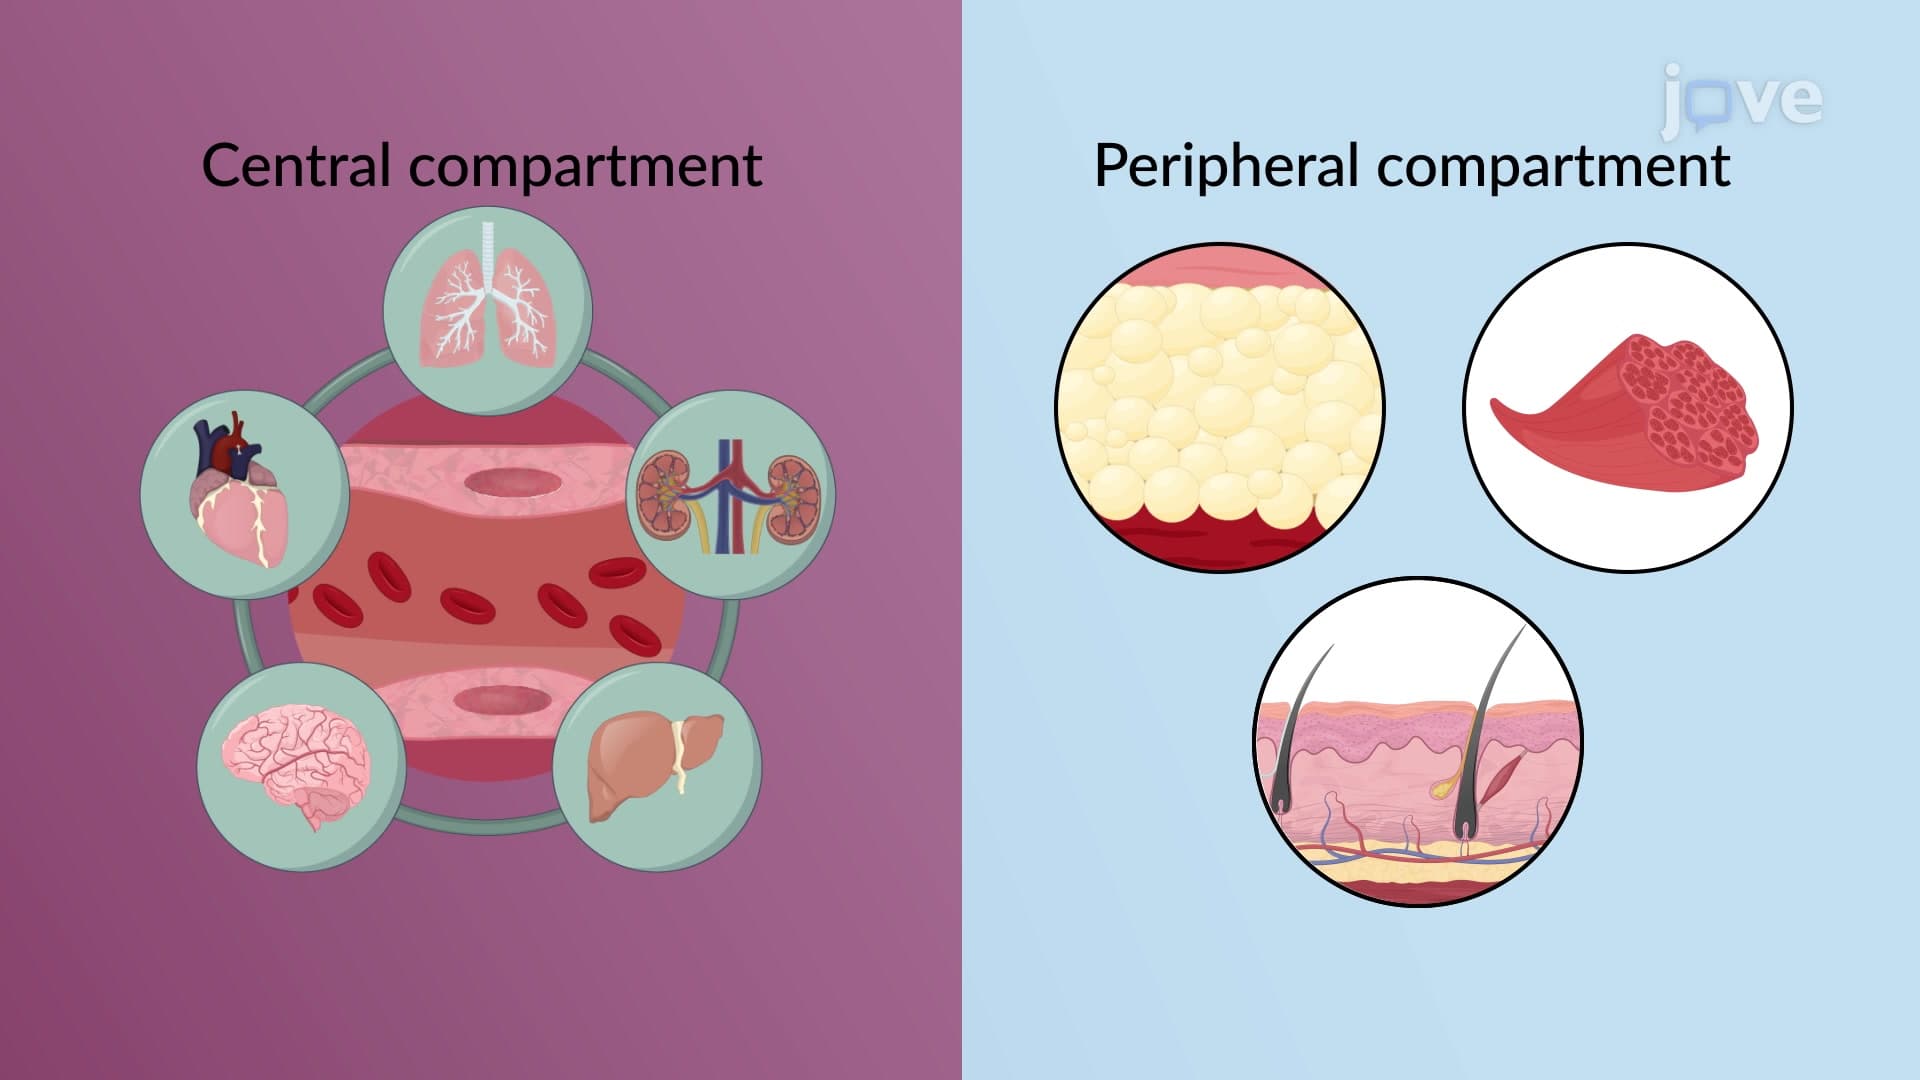
Compartment Models: Two-Compartment Model
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:15
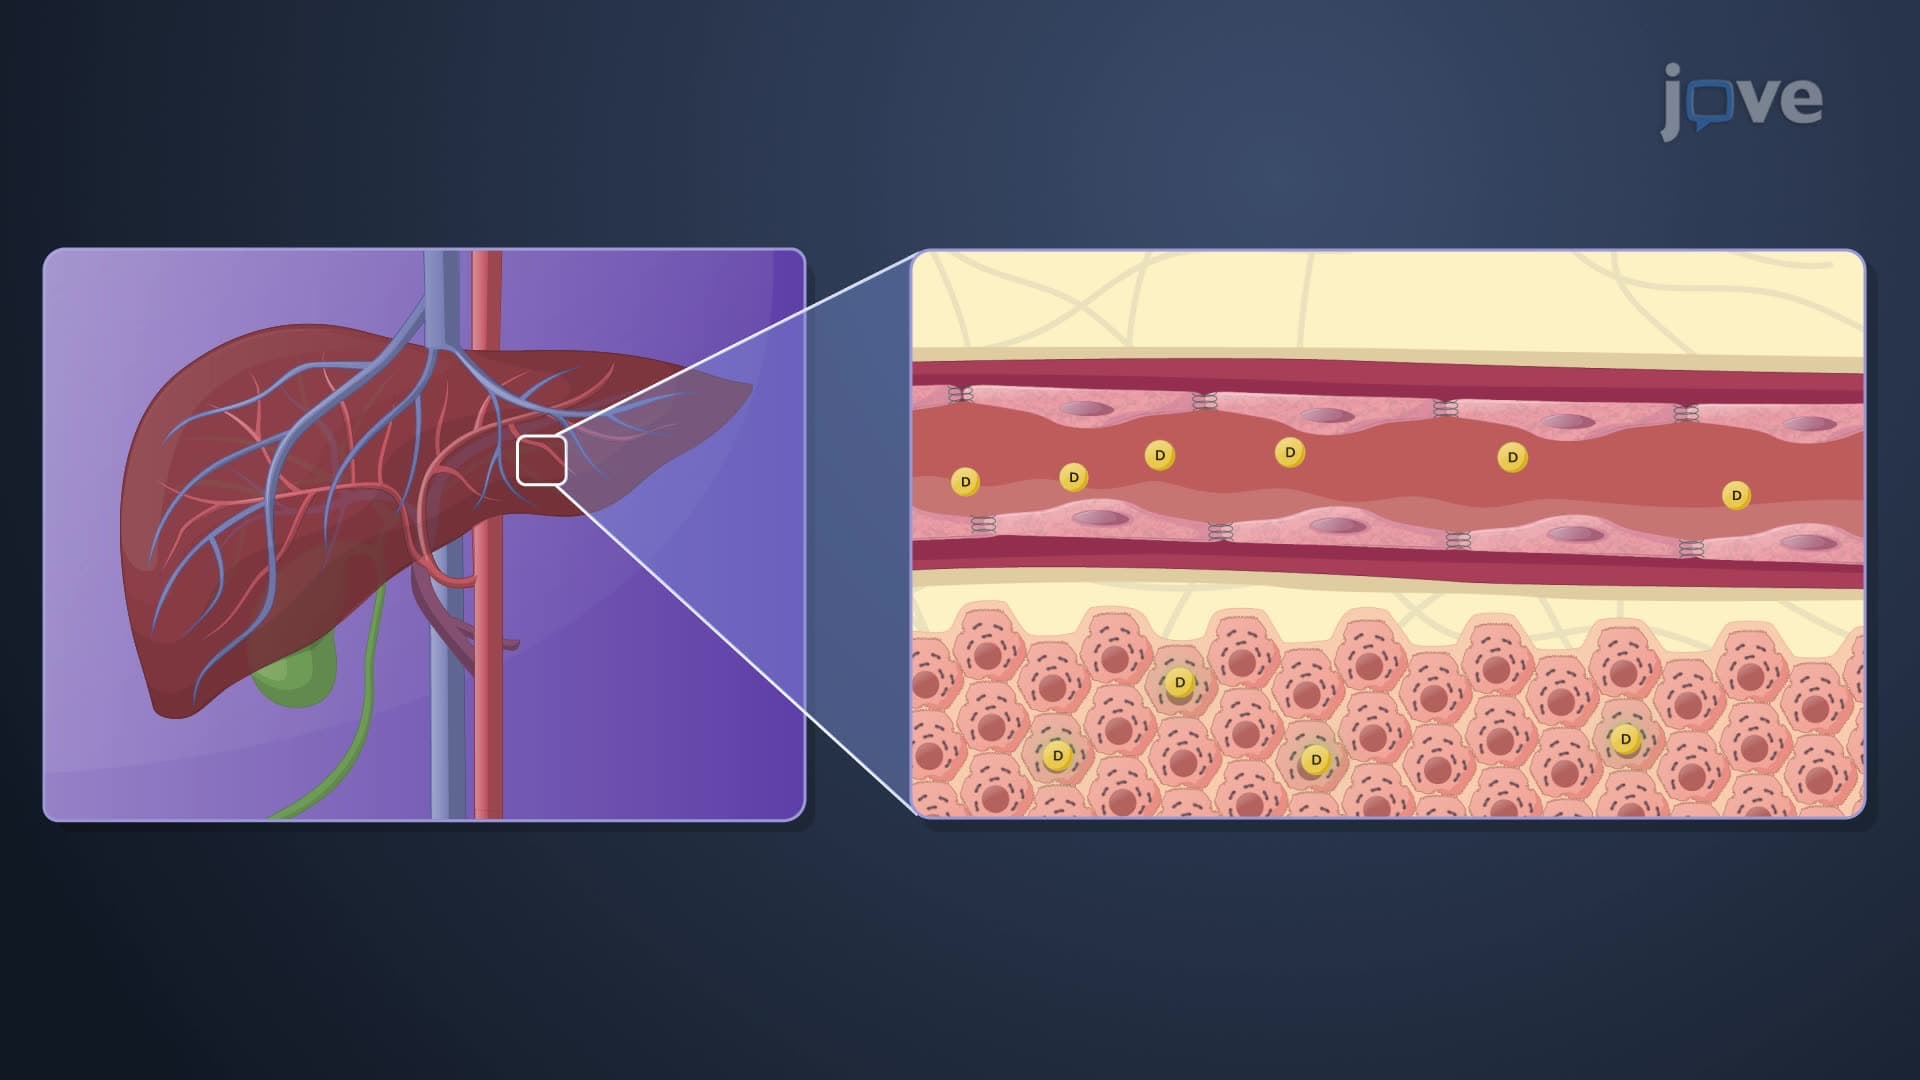
Factors Affecting Drug Distribution: Organ Perfusion Rate
Perfusion rate-limited distribution relies on the...
 01:10
Atelectasis II: Pathophysiology