Related Experiment Video
Updated: Oct 3, 2026


Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
Quantitative analysis of end-tidal carbon dioxide during mechanical and spontaneous ventilation in infants and young
1Department of Pediatrics, Veterans General Hospital, Kaohsiung, Taiwan. Kshsieh@Isca.vghks.gov.tw

Abstract:
Capnography provides a substitute for monitoring of arterial carbon dioxide tension (PCO(2)). We performed a prospective study to evaluate a new application of capnography, using quantitative curve analysis in the pediatric ICU. Twenty-five infants and children admitted to the pediatric ICU after cardiovascular surgery for congenital heart diseases were included in the study. Capnographic curves were recorded during 3 phases of mechanical and spontaneous ventilation: phase 1, immediate postoperative period; phase 3, preextubation period; and phase 2, period between phases 1 and 3. Each recording included 17 sec of capnographic tracings from consecutive spontaneous and/or ventilator-driven breaths. Quantitative curve analysis was made to define parameters including peak value of exhaled PCO(2) (P), mean rate of rise of PCO(2) (R), and area under each capnographic curve (A). Qualitative inspection of the wave contour showed no obvious difference in phase 3 during spontaneous and mechanically assisted ventilator breaths. However, an obvious difference existed between spontaneous and mechanically assisted breaths in phase 2. For each parameter (P, R, and A), there was a significant difference in phases 2 and 3 from spontaneous breaths. However, there was no significant difference in phases 2 and 3 from ventilator-assisted breaths. We further calculated the ratio of parameters of spontaneous breaths (S) and ventilator-assisted breaths (V) in phase 2 and phase 3. The ratio of S/V for P, R, and A showed significant differences between phase 2 and phase 3. We conclude that quantitative analysis of exhaled end-tidal PCO(2) curves revealed significant changes of specific parameters during the transition from the ventilator-dependent state to the spontaneously breathing ventilator-independent state. This new approach provides a new way to estimate respiratory status in infants and children receiving ventilator therapy. Through quantitative capnographic curve analysis, if P, R, and A from spontaneous breaths approached those of ventilator-assisted breaths, patients have resumed reasonable pulmonary mechanics, and extubation may then be considered.

Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:22
Respiratory Volumes and Capacities
 01:29
Mechanical Ventilation I: Indication and Settings
 01:15
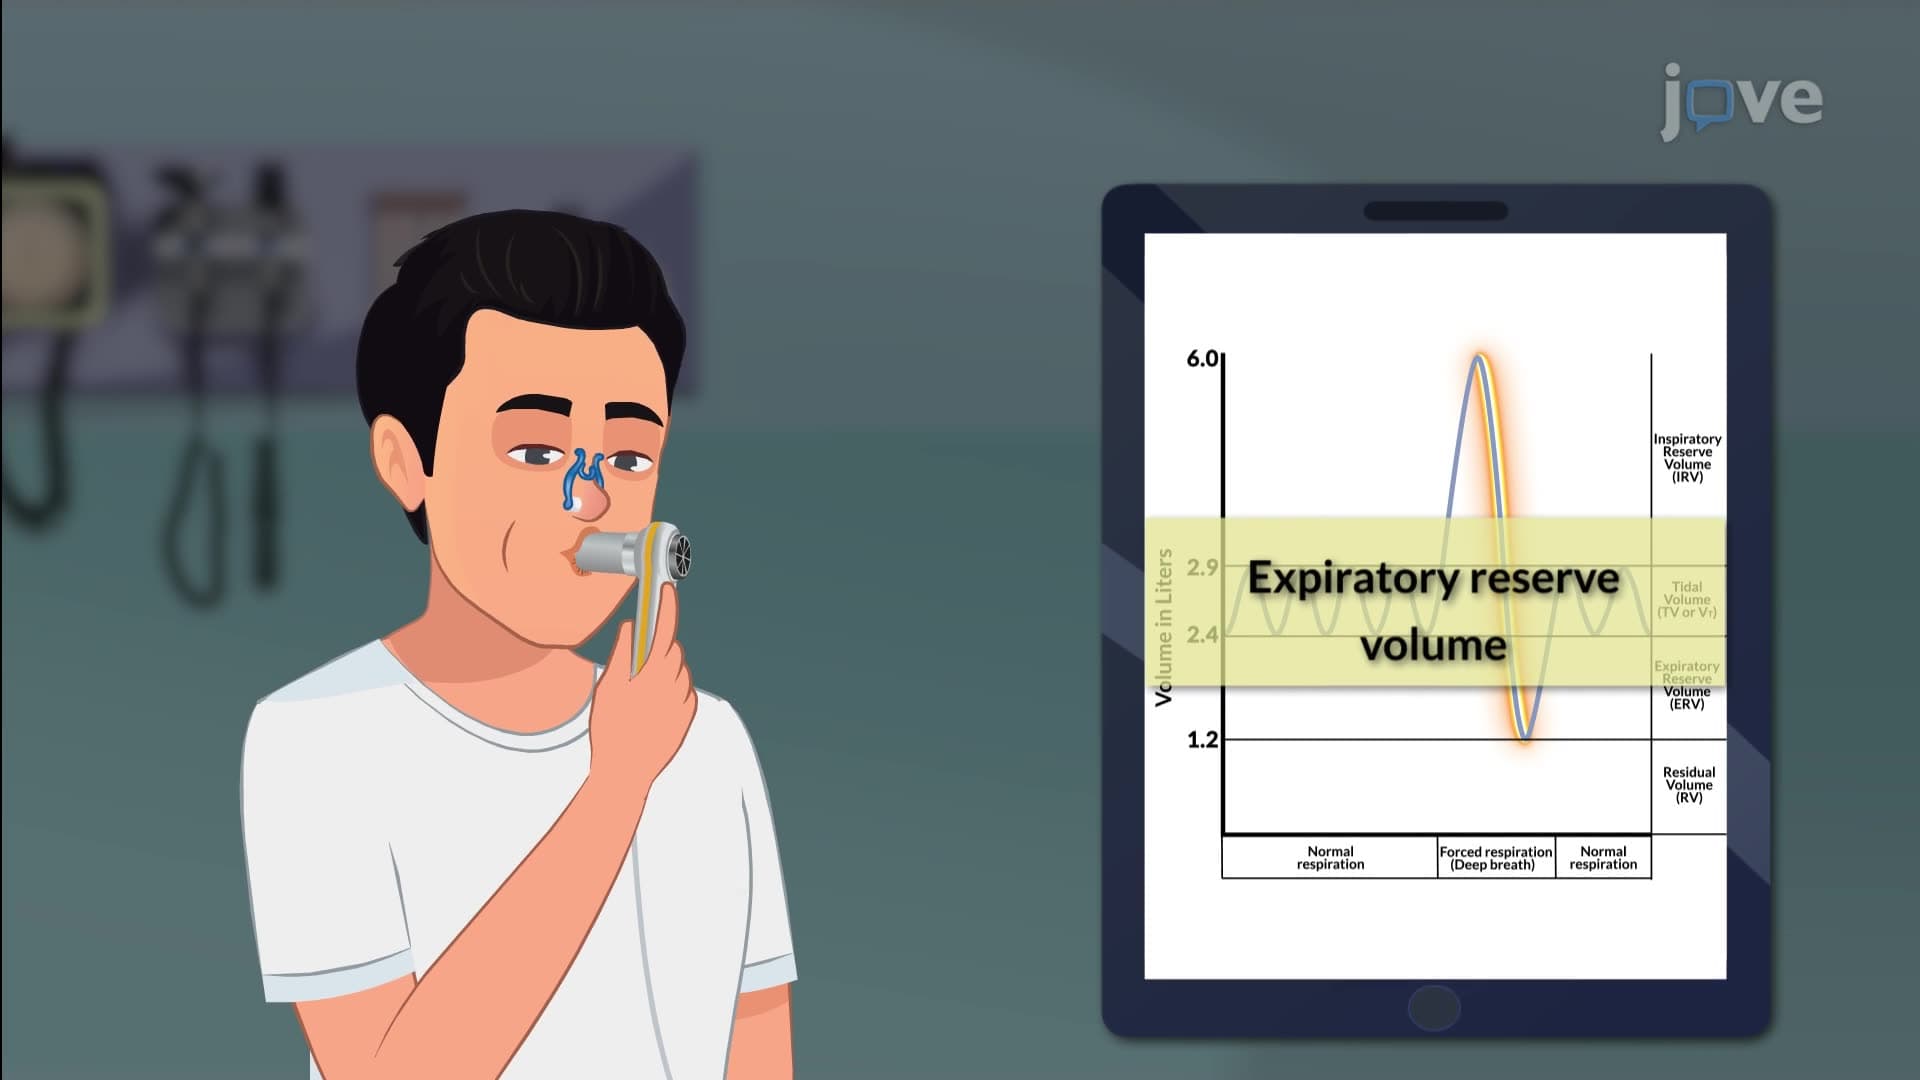
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...