Related Experiment Video
Updated: Oct 5, 2026
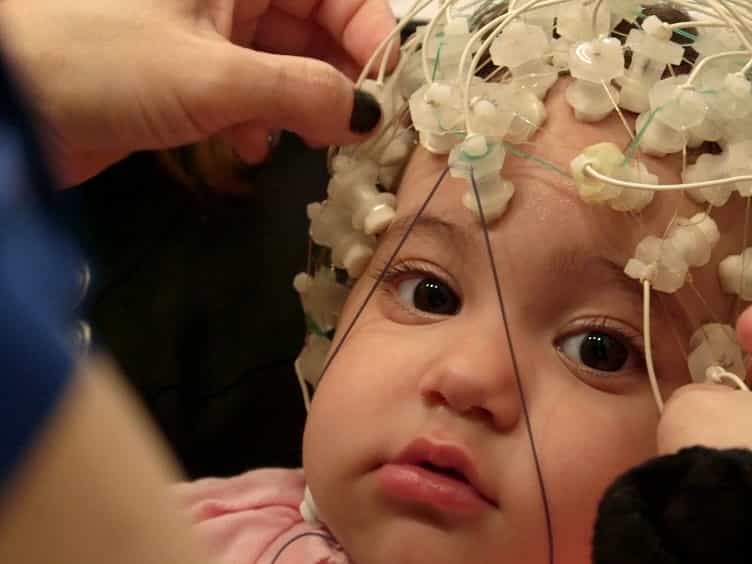
Infant Auditory Processing and Event-related Brain Oscillations
Published on: July 1, 2015
Temporal Dynamics and Clinical Relevance of Oscillatory Amplitude Variability During High-Frequency Oscillatory
Kamal Ali1,2,3, Mesaed Alsenani1,2, Saad Alshareedah1,2
1Neonatal Intensive Care Department, King Abdulaziz Medical City, Riyadh, Saudi Arabia.

Objective:
To characterise temporal dynamics, variance structure, determinants, and predictive relevance of oscillatory amplitude variability during high-frequency oscillatory ventilation with volume guarantee (HFOV-VG) in preterm infants.
Methods:
Single-centre retrospective cohort study using minute-level ventilator data collected during the first 72 h of HFOV-VG. Amplitude variability was quantified using standard deviation, coefficient of variation (CV), and root mean square of successive differences (RMSSD). Temporal patterns, variance decomposition, and determinants of variability were assessed using mixed-effects modelling separating within- and between-infant effects. Predictive performance for death before discharge or moderate-to-severe bronchopulmonary dysplasia was evaluated using receiver operating characteristic analysis.
Results:
A total of 237,790 measurements from 60 infants were analysed. Amplitude CV declined from 0.122 (0.072-0.160) at 0-6 h to 0.063 (0.035-0.106) at 48-72 h, while RMSSD decreased from 2.10 (1.22-2.69) to 1.13 (0.64-1.94). Variability was predominantly within-infant (ICC 0.246-0.282), whereas mean amplitude, VThf/kg, and frequency were predominantly between-infant. Within-infant increases in oscillatory frequency were associated with higher variability, whereas increases in mean airway pressure and time from HFOV initiation were associated with lower variability. The composite outcome occurred in 47/60 infants. Early oscillatory amplitude variability demonstrated moderate discrimination (AUC 0.72, 95% CI 0.55-0.86), with an AUC of 0.82 (95% CI 0.66-0.95) when combined with oscillatory frequency and weight-normalised DCO2.
Conclusions:
Oscillatory amplitude variability during HFOV-VG reflects dynamic ventilator-lung interactions. Its association with adverse respiratory outcome is hypothesis-generating and requires validation in larger independent cohorts.
Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:29
Mechanical Ventilation I: Indication and Settings