Related Experiment Video
Updated: Sep 25, 2026


Phase-Resolved Functional Lung MRI for Pulmonary Ventilation and Perfusion (V/Q) Assessment
Published on: August 9, 2024
Cardiorespiratory coupling during high-frequency oscillatory ventilation with volume guarantee in extremely preterm
Kamal Ali1,2,3, Abdulaziz Homedi1,2,3, Musab Alshareef1
1Neonatal Intensive Care Department, King Abdulaziz Medical City, Riyadh, Saudi Arabia.

Abstract:
This study aims to evaluate associations between PCA-derived cardiovascular components and respiratory burden during high-frequency oscillatory ventilation with volume guarantee (HFOV-VG). This retrospective cohort study included infants born before 30 weeks of gestation who received HFOV-VG and underwent targeted neonatal echocardiography during respiratory support. Echocardiography assessed ventricular systolic function, cardiac output, myocardial deformation, and pulmonary vascular loading. Principal component analysis (PCA) derived integrated cardiovascular components. Multivariate regression models evaluated associations with respiratory support, haemodynamic support, and clinical outcomes, including mortality, moderate-to-severe bronchopulmonary dysplasia (BPD), and the composite outcome of death or moderate-to-severe BPD. Sixty-two infants were included (gestational age 26.0 [25.0-27.0] weeks; birth weight 860 [700-1000] g). Median FiO₂ during HFOV-VG was 0.35 (0.31-0.52). Right ventricular strain demonstrated the strongest association with FiO₂ (rho = 0.53, q < 0.001). The first principal component (PC1), representing a cardiopulmonary loading component characterised by less favourable ventricular performance, reduced cardiac output, altered myocardial deformation, and increased septal loading, explained 65.9% of echocardiographic variance. Each one standard deviation increase in PC1 was associated with a 0.60 standard deviation increase in FiO₂ (95% CI 0.38-0.82; p < 0.001). Higher PC1 was independently associated with mortality (OR 3.01, 95% CI 1.44-6.29; p = 0.004), higher peak vasoactive-inotropic score, longer inotropic support, increased odds of inotrope use, and lower odds of haemodynamically significant patent ductus arteriosus (all p < 0.05).
Conclusion:
In preterm infants receiving HFOV-VG, the first cardiovascular principal component was independently associated with oxygenation burden, haemodynamic support requirements, and mortality. PCA-derived cardiovascular assessment may complement conventional respiratory assessment during HFOV-VG.
What Is Known:
• Oxygenation during high-frequency oscillatory ventilation is influenced by both respiratory and cardiovascular factors. • Targeted neonatal echocardioghraphy can assess multiple aspects of cardiovascular function, but most studies have evaluated individual haemodynamic variables rather than integrated cardiovascular profiles.
What Is New:
• Exploratory principal component analysis identified a cardiovascular component independently associated with oxygen requirements during HFOV-VG. • The first principal component was independently associated with oxygenation burden, haemodynamic support requirements, and mortality, supporting an integrated cardiorespiratory approach to physiological assessment during HFOV-VG.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:15
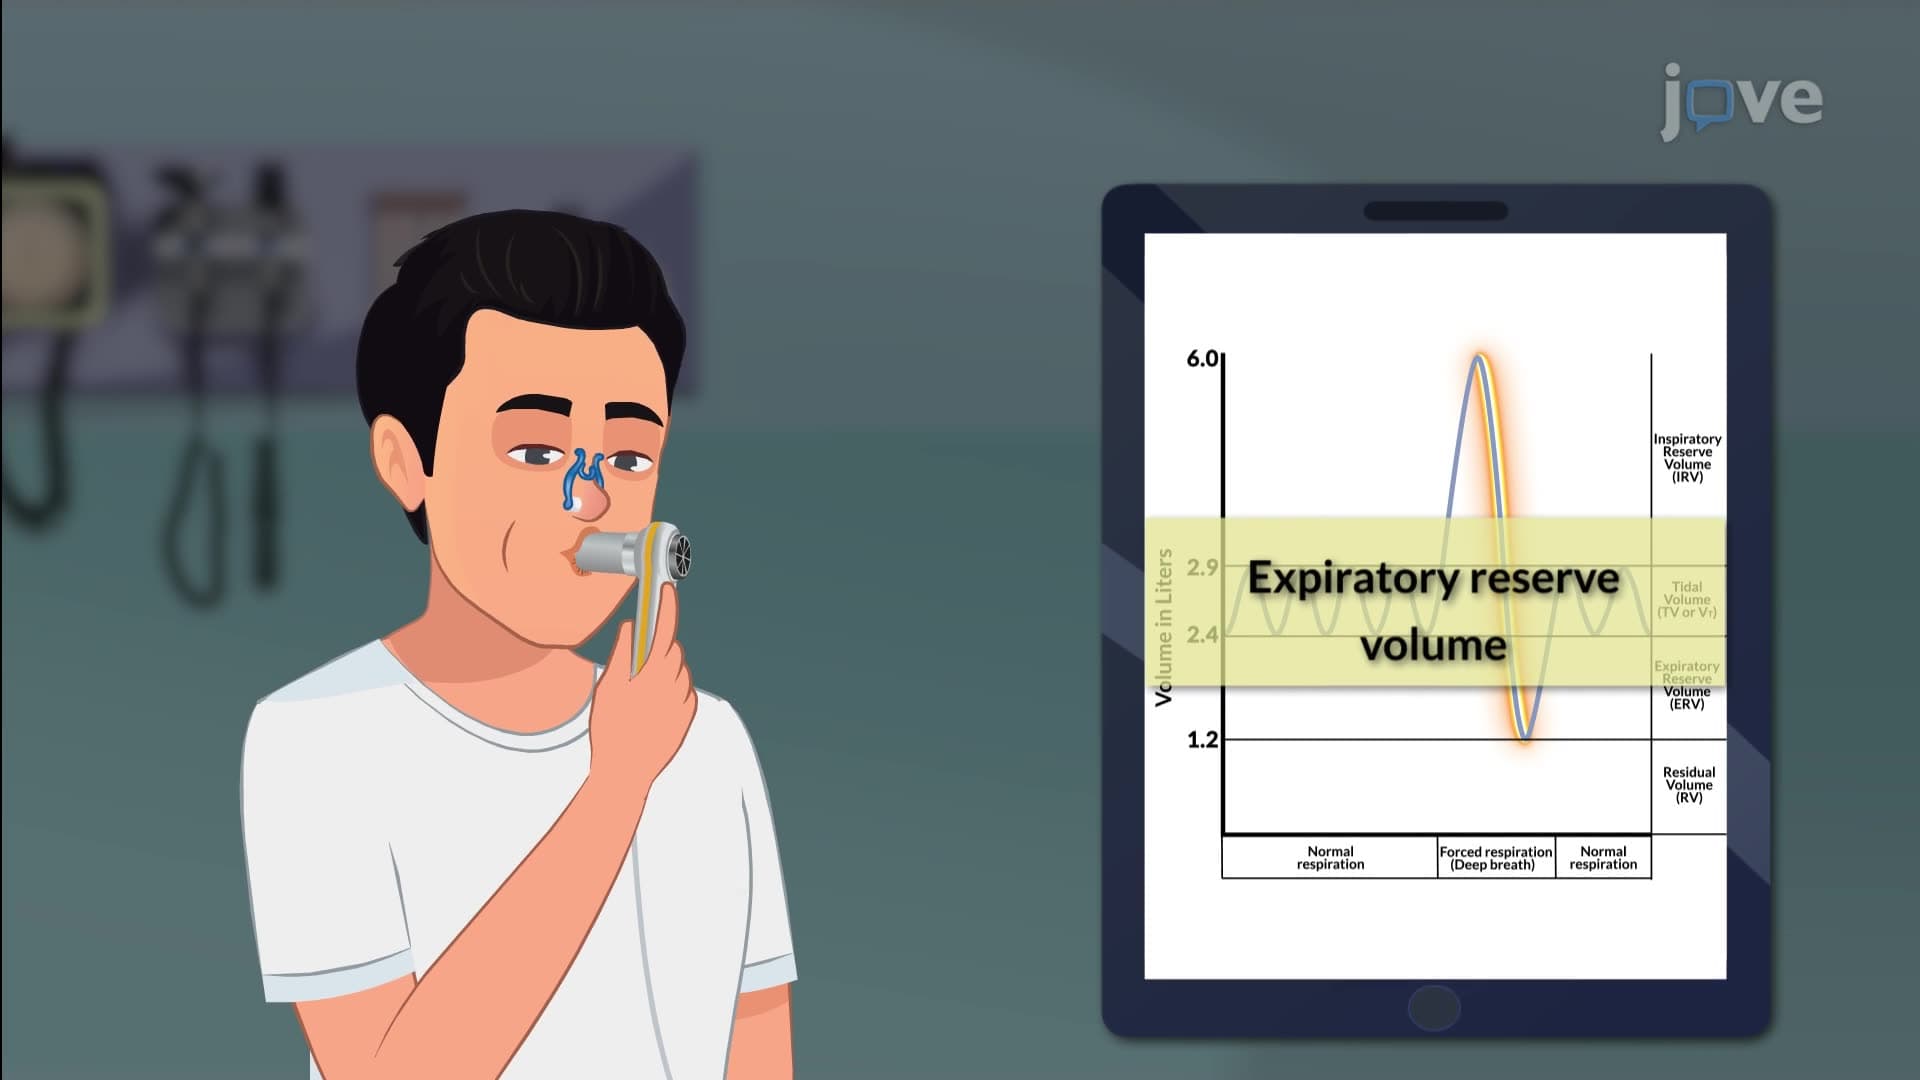
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:26
Respiratory Volumes and Capacities I
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: