Related Experiment Video
Updated: Oct 3, 2026

Generation of a Mouse Spontaneous Autoimmune Thyroiditis Model
Published on: March 17, 2023
Reference intervals from birth to adulthood for serum thyroxine (T4), triiodothyronine (T3), free T3, free T4,
M W Elmlinger1, W Kühnel, H G Lambrecht
1University Children's Hospital, Paediatric Endocrinology Section, Tuebingen, Germany. martin.elmlinger@med.uni-tuebingen.de

Insights
Establishing pediatric thyroid hormone reference intervals is crucial for development. This study provides new reference ranges for thyroid-stimulating hormone (TSH) and thyroid hormones from birth to adulthood using automated chemiluminescence immunoassay.
Area of Science:
- Pediatric Endocrinology
- Clinical Chemistry
- Immunoassay Technology
Background:
- Thyroid dysfunction can significantly impact child development.
- Establishing accurate reference intervals for thyroid hormones is essential for diagnosis and management in pediatric populations.
- Existing reference ranges may not adequately cover the dynamic changes from birth through adolescence.
Purpose of the Study:
- To establish comprehensive reference intervals for key thyroid hormones and thyrotropin (TSH) in euthyroid individuals from birth to adulthood.
- To utilize the automated chemiluminescence immunoassay system (Immulite) for reliable and standardized measurements.
- To provide age- and sex-specific reference data for clinical assessment.
Main Methods:
- Serum samples from 762 euthyroid newborns, children, and adolescents (1 day to 19 years) were analyzed.
- Measurements included triiodothyronine (T3), free T3 (fT3), thyroxine (T4), free T4 (fT4), thyroxine binding globulin (TBG), and TSH.
- Non-normal distribution necessitated the calculation of 2.5th, 50th, and 97.5th percentiles for central 95% intervals.
Main Results:
- Thyroid hormone and TSH concentrations showed significant variations, with higher medians in the neonatal period (up to 3.2-fold).
- Thyroxine (T4) levels increased in the first month of life.
- Thyroxine binding globulin (TBG) increased with age, peaking around 5 years, while other parameters generally decreased from 1 year onwards. No significant sex differences were observed.
Conclusions:
- Reference intervals for thyroid hormones and TSH vary considerably after the neonatal period and across childhood and adolescence.
- The established reference intervals are applicable for assessing thyroid status in pediatric patients using the Immulite/Immulite 2000 system.
- Thyroid hormone levels do not correlate with sexual development, with the exception of a slight decrease in TBG during puberty.
Abstract:
Disorders in thyroid function can impair normal development in children. Therefore it was our aim to establish reference intervals for serum triiodothyronine (T3), free T3 (fT3), thyroxine (T4), free T4 (fT4), thyroxine binding globulin (TBG) and thyrotropin (TSH) which are applicable from birth to adulthood by using the non-isotopic automated chemiluminescence immunoassay system, Immulite (DPC Los Angeles, USA). Serum samples from 762 euthyroid newborns, children and adolescents (369 female, 393 male; age 1 day to 19 years) were examined; of these, 381 were classified as pubertal. Due to non-normal distribution, the 2.5th, 50th and 97.5th percentiles (the central 95% interval) were calculated for each group. The median concentrations of T4, fT4 and TSH were up to 3.2-fold higher during the first 2 weeks, while T4 increased during the first month of life. The concentrations in all age groups showed no sex differences. From 1 year onwards, the concentration of all parameters tended to decrease until adult age, with the exception of TBG which increased by >60% (p<0.02) and reached a maximum at approximately 5 years of age. The findings underscore the fact that thyroid hormones are not associated with sexual development, except for TBG, which decreased slightly (p<0.04) between Tanner stages 1 and 5. However, the reference intervals established here demonstrate that marked changes occur in concentrations of thyroid hormones after the neonatal period. Our findings complement these of earlier studies. The developed reference intervals can be used to assess the thyroid status of patients, particularly if the measurements are done on the Immulite/Immulite 2000 system.
Related Concept Videos
 01:20
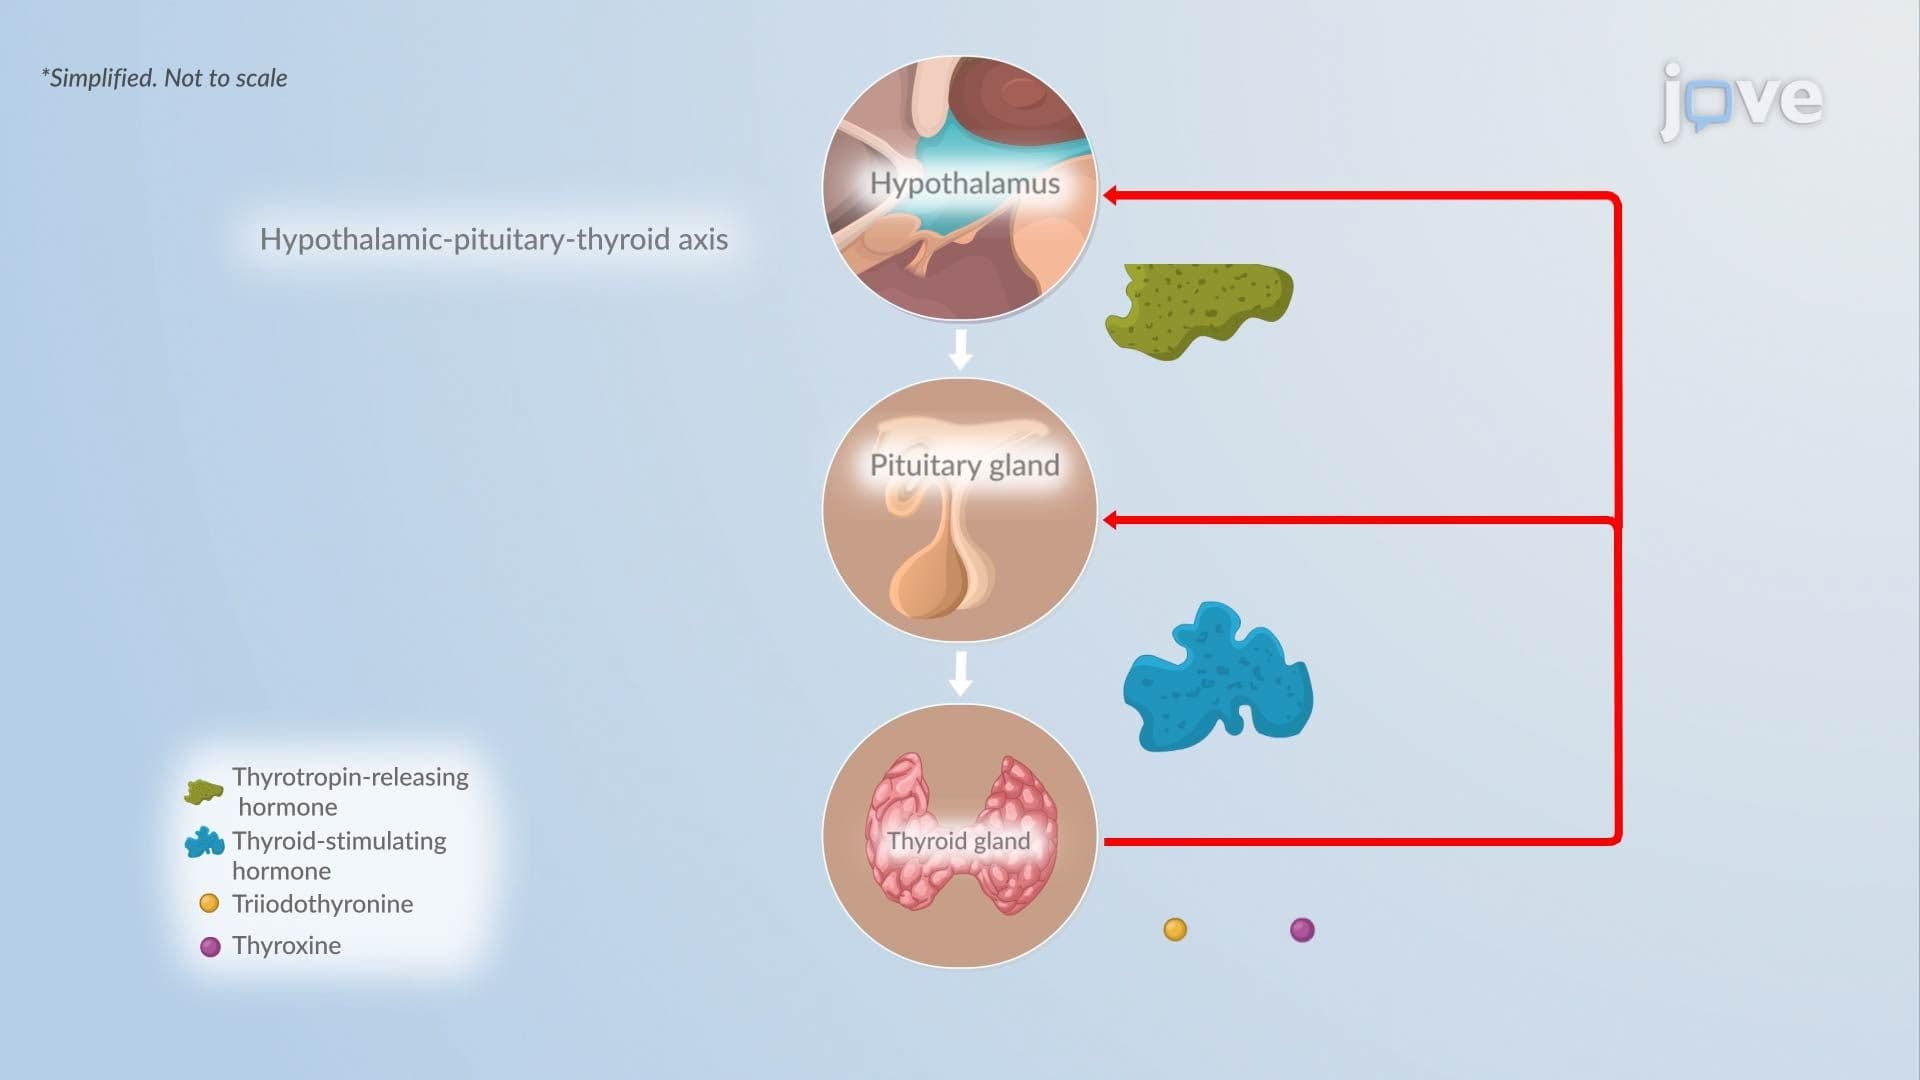
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:25
Hyperthyroidism I: Introduction
 01:27
Goiter
 01:27
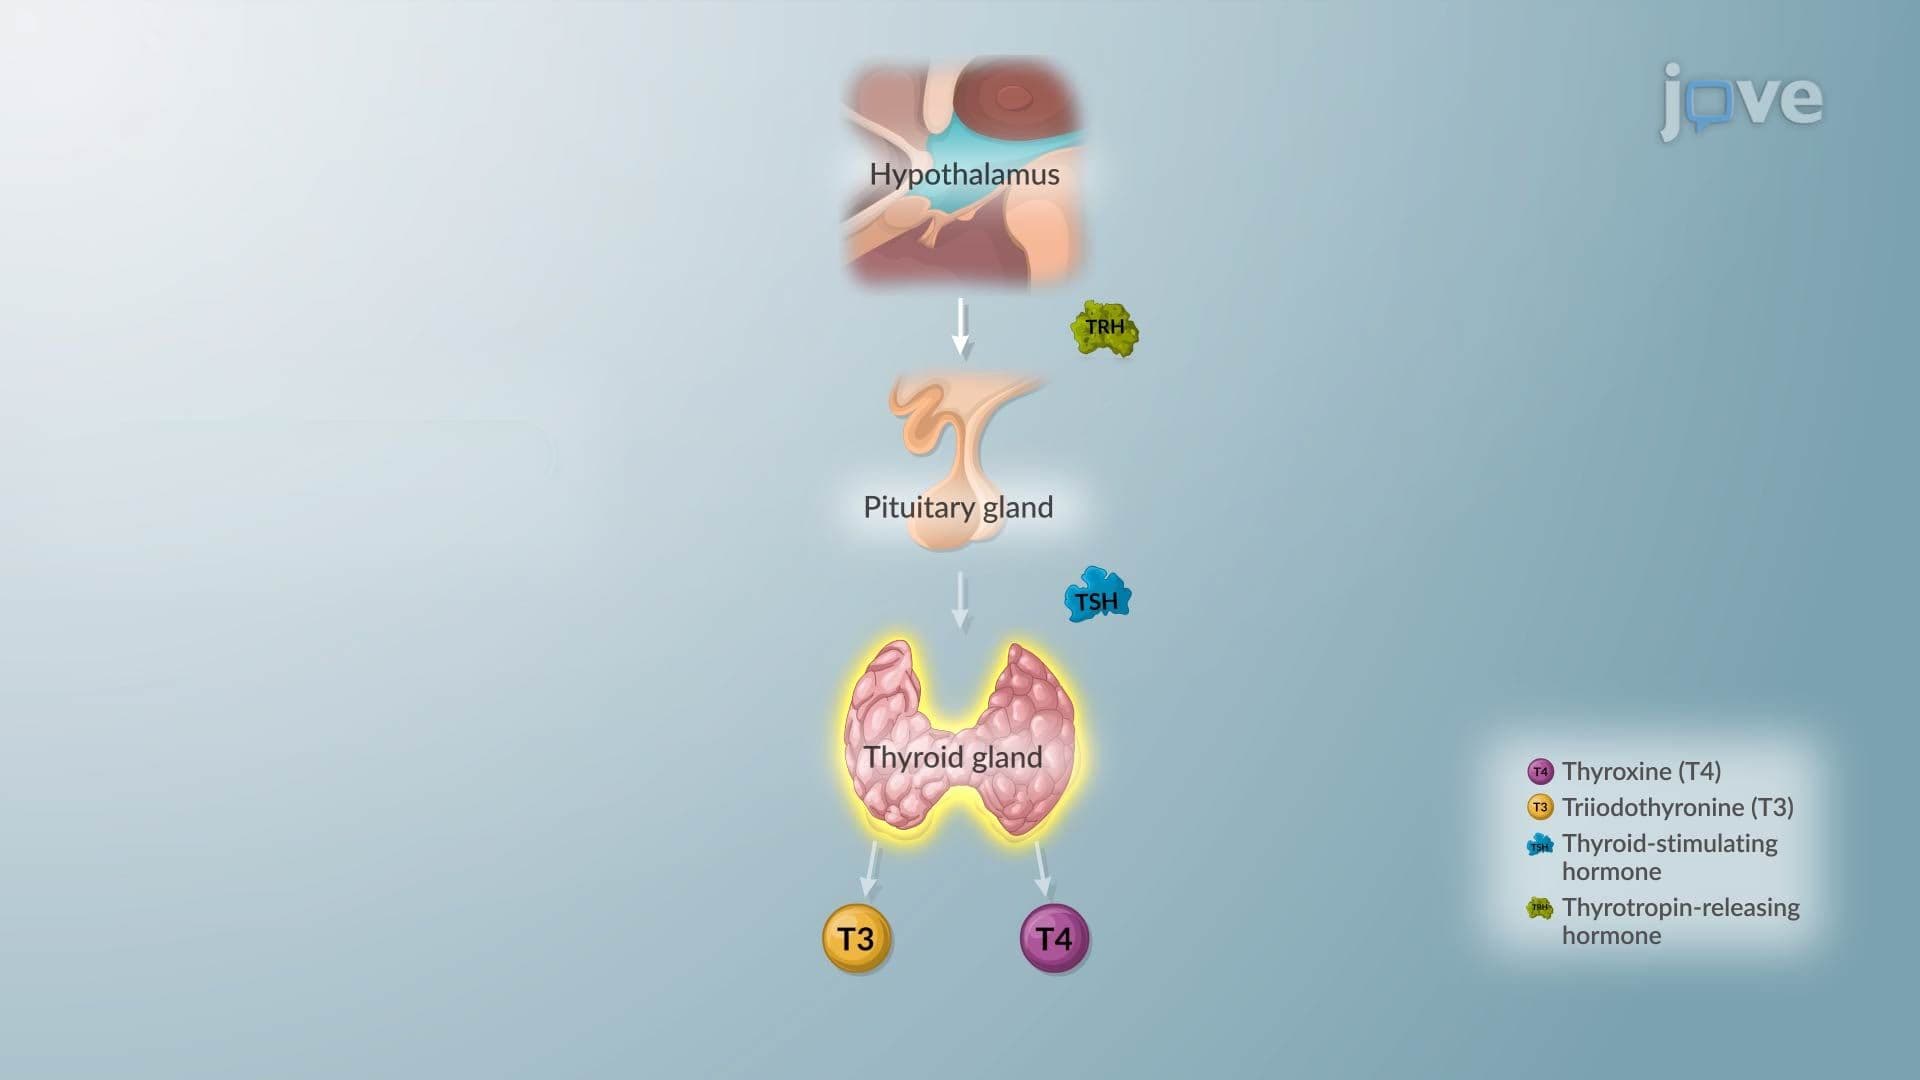
Hyperthyroidism II: Pathophysiology
 01:23
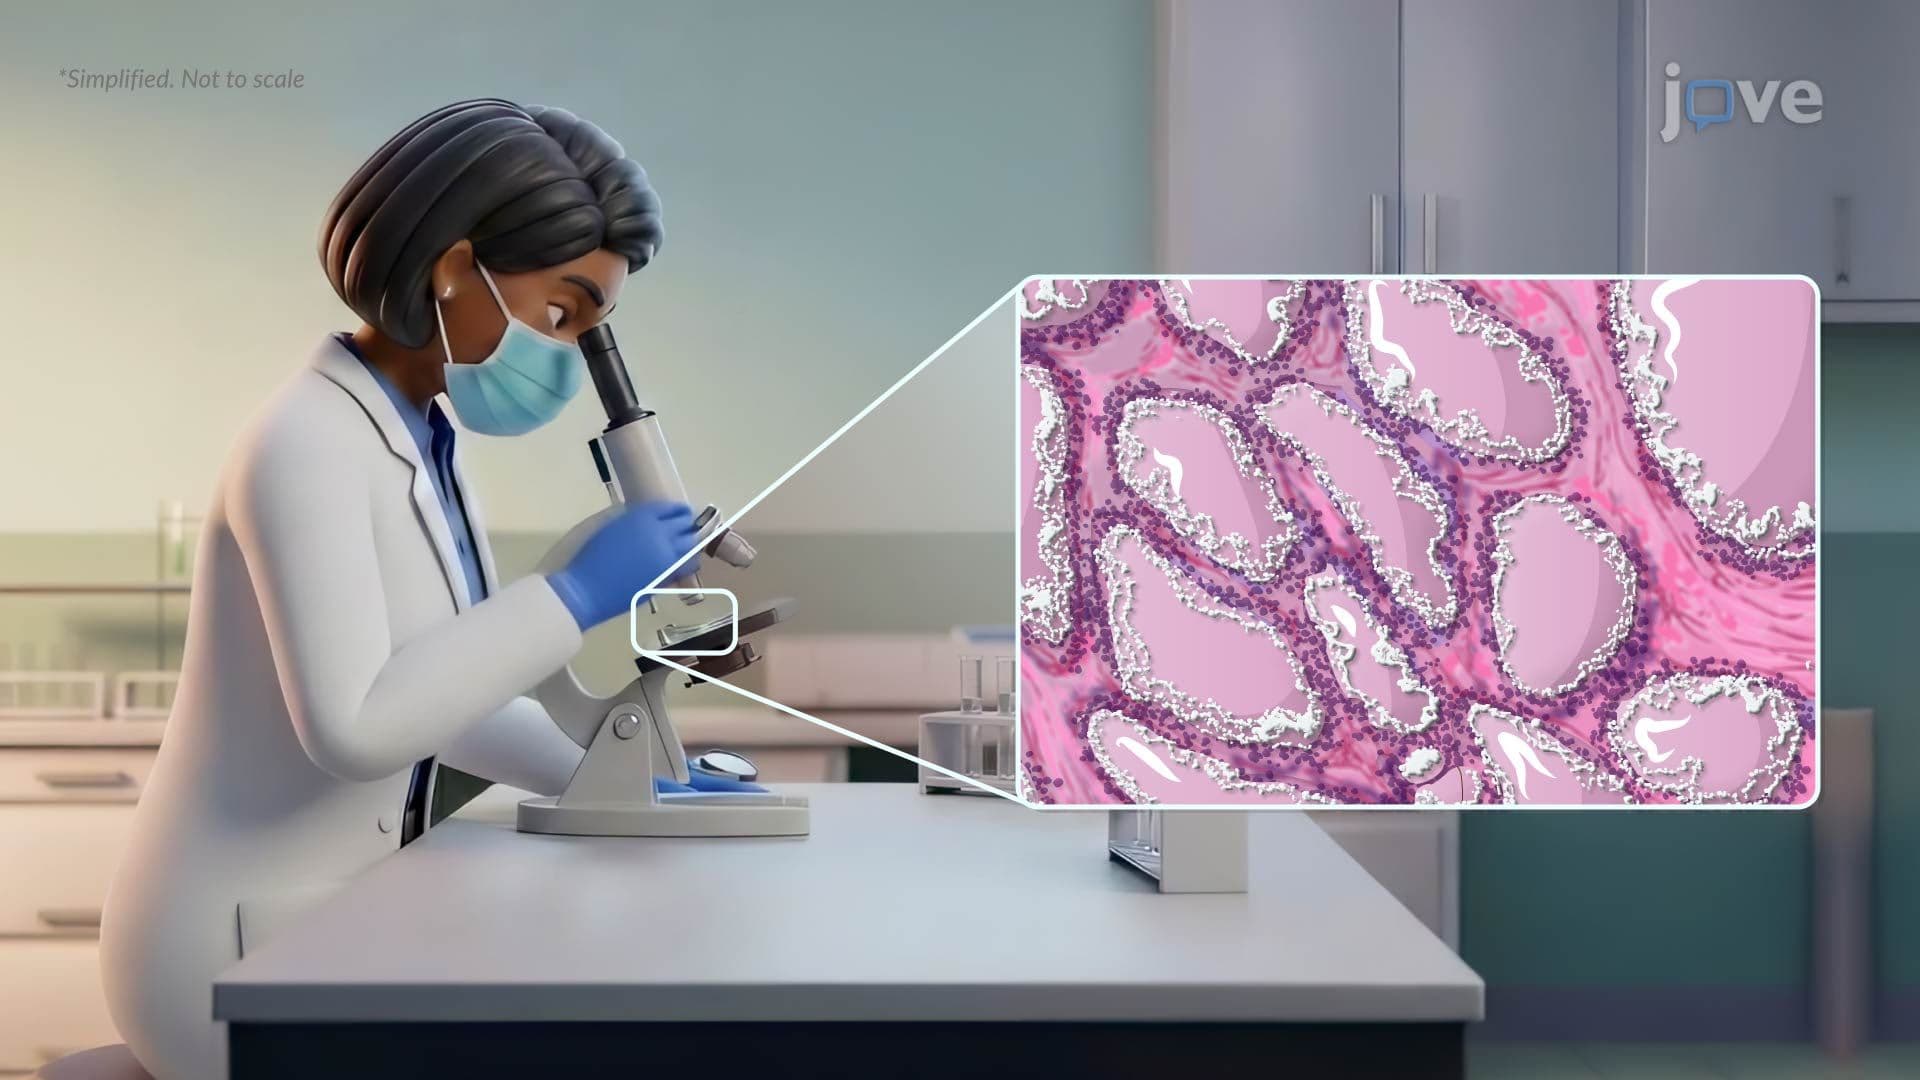
Hypothyroidism II: Pathophysiology
 01:24
Graves Disease II: Pathophysiology