Related Experiment Video
Updated: Jul 25, 2026
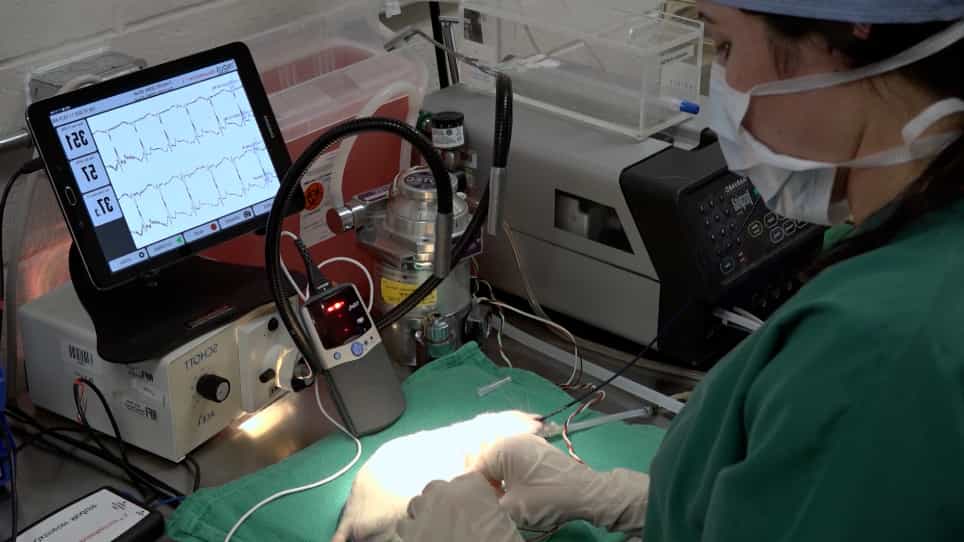

An Image Guided Transapical Mitral Valve Leaflet Puncture Model of Controlled Volume Overload from Mitral Regurgitation in the Rat
Published on: May 19, 2020
Mitral regurgitation after partial left ventriculectomy as the cause of ventricular redilatation
A T Kawaguchi1, L O Bocchino, S Shimura
1Tokai University School of Medicine, Bohseidai, Isehara, Japan. akira@is.icc.u-tokai.ac.jp

Background:
It remains unclear whether ventricular redilatation after partial left ventriculectomy (PLV) is due to underlying pathology or to continued volume overload amenable to surgery.
Methods:
Among patients undergoing PLV, 32 had Doppler echocardiography preoperatively, immediately after surgery (< 1 week), early after surgery (1-3 months), and late after surgery (8-14 months). Patients were divided into groups with mitral regurgitation (MR; MR+, n = 16) and without postoperative MR (MR-, n = 16) and were compared for ventricular size, performance, and survival.
Results:
After initial surgical reduction, left ventricular dimension on average gradually increased back to the preoperative level in subgroups of patients with valvular disease and cardiomyopathy and in all patients combined. Most patients showed drastically reduced left ventricular dimension early after PLV. In MR+ patients, dimension increased back to the preoperative level within 3 months after surgery, whereas the MR- group maintained reduced dimension throughout the first year in all patients combined and in a subgroup of patients with cardiomyopathy. Occurrence of significant MR after PLV appeared to be related to severity of fibrosis in excised myocardium but not to severity of preexisting MR, etiology, or performance of mitral valvuloplasty.
Conclusions:
Early postoperative MR, residual or new, appeared to play an important role in dictating early hemodynamics and late outcome in patients undergoing PLV. Results suggest an aggressive simultaneous approach to abolish MR. Causative role of myocardial fibrosis remains unclear and needs further study.
Insights
Mitral regurgitation (MR) after partial left ventriculectomy (PLV) significantly impacts ventricular size and patient outcomes. Addressing MR aggressively during surgery may improve long-term results.
Area of Science:
- Cardiovascular Surgery
- Cardiac Imaging
- Heart Failure Management
Background:
- Ventricular remodeling after partial left ventriculectomy (PLV) is not fully understood.
- The role of underlying pathology versus continued volume overload in ventricular redilatation requires clarification.
Purpose of the Study:
- To investigate the factors influencing ventricular redilatation post-PLV.
- To assess the impact of mitral regurgitation (MR) on ventricular dimensions and outcomes after PLV.
Main Methods:
- Doppler echocardiography was performed on 32 patients undergoing PLV at multiple time points.
- Patients were stratified into groups with (MR+) and without (MR-) postoperative mitral regurgitation.
- Ventricular size, performance, and survival were compared between MR+ and MR- groups.
Main Results:
- Left ventricular dimensions returned to preoperative levels in most patients, particularly those with valvular disease and cardiomyopathy.
- Patients with MR+ showed a rapid increase in ventricular dimension within 3 months post-surgery.
- Patients in the MR- group maintained reduced ventricular dimensions throughout the first year.
Conclusions:
- Early postoperative MR, whether residual or new, significantly influences hemodynamics and long-term outcomes after PLV.
- An aggressive, simultaneous approach to abolish MR is suggested to improve patient outcomes.
- The causative role of myocardial fibrosis in MR requires further investigation.


Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:25
Mitral Regurgitation III: Medical Management
 01:28
Mitral Regurgitation IV: Nursing Management
 01:22
Mitral Stenosis I: Introduction
 01:15
Aortic Regurgitation I: Introduction