Concentration/Effect Analysis of Antihypertensive Drugs
Related Experiment Video
Updated: Oct 2, 2026

The Antihypertensive Effects and Mechanisms of Huotan Jiedu Tongluo Decoction in Rats with H-Type Hypertension
Published on: May 17, 2024
S. Harder1, P. Thürmann, N. Rietbrock
1Department Clinical Pharmacology, University Hospital Frankfurt/Main, Germany.

Abstract:
Studies on the concentration/effect relationship of different antihypertensive agents (mainly calcium antagonists and alpha(1)-blockers) in patients confirm a close relation between plasma concentrations and the corresponding fall in blood pressure, but the heterogenity in study objectives and methodology impedes the compiling and differentiation of results. Concentration/effect analysis was established using either the linear or the E(max) model. The studies reviewed here do not speak unequivocally in favor of either one of the methodological approaches (linear or E(max) model, PK/PD modeling, placebo correction) or a certain mode of blood pressure measurement. The responsiveness parameters obtained exhibited a wide intersubject variability; thus, threshold levels derived for any of the investigated compounds can only be used to a limited extent. For drug development, a more integrated protocol should be strived for to design studies on concentration/effect relationship for antihypertensives. Although individualized dose adjustment based on concentration/effect analysis after single-dose application was applied successfully, this approach seems to be an inadequate strategy for conventional treatment of hypertension.
Related Concept Videos
 01:14
Time Course of Drug Effect
 01:15
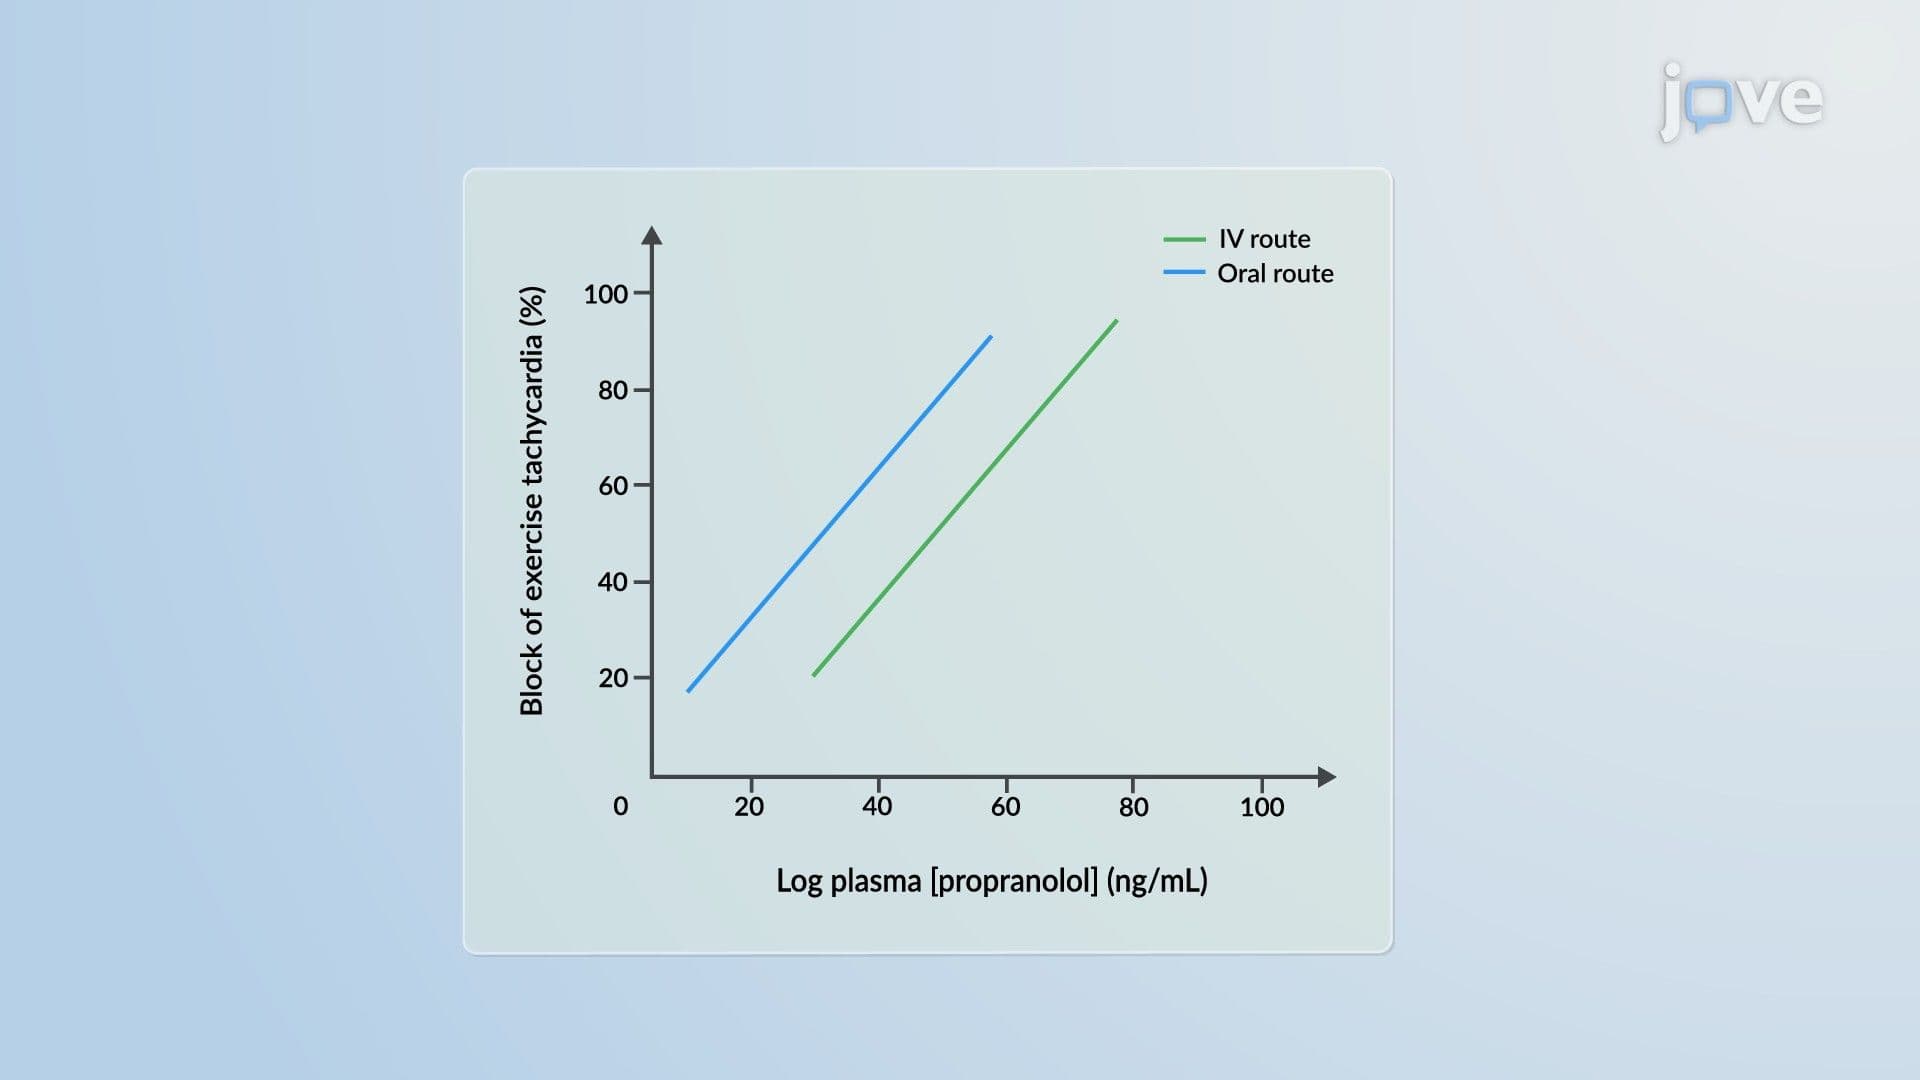
Pharmacodynamic Models: Logarithmic Concentration–Effect Model
 01:15
Pharmacodynamic Models: Linear Concentration–Effect Model
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:16
Antihypertensive Drugs: Action of Diuretics
 01:22
Dose-Response Relationship: Potency and Efficacy