Reestablishing duodenal continuity after previous gastrectomy for peptic ulcer
Related Experiment Video
Updated: Oct 9, 2026
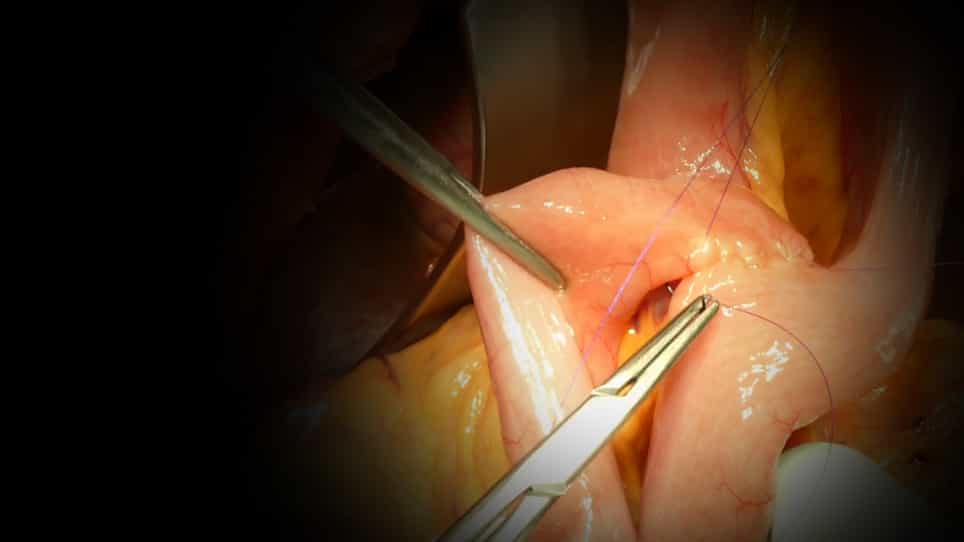
Modified Single-Loop Reconstruction for Pancreaticoduodenectomy
Published on: September 28, 2019

Abstract:
Gastroduodenal anastomosis is not routine during reoperation for stomal ulcers after primary Billroth II gastrectomy. It nevertheless is a sure way to prevent an increased peptic potential which is brought about by a duodenal bypass. We have reviewed the published cases and added three more, bringing the total to 47. We analyzed the modalities, indications and results of this method. Gastroduodenal anastomosis can be accomplished more often than is thought, despite the often necessary large gastric resections. Separation of the duodenopancreatic block and liberation of the fundus allows suturing without traction. End-to-side anastomosis of the stomach on the anterior wall of the second portion of the duodenum avoids dissection of the duodenal stump. Vagotomy is required when basal acidity is greater than 20 mEq/liter. Reestablishing a physiologic alimentary tract is particularly indicated in chronic obstruction due to stenosis associated with a proximal loop syndrome in young patients. Jejunal interposition becomes necessary when total gastrectomy is the result of repeated surgery. Such a method is the best solution for agastria. The excellent results obtained by gastroduodenal anastomosis after repeat gastrectomy should encourage wider use.
More Related Videos
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
 04:05
Endoscopic Vacuum Therapy for the Treatment of Anastomotic Leakage after Total Gastrectomy with Esophagojejunostomy
Published on: August 22, 2025
Related Concept Videos
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications