Optimizing epilepsy surgery with intraoperative MR imaging
Related Experiment Video
Updated: Oct 1, 2026
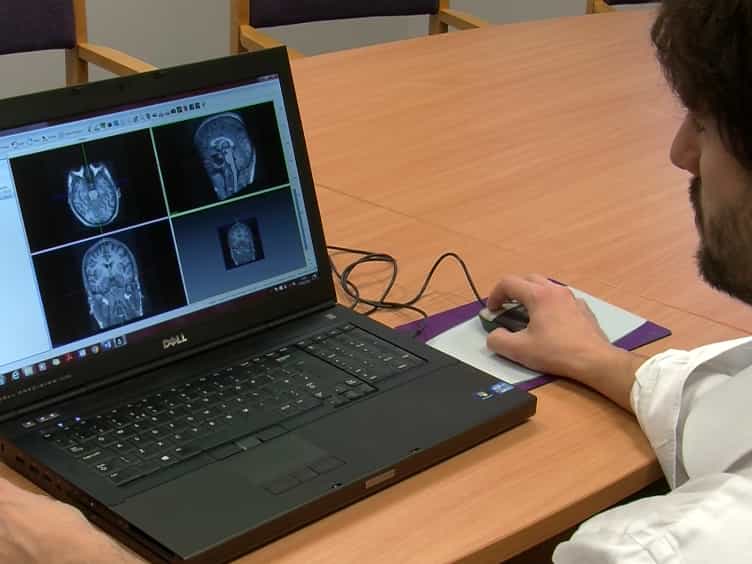
A Pipeline for 3D Multimodality Image Integration and Computer-assisted Planning in Epilepsy Surgery
Published on: May 20, 2016
Taro Kaibara1, S Terence Myles, Mary Anne Lee
1The Seaman Family MR Research Centre, Department of Clinical Neurosciences, Division of Neurosurgery, University of Calgary, Calgary, Alberta, Canada T2N 2T9.

Purpose:
The surgical treatment of medically intractable temporal lobe epilepsy includes the resection of temporal lobe structures. Although the reported seizure-free outcomes are highly variable, there is growing evidence that the extent of resection of the mesiotemporal lobe directly correlates with seizure control.
Methods:
A moveable, high-field intraoperative magnetic resonance (MR) system was used to monitor and optimize the resection of the amygdala and hippocampus in 14 epilepsy patients. Fourteen patients with intractable seizures of temporal lobe origin underwent standard preoperative investigations including MR imaging, EEG telemetry, single-photon emission computed tomography, and neuropsychologic and sodium amytal testing. Anterior temporal lobectomy was performed on 10 patients, whereas four were treated with selective amygdalohippocampectomy. Intraoperative electrocorticography was applied as required. For all procedures, the objective was to resect the amygdala completely, and hippocampus to the posterior margin of the brainstem.
Results:
Interdissection intraoperative MR imaging taken when optimal resection was thought to have been achieved revealed residual unresected amygdala or hippocampus in seven of 14 patients. An unexpected acute hematoma was found in one patient. At 17 months' follow-up, 13 (93%) of 14 patients are seizure free or have significantly improved seizure control.
Conclusions:
The mobile high-field intraoperative MR system provides high-resolution images without restriction on surgical instruments or techniques. The ability to identify and resect residual mesial temporal lobe targets before craniotomy closure is of potentially tremendous value in optimizing seizure control.
