Related Experiment Video
Updated: Sep 30, 2026
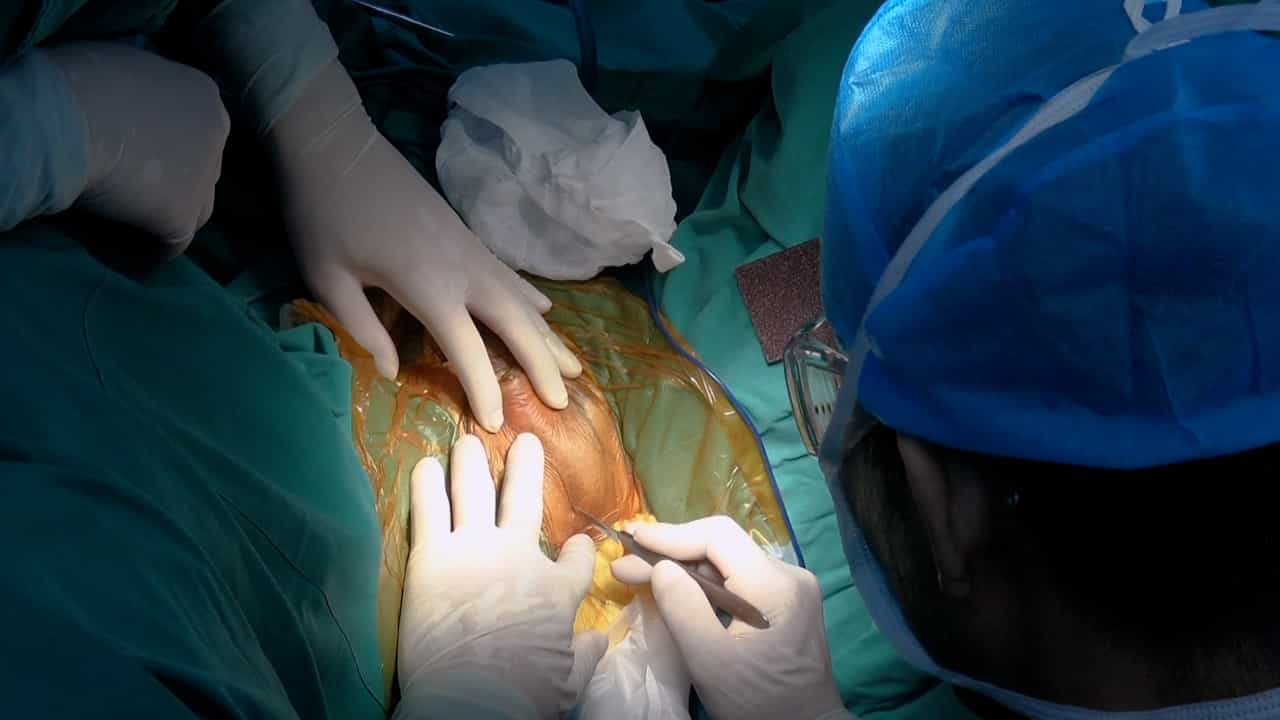

Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Grades of intrinsic sphincteric deficiency (ISD) associated with female stress urinary incontinence
G M Ghoniem1, A N Elgamasy, R Elsergany
1Section of Voiding Dysfunction and Female Urology, Cleveland Clinic Florida, Weston 33331, USA.

Abstract:
Intrinsic urethral sphincter deficiency (ISD) is a clinical entity that should be suspected in women with stress urinary incontinence. If it is not diagnosed prior to surgery, it poses a significant risk factor for repair failure. We propose a classification of ISD based on videofluorourodynamic (VFUD) and abdominal leak-point pressures. One hundred female patients with stress urinary incontinence due to ISD were included in this study. History and physical examination were performed on all patients. Each patient underwent a standard VFUD study with abdominal leak-point pressure (ALPP) measurement. ISD is classified into subtypes according to VFUDS and ALPP. The findings were then correlated with the clinical presentation, etiology and proposed management. Three types of ISD/SUI were identified. ISD-A, subtle/urodynamic, was present in 32 patients (32%). It is most difficult to diagnose because radiologically the bladder neck is not open at rest, and it is only diagnosed by VFUD. The abdominal leak-point pressure was less than 12 cmH2O. ISD-B was present in 45 patients (45%). This is characterized by a beak-shaped open bladder neck at rest. The abdominal leak-point pressure was less than 90 cmH2O. ISD-C was present in 14 patients (14%). It is characterized by an open, fixed non-functioning urethra (pipe-stem) with high position of the bladder neck. The abdominal leak-point pressure was less than 70 cmH2O. All the three subtypes had proximal urethral closure pressure (PCUP) less than 10 cmH2O. Based on these data, the treatment options may vary from one subtype to another. For ISD-A, initial treatment was medical, with collagen injection being used for the failed cases. For ISD-B a modified pubovaginal sling was used, as it corrects the ISD and the urethral hypermobility at the same time. For ISD-C, urethrolysis and takedown of the previous suspension was required before using a sling. Collagen injections were used in selected cases. This classification identifies different subgroups of ISD, which is important in the diagnosis and management of this condition.
Related Concept Videos
 01:23
Irritable Bowel Syndrome
 01:17
Irritable Bowel Syndrome I: Introduction
IBS is a chronic condition that can persist over a long period or recur frequently.
The pathogenesis of IBS involves a complex interplay of the following factors:
Altered...
 01:30
Irritable Bowel Syndrome III: Medical and Nursing Management
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating urine...