[Response of skin blood flow to several respiratory maneuvers in healthy subjects]
Related Experiment Video
Updated: Aug 10, 2026
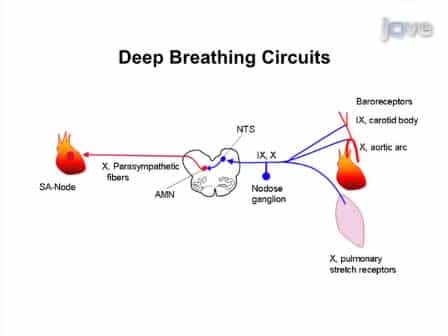
Quantitative Autonomic Testing
Published on: July 19, 2011
Shaula Mundo López1, Bruno Estañol, José Francisco Téllez Zenteno
1Departamento de Neurología y Psiquiatría Instituto Nacional de Ciencias Médicas y Nutrición, Salvador Zubirán, Vasco de Quiroga No. 15, Colonia Sección XVI Delegación Tlalpan, México, D.F.

Introduction:
In the diagnosis of autonomic disturbances, the variability of skin blood flow (SBF) and the sympathetic skin response (SSR) in response to several respiratory maneuvers are not routinely studied.
Objective:
We sought to standardize the method of SBF variability and SSR in healthy subjects during four respiratory maneuvers: 1) spontaneous breathing (SB); 2) rhythmic breathing at a rate of 6 per minute (RB); 3) sudden deep inspiration (SDI); 4) Valsalva maneuver (VM). SUBJECTS, MATERIAL AND METHOD: We studied 30 healthy subjects with a mean age of 32 years, 60% were men and 40% women. We used a photopletysmograph in the finger pad to measure SBF and surface electrodes on the palms of the hand to register the SSR. We also recorded the ECG and the respiratory movements. The variables were: 1) amplitude of SBF; 2) latency and duration of SSR; 3) percentage of decrease of the SBF during the maneuvers compared with the basal flow.
Results:
During spontaneous breathing there was no respiratory modulation of the SBF and during RB the SBF was modulated with respiration. With SDI there was a 60% decrease of the SBF. VM induced a larger SBF decrease of 72 per cent. A significant statistical difference was revealed when we compared the decrease of SBF basal breathing with SDI and VM (P < 0.001). The difference was also significant between the SDI and VM (P < 0.001). The SBF decrease recovered more slowly after the SDI (beat 7) than after the VM (veat 6). The SBF decrease was more pronounced in magnitude during the VM. The latency of the SSR appears spontaneously and at random in 57% of subjects during normal breathing but it appeared consistently during RB, SDI, and VM. The latency of SSR was longer during SB (1.7 +/- 0.7 s), RB (1.6 +/- 0.7 s) than SDI (0.7 +/- 0.5 s) and VM (0.8 +/- 0.9 s) (P > 0.050). Duration of the SSR was significantly longer in the SDI (around 7.8 +/- 2.4 s) and during the VM (8 +/- 2.5 s) as compared to normal breathing (6.3 +/- 1.0 s) and RB (6.4 +/- 1.5 s) (P < 0.009).
Conclusions:
SB and RB induce periodic modulation of sympathetic activity to skin blood vessels and sweat glands. SDI and VM produced a much greater activation of sympathetic skin activity than SB and RB. The increased SSR duration and the profound SBF decrease with SDI and VM as compared to SB or RB are consistent with this hypothesis. The latency of the SSR is much shorter with SDI and VM than with SB or RB. The most likely explanation is that the SSR, under these circumstances, results from a central command. The recovery to normal SBF is faster after the VM as compared to SDI. This suggests that the withdrawal of sympathetic responses is faster after the VM. The explanation for this is unknown but suggests that it might be baroreceptor mediated.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:35
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Related Concept Videos
 01:26
Respiratory Volumes and Capacities I
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...