Related Experiment Video
Updated: Aug 28, 2026

Intramuscular Injections Along the Motor End Plates: A Minimally Invasive Approach to Shuttle Tracers Directly into Motor Neurons
Published on: July 13, 2015
Botulinum toxin injection without electromyographic assistance
Enrique Chipont Benabent1, Pedro García Hermosa, María T Arrazola
1Instituto Oftalmologico de Alicante, Spain.

Insights
Electromyographic (EMG) guidance is not necessary for successful botulinum toxin injections in infantile esotropia. Results and complications are similar without EMG, potentially reducing anesthetic risks.
Area of Science:
- Ophthalmology
- Pediatric Strabismus Surgery
- Neurotoxin Applications
Background:
- Infantile esotropia is a common form of strabismus in children.
- Botulinum toxin injections are used to treat medial rectus muscle overaction.
- The necessity of electromyographic (EMG) guidance during these injections is debated.
Purpose of the Study:
- To evaluate if electromyographic (EMG) control is required for effective botulinum toxin injections in the medial rectus muscles of pediatric patients under sedation.
- To assess the impact of EMG guidance on ocular alignment and postoperative complications.
Main Methods:
- A consecutive series of 40 neurologically normal children (6-48 months) diagnosed with essential infantile esotropia were included.
- Botulinum toxin (7 IU) was injected into both medial rectus muscles under sevoflurane sedation without EMG guidance.
- Postoperative assessments for tropia, paralysis, and complications were conducted at 3 days, 3 weeks, 3 months, and 6 months.
Main Results:
- The mean postoperative esotropia at 6 months was 8.47 prism diopters.
- 53% of patients achieved an esotropia between 0 and 10 prism diopters.
- Common complications included ptosis (23%) and vertical deviation (21%); conjunctival hemorrhage occurred in 7%.
Conclusions:
- Botulinum toxin injections without electromyographic (EMG) guidance yield comparable results to those with EMG in treating congenital esotropia.
- Avoiding EMG guidance may reduce anesthetic risks in pediatric patients.
- The study advocates against the routine use of EMG guidance for botulinum toxin injections in congenital esotropia.
Purpose:
To ascertain whether electromyographic control of the muscles when injecting botulinum toxin in the medial rectus muscles of children under sedation is necessary to obtain good results in terms of ocular alignment and postoperative complications.
Methods:
Forty neurologically normal children 6 to 48 months of age were entered consecutively into the study once the initial diagnosis of essential infantile esotropia had been made. The children were sedated with sevoflurane and both medial rectus muscles were injected with 7 IU of botulinum toxin using an insulin syringe with a 27-gauge needle. Postoperative controls were performed at 3 days, 3 weeks, 3 months, and 6 months after the injection. The effectiveness of the injection was noted in terms of tropia, paralysis, and associated complications.
Results:
The mean tropia at 6 months postoperatively was 8.47 prism diopters of esotropia, ranging from 25 prism diopters of esotropia to 10 prism diopters of exotropia. Fifty-three percent of the patients had an esotropia between 0 and 10 prism diopters. The most common complications were ptosis and vertical deviation, affecting 23% and 21% of the patients, respectively, followed by conjunctival hemorrhage, which was recorded in 7% of the patients. There were no retrobulbar hemorrhages, ocular perforations, or anesthetic complications.
Conclusions:
If anesthetic risks are higher and the results are similar when using electromyographic control, we advocate not using it in congenital esotropia when injecting botulinum toxin in children.

Related Concept Videos
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:17
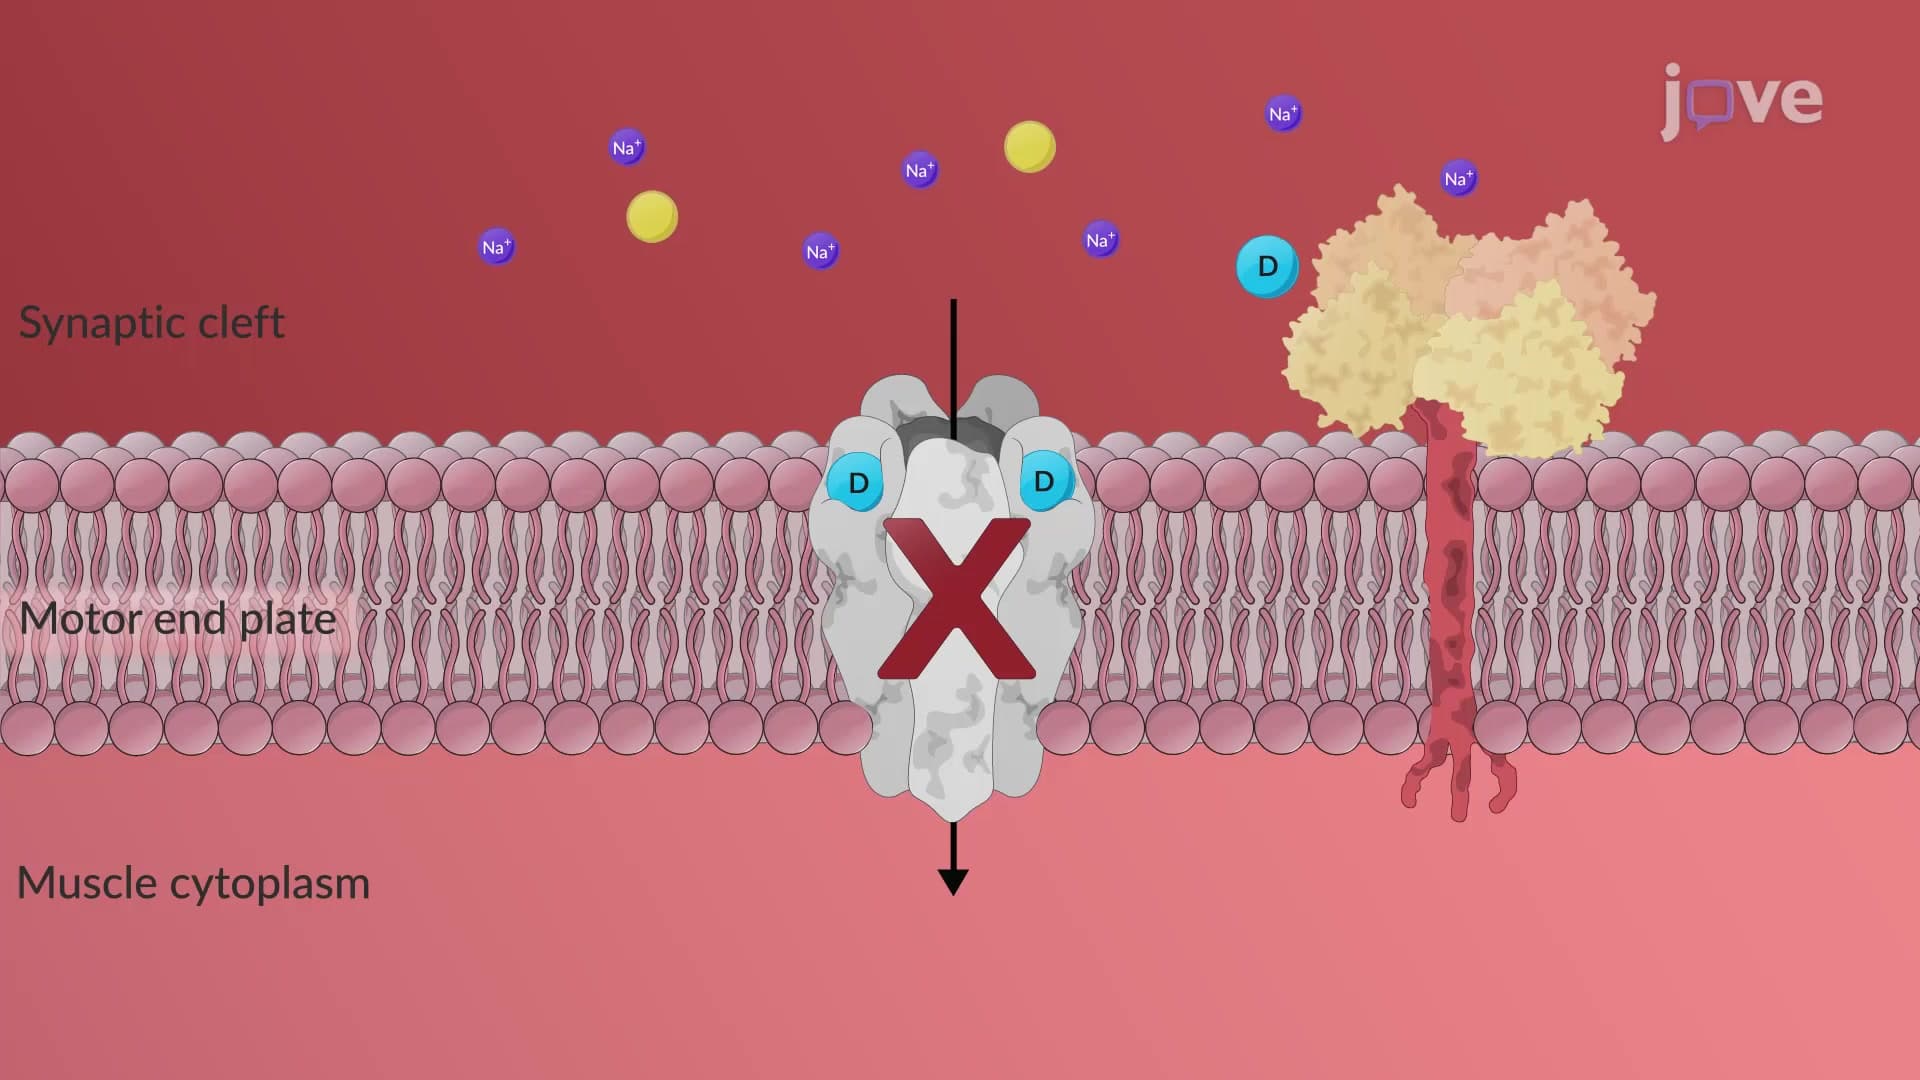
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses