Related Experiment Video
Updated: Sep 29, 2026
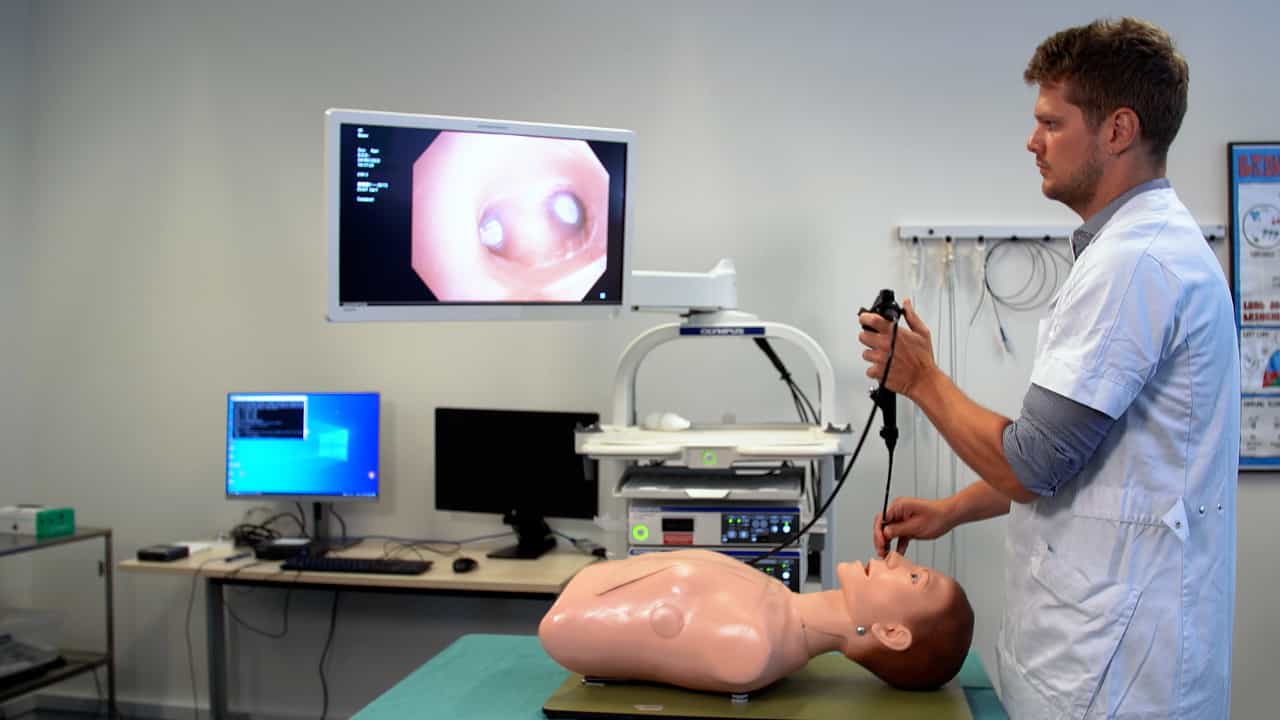
Systematic Bronchoscopy: the Four Landmarks Approach
Published on: June 23, 2023
Airway obstruction in children with congenital heart disease: assessment by flexible bronchoscopy
S L Lee1, Y F Cheung, M P Leung
1Department of Paediatrics, Queen Mary Hospital, Hong Kong, People's Republic of China. slleem@hkucc.hku.hk

Insights
Children with congenital heart disease often experience airway obstruction. Flexible bronchoscopy is a safe and effective diagnostic tool for identifying these airway problems in pediatric patients.
Area of Science:
- Pediatric Pulmonology
- Pediatric Cardiology
- Diagnostic Bronchoscopy
Background:
- Congenital cardiac anomalies are associated with a spectrum of airway disorders in children.
- Airway obstruction can occur pre- and post-operatively in these patients.
Purpose of the Study:
- To assess the range of airway disorders in children with congenital heart disease.
- To review the utility of flexible bronchoscopy in diagnosing airway issues in this population.
Main Methods:
- Retrospective review of clinical records, flexible bronchoscopic findings, and cardiac imaging in pediatric patients (1992-1999).
- Flexible bronchoscopy performed under sedation and topical anesthesia.
- Analysis of 52 pediatric patients presenting with signs of airway obstruction.
Main Results:
- A definitive diagnosis was made in 92% of patients.
- Common airway abnormalities included extrinsic compression (67%) of the lower airways, often by dilated pulmonary arteries, and intrinsic lesions like subglottic stenosis.
- Upper airway issues such as laryngomalacia were also identified.
Conclusions:
- Children with congenital heart disease are at significant risk for airway obstruction.
- Flexible bronchoscopy is a safe and effective first-line investigation for diagnosing airway disorders in this patient group.
Abstract:
We assessed the spectrum of airway disorders in children with congenital cardiac anomalies, and reviewed our experience in using flexible bronchoscopy for assessment of airway problems in this patient group. The clinical records, flexible bronchoscopic findings, and cardiac imaging results of pediatric cardiac patients who presented with either clinical or radiological signs of airway obstruction between 1992-1999 were reviewed. Flexible bronchoscopic assessment was performed with the patients under sedation and topical anesthesia, using one of two bronchoscopes, i.e., an Olympus BFN20 or Olympus BF3C20. Of a total of 52 patients, 33 had acyanotic cardiovascular lesions, the commonest being left-to-right shunts (61%), while 19 had cyanotic heart lesions, with right ventricular outflow obstruction being the commonest (63%). Twenty-seven patients had undergone either surgical or transcatheter interventions. The median age at bronchoscopic assessment was 6 months (range, 4 days to 6 years). None of the patients developed significant procedural complications. A definitive diagnosis was made in 48 (92%) patients, 8 of whom had abnormalities involving only the upper airways, 35 only the lower airways, and 5 both. Abnormalities of the upper airway included laryngomalacia (n = 6), subglottic stenosis (n = 3), pharyngeal collapse (n = 2), and 1 each of choanal stenosis and supraglottitis. Extrinsic compression was the commonest lower airway abnormality that was found in 27/40 patients (67%), with a predilection for the left main bronchus (18/27, 67%). The structures that caused extrinsic compression included dilated pulmonary arteries with or without left atrial dilation (n = 20), an anomalous aortic or pulmonary arterial course (n = 3), a dilated aorta (n = 1), and a shunt (n = 1), but were not obvious in 2 patients. Intrinsic lower airway abnormalities included bronchomalacia (n = 4), tracheal stenosis (n = 4), and one each of variant bronchial bifurcation and a pouch arising from the tracheal wall. Intraluminal mucus plugging of the lower airways occurred in the remaining 3 patients. Children with congenital heart disease are at risk of airway obstruction both before and after surgery. Flexible bronchoscopy, being safe and effective in diagnosing airway disorders in this patient group, should be considered as the first line of investigation.


Related Concept Videos
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...