Severe hypokalemia as a cause of acute transient paraplegia following electrical shock

R A Dasgupta1, J T Schulz, R C Lee

  • 1Sumner Redstone Burn Center, Surgical Services, Massachusetts General Hospital, Harvard Medical School, Bigelow 1302, Boston 02114, USA.

Related Concept Videos

Skeletal Muscle Relaxants: Adverse Effects01:21

Skeletal Muscle Relaxants: Adverse Effects

Skeletal muscle relaxants are widely used for muscle paralysis and relieving pain following any muscle injury or stiffness. However, depending on the drug type, they can have adverse effects that range from mild to severe. Usually, nondepolarizing neuromuscular blockers have minimal side effects. For example, drugs like d-tubocurarine, cisatracurium, and rocuronium cause hypotension, whereas drugs like baclofen, when stopped abruptly, can lead to the recurrence of spastic conditions.
Unlike...
Cardiac Action Potential01:30

Cardiac Action Potential

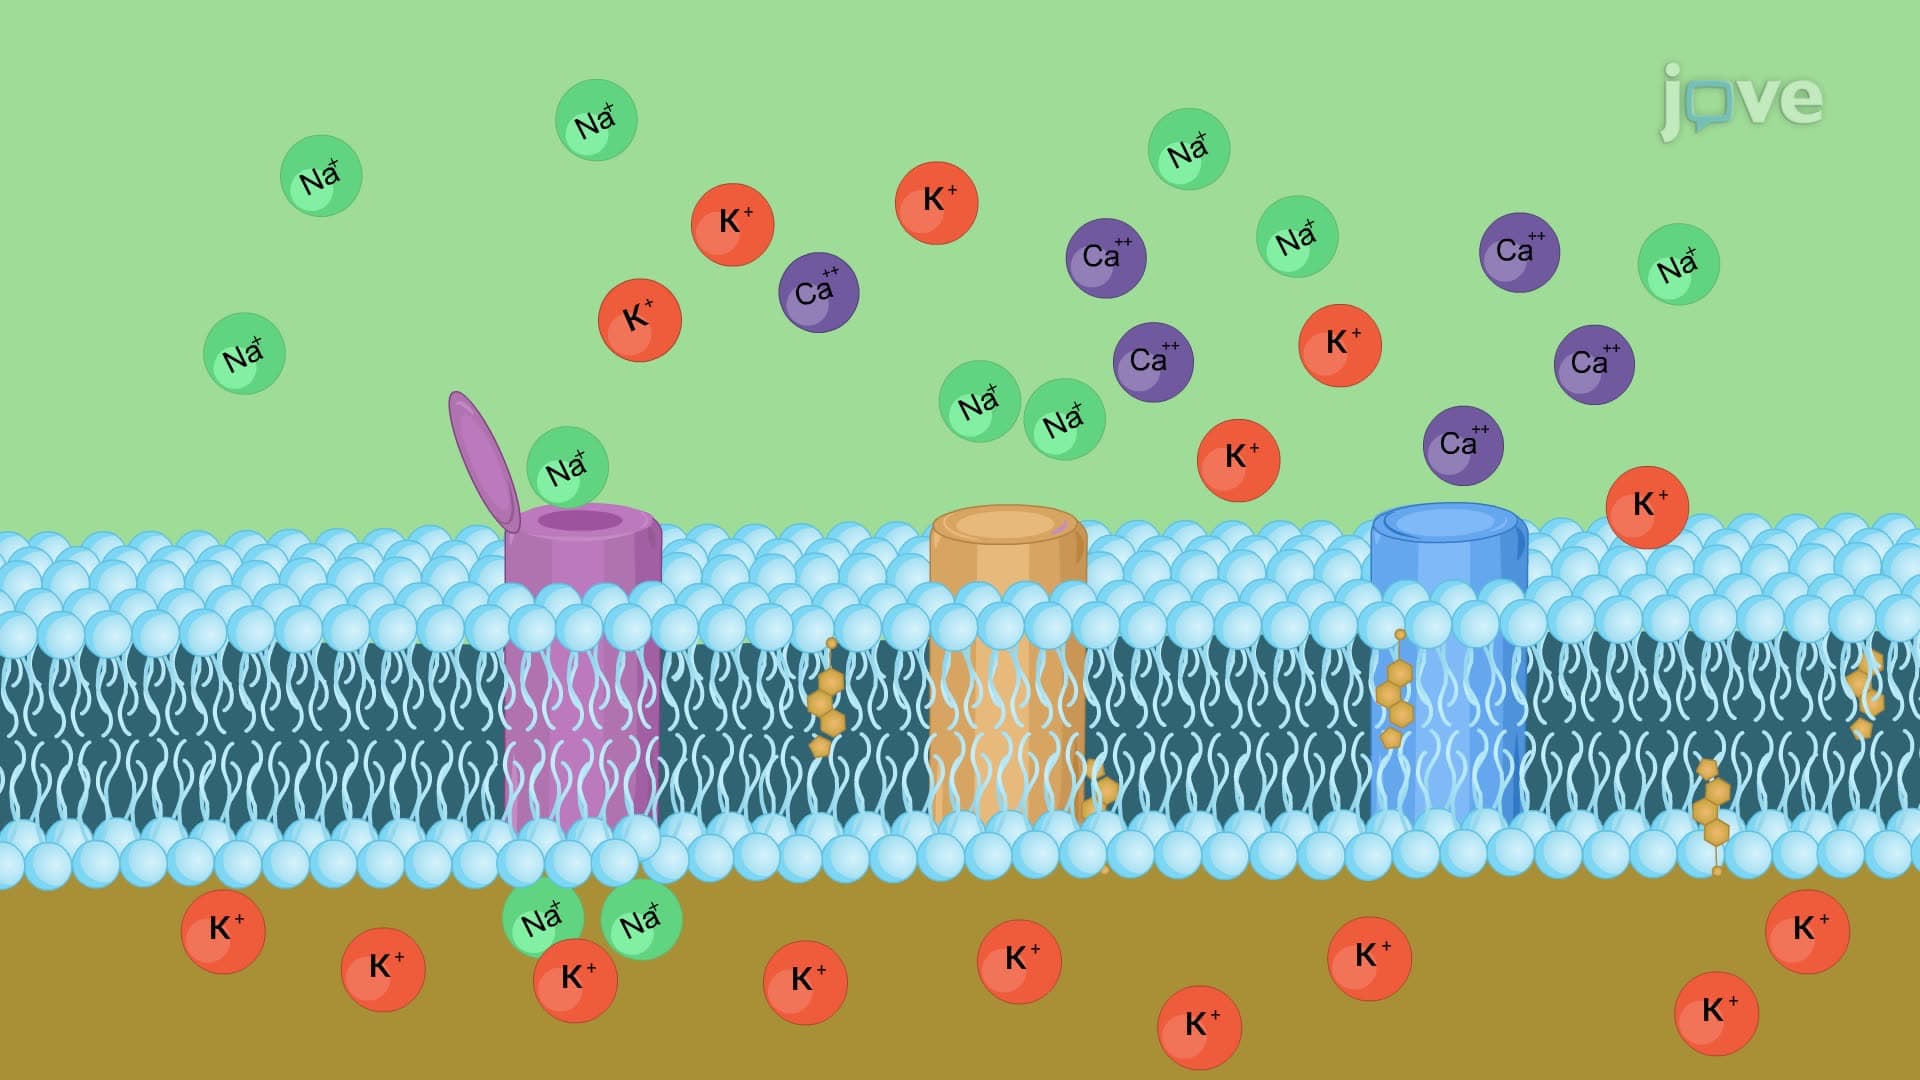
Cardiac action potentials are essential for proper heart function, enabling the rhythmic contractions needed for adequate blood circulation. Nodal cells and Purkinje fibers, specialized for electrical conduction, generate these action potentials.
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
Electroconvulsive Therapy01:30

Electroconvulsive Therapy

Electroconvulsive therapy (ECT), or shock therapy, remains a critical biomedical intervention for severe, treatment-resistant depression. While its origins can be traced back to Hippocrates' observations that malaria-induced convulsions alleviated mental illness, modern ECT has evolved significantly from its earlier, more primitive applications. First introduced in 1938 by Ugo Cerletti and his colleagues, ECT involves inducing controlled seizures using electrical currents. In its early years,...
Tetanus01:29

Tetanus

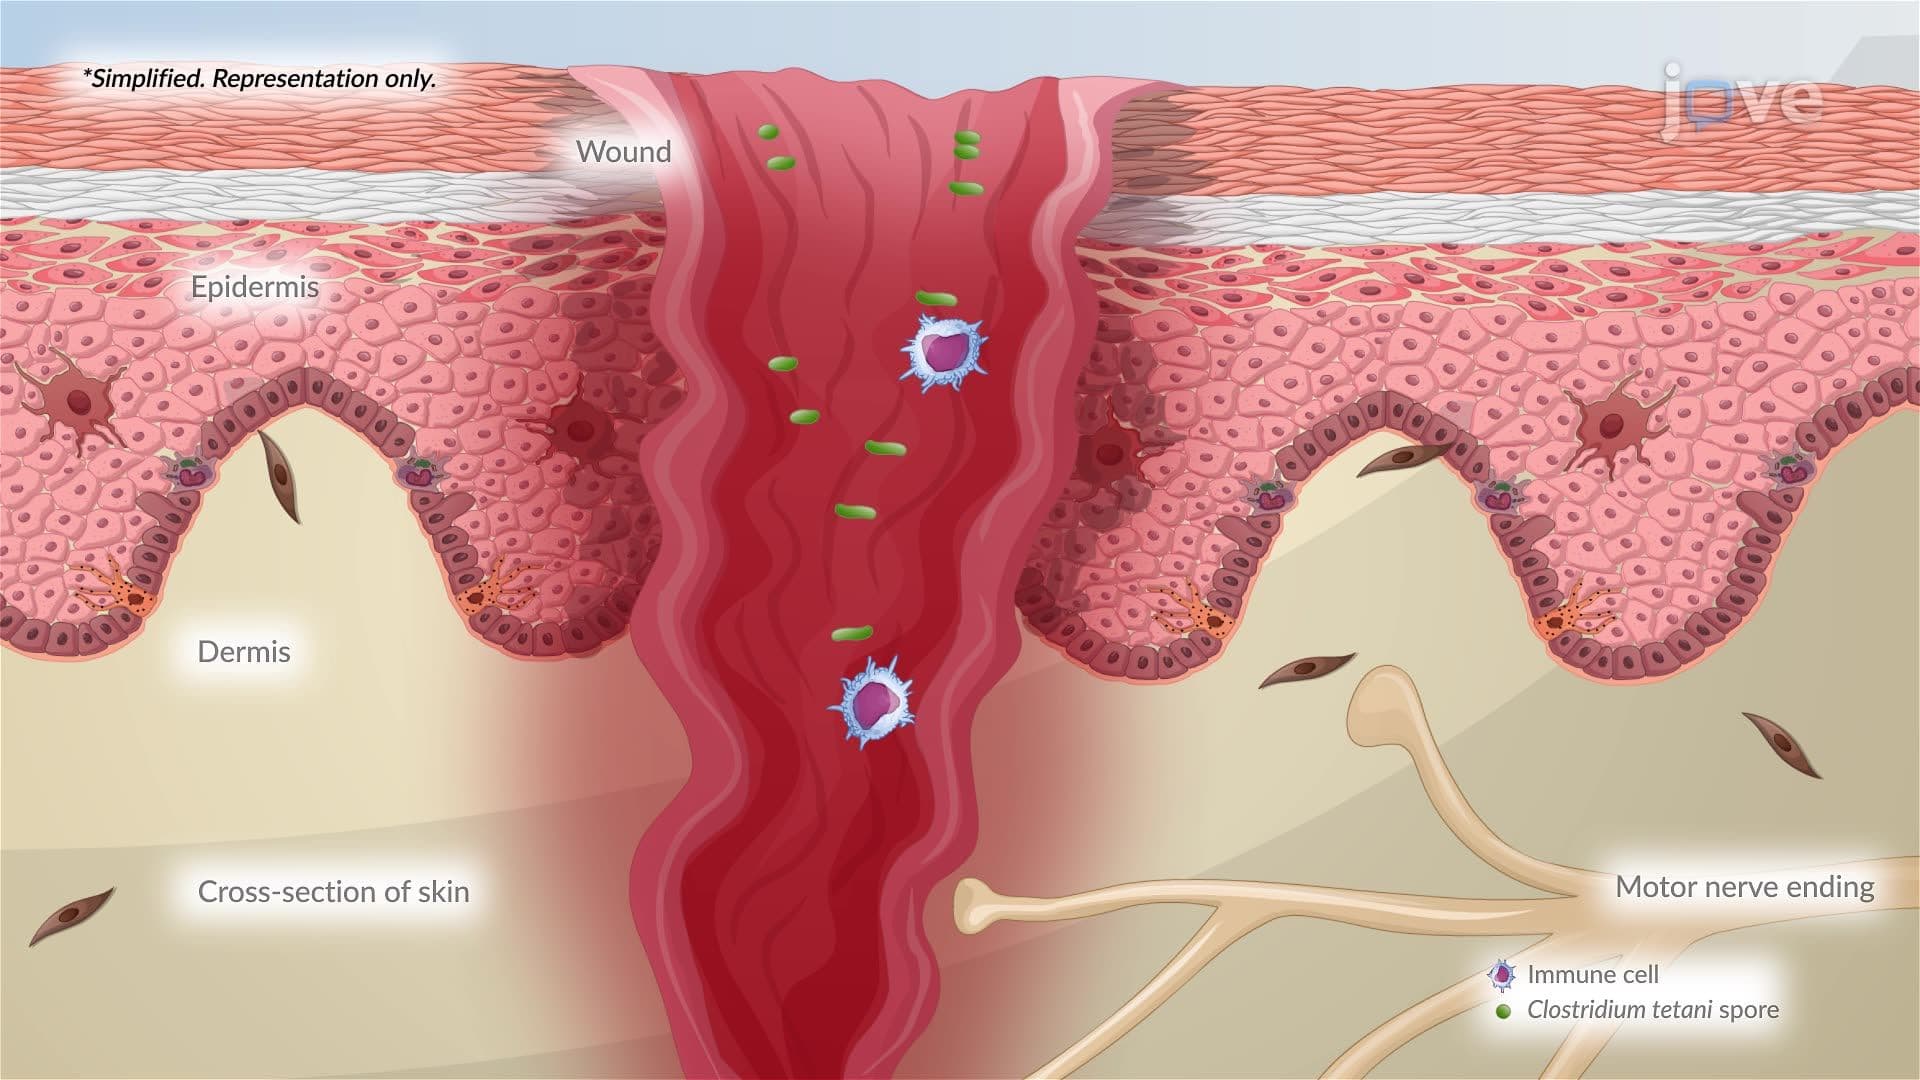
Tetanus is a life-threatening neurological disorder characterized by persistent muscle contractions and spastic paralysis. It is caused by Clostridium tetani, a motile, Gram-positive, rod-shaped, obligate anaerobe. These bacteria produce terminal endospores, giving them a distinctive “lollipop” or “tennis-racket” appearance. They thrive in anaerobic environments, such as those found in deep puncture wounds.Once introduced into the body, the spores germinate into vegetative cells. These cells...
Spinal Cord Injury ll: Pathophysiology01:14

Spinal Cord Injury ll: Pathophysiology
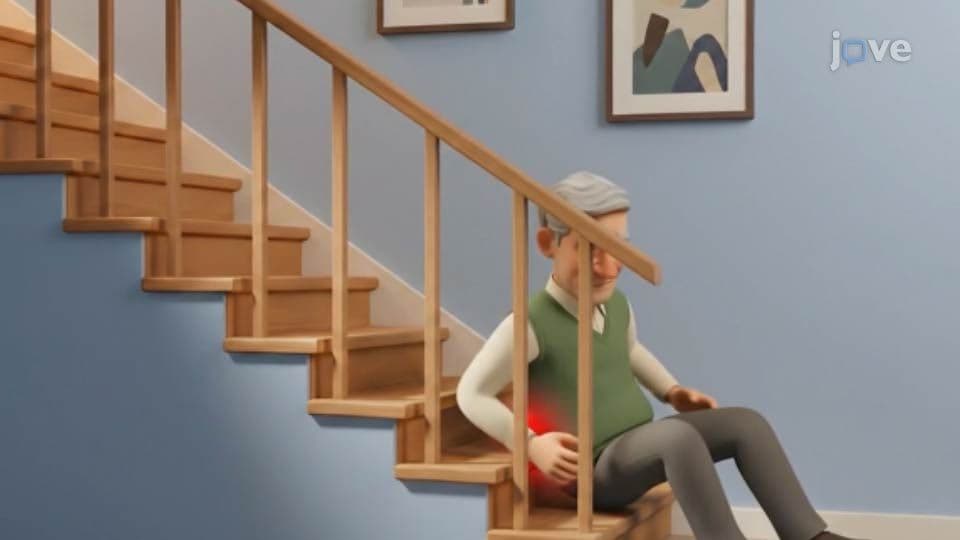
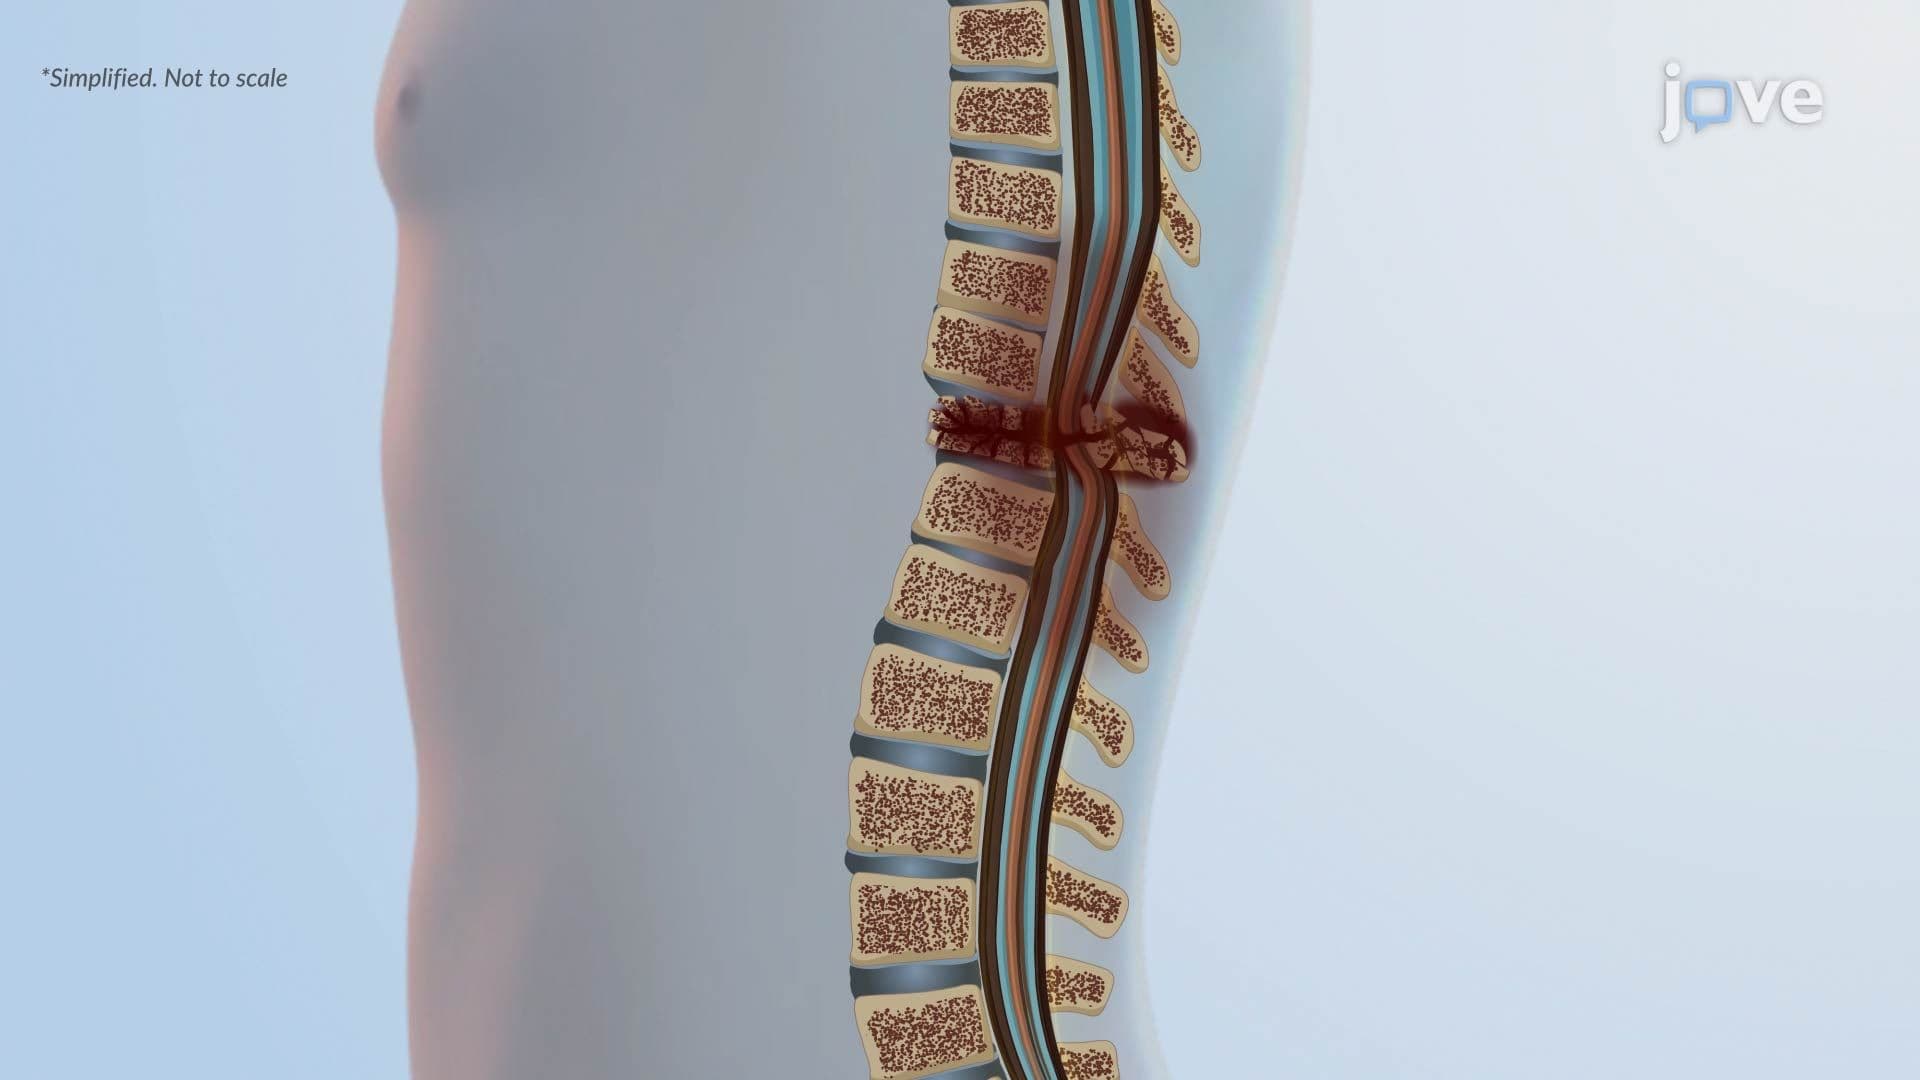
Spinal cord injury progresses through two interconnected phases: primary injury and secondary injury.Primary InjuryPrimary injury happens at the moment of trauma and involves immediate mechanical damage to the spinal cord.Compression happens when broken vertebrae, herniated discs, or accumulating blood (such as a hematoma) press directly against the spinal cord, distorting its normal shape and function. In cases of contusion, the cord is bruised by a blunt force (like penetrating injuries or...
Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology

Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...