Related Experiment Video
Updated: Sep 29, 2026
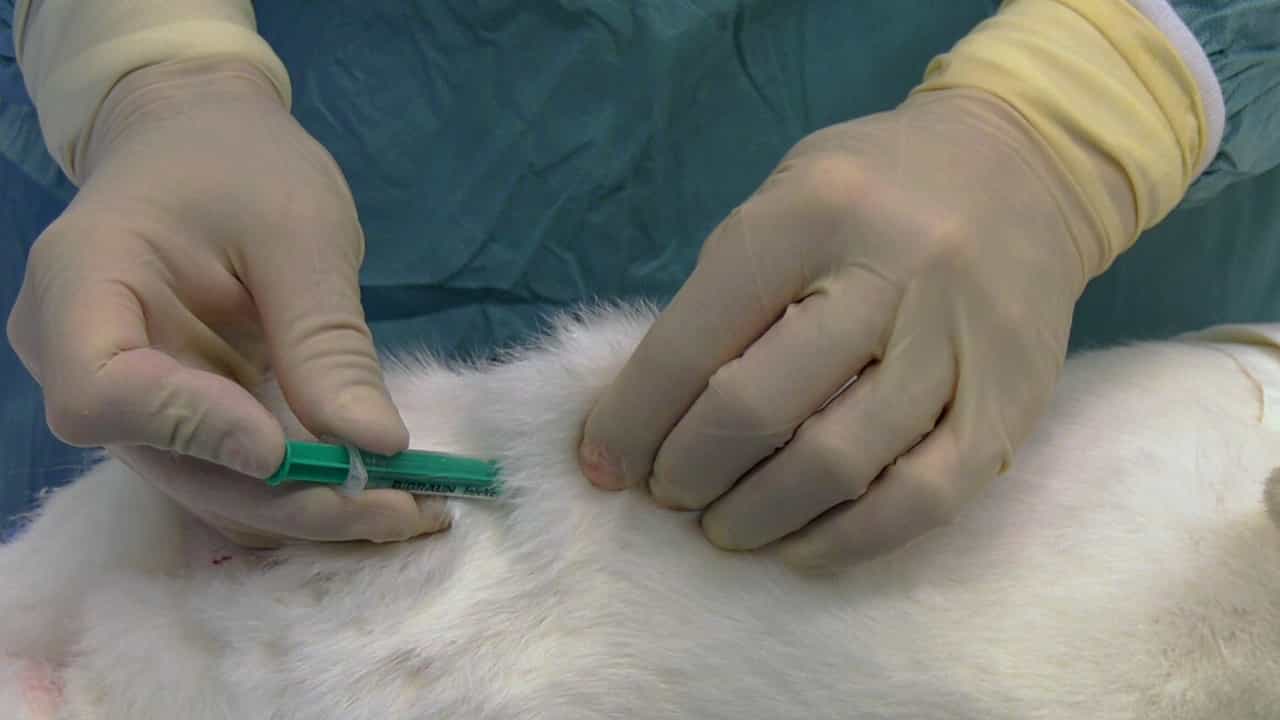

Microsurgical Creation of Giant Bifurcation Aneurysms in Rabbits for the Evaluation of Endovascular Devices
Published on: September 8, 2023
[Diagnostic and therapeutical considerations in the treatment of giant aneurysms]
J Regelsberger1, C Groden, M J A Puchner
1Neurochirurgische und Neuroradiologische Universitätsklinik Eppendorf, Hamburg. jregelsberger@aol.com

Abstract:
The treatment of giant aneurysms requires a thorough surgical and endovascular planning as this entity is accompanied by complex vascular and blood flow particularities. Even in experienced neurovascular centers the clinical outcome varies considerably. Within a series of 1386 aneurysm patients 72 (5%) giant (>25 mm) aneurysms were treated in our institution. Their age ranged between 26 and 81 years (medium age 52 years). 22 patients were suffering of a subarachnoid hemorrhage (SAH). Additionally there were 50 patients with nerve palsies or unspecific symptoms due to unruptured giant aneurysms (UGA). Treatment modalities included surgical clipping (n = 35), balloon occlusion of the ICA (n = 12), endovascular coiling (n = 7) or a combined regimen of balloon occlusion, surgical clipping and EC-IC bypass (n = 8). 10 patients could not be treated on due to their high age or minor clinical status (H&H IV and V). 6 of 15 (40%) SAH-patients were discharged without any complaints compared to 26% (12 of 47 patients) in the group of unruptured aneurysms. 1 SAH-patients (7%) versus 13 UGA (28%) patients suffered persisting nerve palsies or minor neurological disorders. 32% (n = 15) of the UGA-patients were suffering of major neurological deficits and required further professional help. 5 patients remained in a vegetative state, 3 of these had been admitted with an incidental finding of an UGA. 6 of 15 (40%) SAH-patients died, 5 of them admitted with H&H grade IV or V. However only 3 of 47 (6%) UGA patients died. 2 of these had a fatal SAH before treatment, 1 underwent EC-IC bypass surgery with insufficient hemispheric vascularization followed by gross infarction. The clinical status and age of the patient are significant factors influencing treatment associated morbidity and mortality. The individual vascular situation may lead to a complex therapeutical regimen thereby predisposes higher complication rates. We believe that surgical clipping is the first choice of treatment allowing temporarily clipping and reconstruction of the normal anatomy by shrinking or/and reconstructive clipping while reducing the mass effect. Whereas endovascular coiling alone is less favorable due to the packing of the coils a combined endovascular and surgical approach have to be considered in selected cases.
More Related Videos
 11:58
Minimally Invasive Thumb-sized Pterional Craniotomy for Surgical Clip Ligation of Unruptured Anterior Circulation Aneurysms
Published on: August 11, 2015
 11:07
Biodegradable Magnesium Stent Treatment of Saccular Aneurysms in a Rat Model - Introduction of the Surgical Technique
Published on: October 1, 2017
Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:25
Aortic Regurgitation III: Medical Management
 01:22
Aneurysm IV: Nursing Management
 01:30
Aneurysm I: Introduction
 01:15
Aortic Regurgitation I: Introduction