Related Experiment Video
Updated: Sep 29, 2026


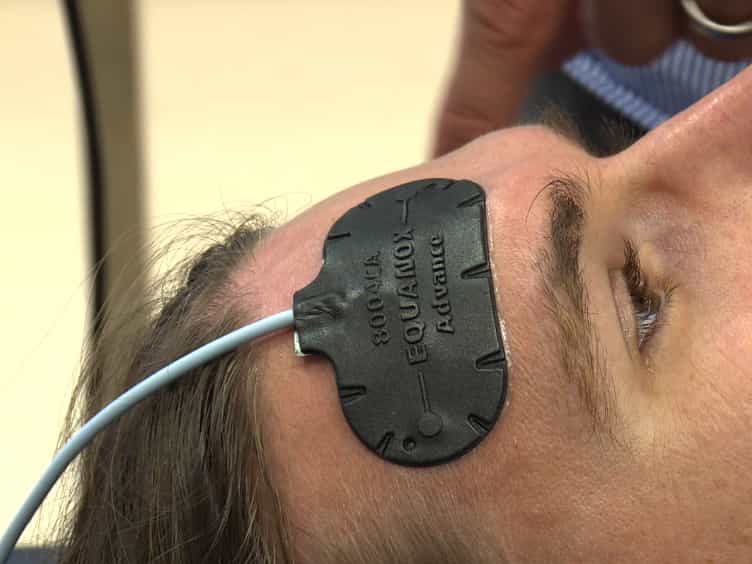
Drug-Induced Sleep Endoscopy (DISE) with Target Controlled Infusion (TCI) and Bispectral Analysis in Obstructive Sleep Apnea
Published on: December 6, 2016
Modulation of upper airway collapsibility during sleep: influence of respiratory phase and flow regimen
Hartmut Schneider1, An Boudewyns, Philip L Smith
1Johns Hopkins Sleep Disorders Center, Division of Pulmonary and Critical Care Medicine, Johns Hopkins University School of Medicine, Baltimore, Maryland 21224, USA.

Abstract:
We hypothesized that upper airway collapsibility is modulated dynamically throughout the respiratory cycle in sleeping humans by alterations in respiratory phase and/or airflow regimen. To test this hypothesis, critical pressures were derived from upper airway pressure-flow relationships in six tracheostomized patients with obstructive sleep apnea. Pressure-flow relationships were generated by varying the pressure at the trachea and nose during tracheostomy (inspiration and expiration) (comparison A) and nasal (inspiration only) breathing (comparison B), respectively. When a constant airflow regimen was maintained throughout the respiratory cycle (tracheostomy breathing), a small yet significant decrease in critical pressure was found at the inspiratory vs. end- and peak-expiratory time point [7.1 +/- 1.6 (SE) to 6.6 +/- 1.9 to 6.1 +/- 1.9 cmH(2)O, respectively; P < 0.05], indicating that phasic factors exerted only a modest influence on upper airway collapsibility. In contrast, we found that the inspiratory critical pressure fell markedly during nasal vs. tracheostomy breathing [1.1 +/- 1.5 (SE) vs. 6.1 +/- 1.9 cmH(2)O; P < 0.01], indicating that upper airway collapsibility is markedly influenced by differences in airflow regimen. Tracheostomy breathing was also associated with a reduction in both phasic and tonic genioglossal muscle activity during sleep. Our findings indicate that both phasic factors and airflow regimen modulate upper airway collapsibility dynamically and suggest that neuromuscular responses to alterations in airflow regimen can markedly lower upper airway collapsibility during inspiration.
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:26
Respiratory Volumes and Capacities I
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: