Related Experiment Video
Updated: Sep 29, 2026

Semi-quantitative Assessment Using [18F]FDG Tracer in Patients with Severe Brain Injury
Published on: November 9, 2018
Tolerability of bolus versus continuous gastric feeding in brain-injured patients
Denise H Rhoney1, Dennis Parker, Christine M Formea
1drhoney@wayne.edu

Abstract:
Brain injured patients may exhibit altered gastric emptying; thus, some believe post-pyloric feeding to be tolerated better than gastric feeding. Reliable post-pylorus access can be difficult to obtain, so gastric feeding remains the preferred route for administering nutrition. Feeding intolerance may be associated with increased complications and costs. We sought to compare bolus (B) versus continuous (C) gastric feeding in brain injured patients. This retrospective cohort study was carried out at a neurological/neurosurgical intensive care unit at a Level 1 trauma and tertiary referral center. Our subjects were 152 consecutive patients over two years. Use of B or C feedings was based on clinicians' preferences. Abdominal examination and gastric residuals (> 75 mL over four hours) defined feeding intolerance (FI). Putative risks for FI were compared between the groups. Demographic characteristics were similar between groups B (n = 86) and C (n = 66). Feeding intolerance occurred more often in group B than in group C (60.5% vs. 37.9%, p = 0.009). Group C patients achieved 75% of nutritional goals faster than group B patients (median 3.3 vs. 4.6 days; p = 0.03). Prokinetic agent use was similar between the groups and did not reduce the time to achieve nutritional goals. There was a trend towards a reduction in the incidence of infections in group C (p = 0.05). Independent predictors of FI included: sucralfate (OR 2.3), propofol (OR 2.1), pentobarbital (OR 3.9) or paralytic (OR 3) use; older age (OR 5); days receiving mechanical ventilation (OR 1.2); and admission diagnosis of either intracerebral hemorrhage (OR 2.2) or ischemic stroke (OR 1.9). Continuous gastric feeding is better tolerated than B feedings in patients with acute brain injuries. Use of prokinetic agents did not affect time to achievement of nutritional goals. Use of common medications including sucralfate and propofol were associated with FI.
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:24
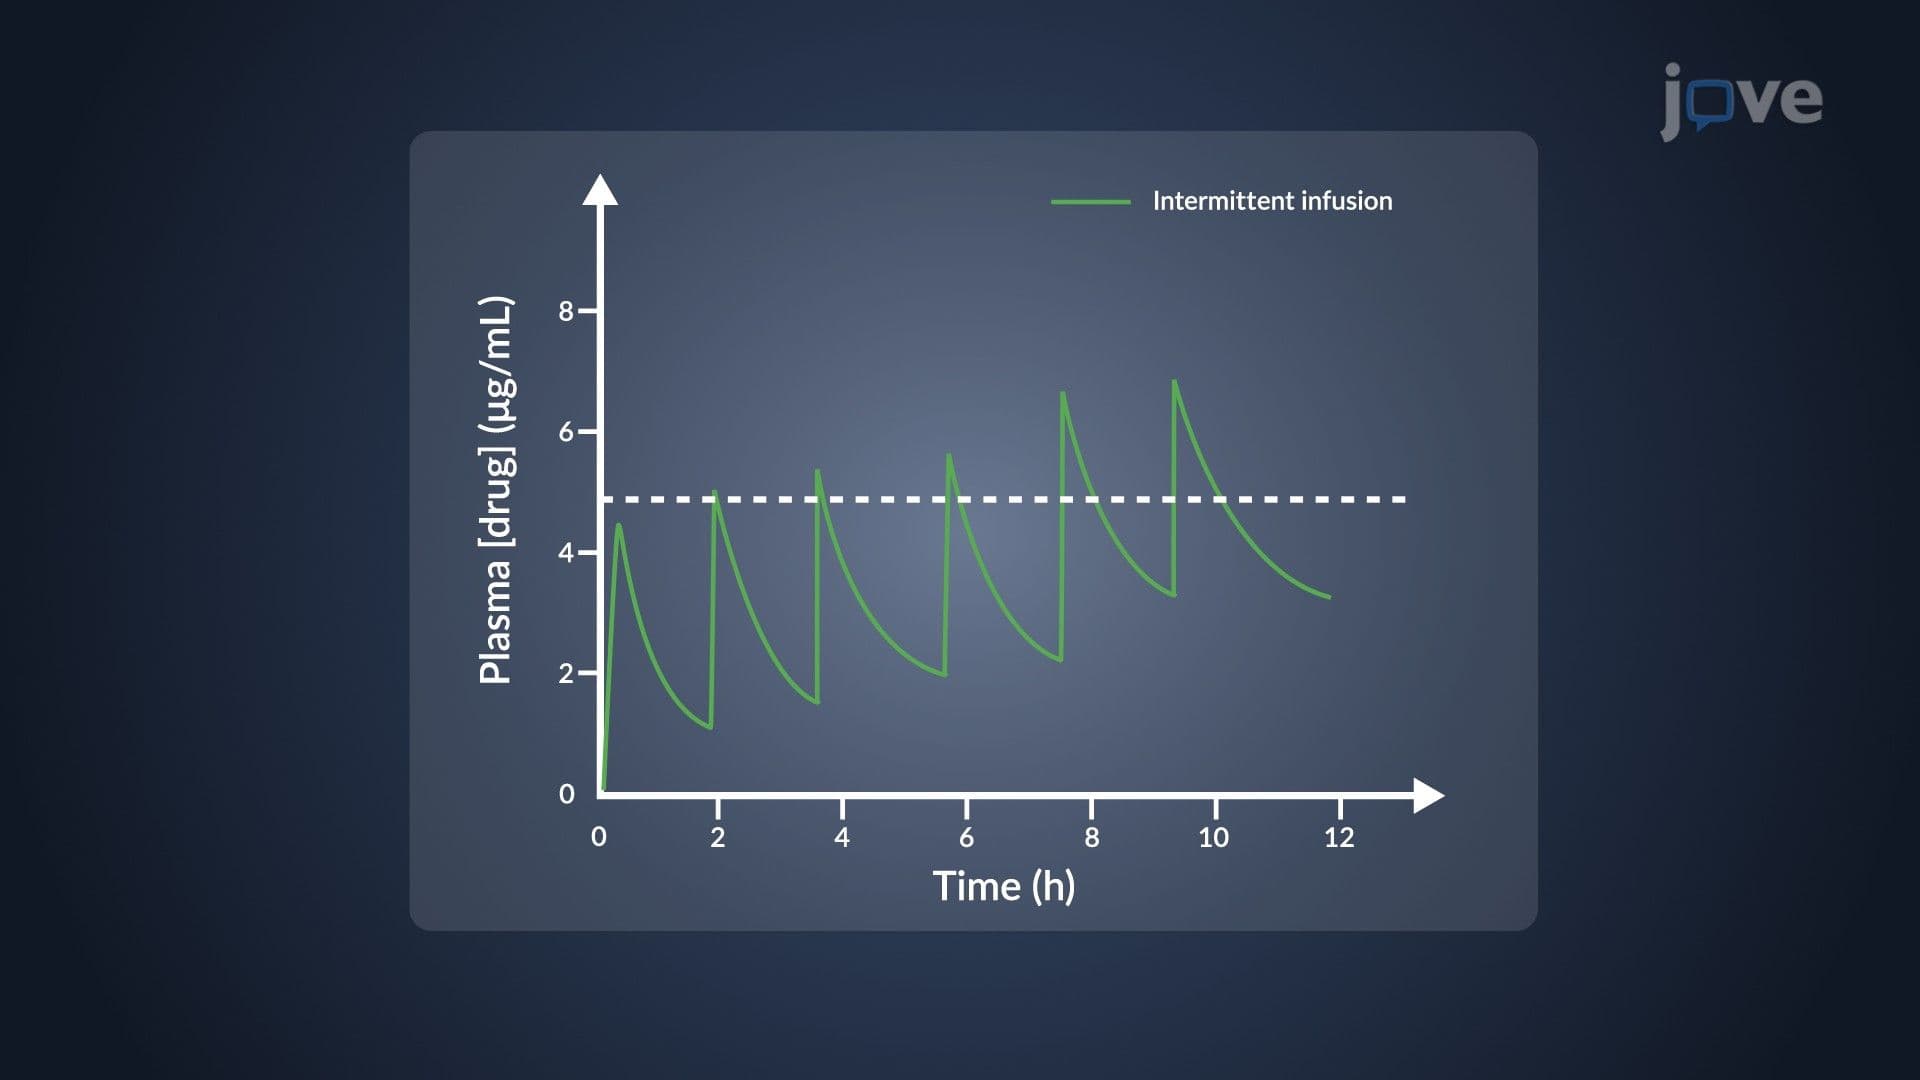
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 00:56
One-Compartment Open Model for IV Bolus Administration: Estimation of Clearance
In the one-compartment open model for intravenous (IV) bolus administration, clearance is estimated by dividing the elimination rate by the plasma drug concentration. This equation leverages the elimination rate constant and the apparent...