Related Experiment Video
Updated: Sep 28, 2026
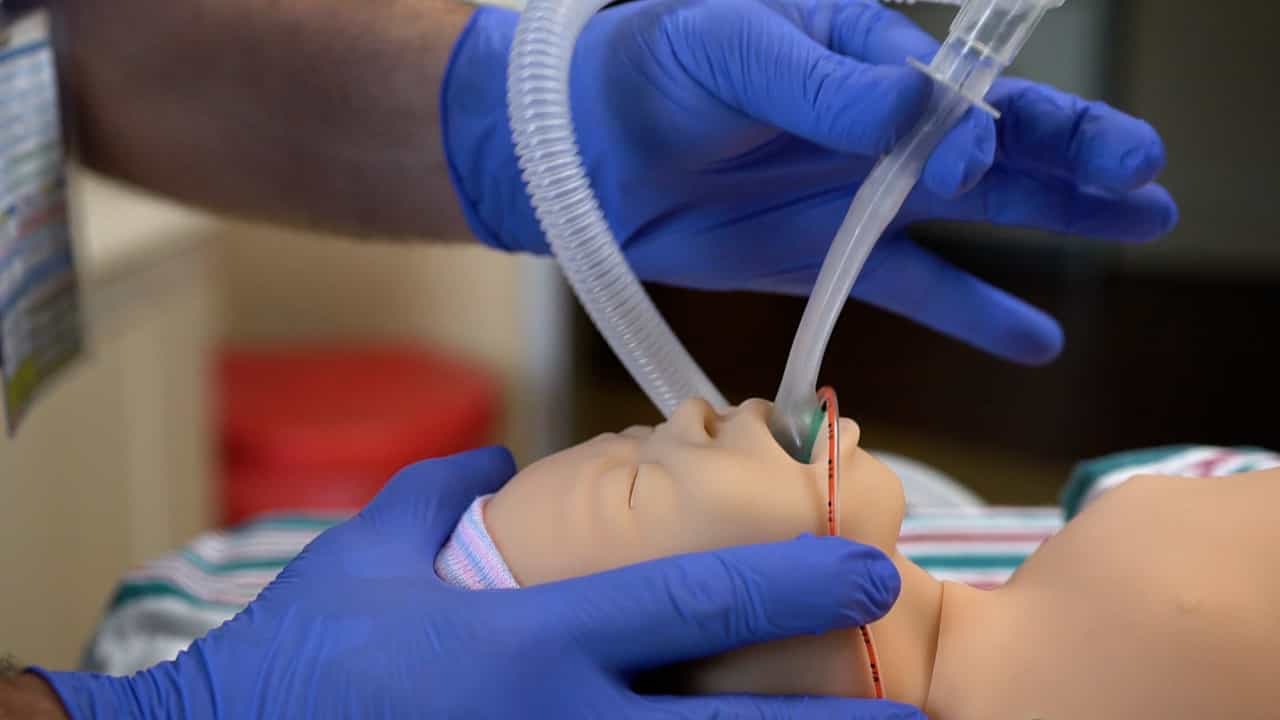

Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Airway complications in neonates who received mechanical ventilation
Thrathip Kolatat1, Kittirat Aunganon, Patcharin Yosthiem
1Department of Pediatrics, Faculty of Medicine Siriraj Hospital, Mahidol University, Bangkok, Thailand.

Objective:
To determine the incidence, type and severity of airway complications in high risk neonates who received conventional mechanical ventilation.
Method:
Forty-five infants who had received conventional mechanical ventilation in the Neonatal Intensive Care Unit, Department of Pediatrics, Faculty of Medicine Siriraj Hospital for at least 4 days were enrolled. Orotracheal intubation with blue line, non-cuffed, non-shouldered polyvinylchloride tube was used exclusively. The average number of intubations was 2 (range 1-7), and the average duration for intubation was 25 days. The details of the intubation, and the presence of respiratory distress after extubation were recorded. All of the infants had endoscopic examination of the airway within 5 days of extubation.
Results:
Following extubation, 14 (31.1%) infants developed signs of upper airway obstruction, of which inspiratory dyspnea was the most common manifestation. Only 4 infants developed inspiratory stridor, three of them had a birth weight greater than 2,500 g. Abnormal bronchoscopic findings were found in 42 infants, 68.8 per cent had multiple sites of injury. Supraglottic lesions were found in 55.7 per cent of cases. Laryngomalacia was an associated finding in 8 and gastroesophageal reflux (GER) in 1 occasion.
Conclusions:
From the result of this study, the authors found that airway complications related to endotracheal intubation are common among survivors from the Neonatal Intensive Care Unit. When the diagnosis of airway complications only depends on symptoms and signs of upper airway obstruction, the incidence and extent of injuries may be under-estimated. When attempted extubation fails or when VLBW infants develop increasing respiratory distress that is not clearly explained by an apparent disorder involving the pulmonary parenchyma, flexible bronchoscopic examination should be performed at the bedside with minimal risk.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:29
Mechanical Ventilation I: Indication and Settings
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)