Related Experiment Video
Updated: Sep 28, 2026
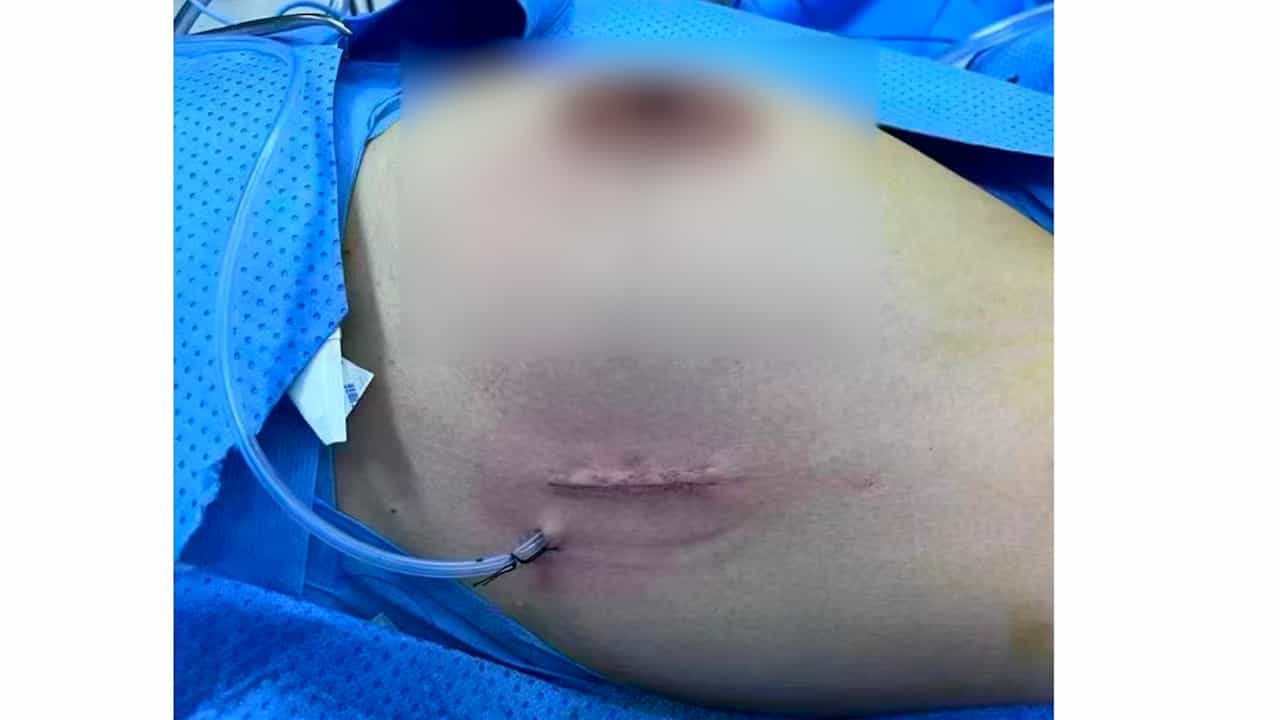
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Stage migration after biopsy of internal mammary chain lymph nodes in breast cancer patients
Viviana Galimberti1, Paolo Veronesi, Paolo Arnone
1Divisions of Senology, European Institute of Oncology, Milan, Italy. viviana.galimberti@ieo.it

Background:
Involvement of the internal mammary chain lymph nodes (IMNs) is associated with worsened prognosis in breast cancer. Use of lymphoscintigraphy to visualize sentinel nodes reveals that IMNs often receive lymph from the area containing the tumor.
Methods:
We biopsied IMNs in 182 patients because there was radiouptake to the IMNs or because the tumor was located in the medial portion of the breast. After tumor removal, pectoralis major fibers were divided to expose intercostal muscle. A portion of intercostal muscle adjacent to the sternum was removed. Lymph nodes and surrounding fatty tissue in the intercostal space were freed, removed, and analyzed histologically. The pleural cavity was breached in four cases (2.2%), with spontaneous resolution.
Results:
IMNs were found in 160 (88%) of 182 patients; 146 (94.4%) were negative and 14 (8.8%) were positive. The latter received internal mammary chain radiotherapy. The axilla was negative in 4 of 14 cases and positive in 10.
Conclusions:
IMNs can be quickly and easily removed via the breast incision with insignificant risk and no increase in postoperative hospitalization. The patients with a positive IMN migrated from N0 (4 cases) or N1 (10 cases) to N3, prompting modification of both local (radiotherapy to internal mammary chain) and systemic treatment; without IMN sampling, they would have been understaged.