Related Experiment Video
Updated: Sep 28, 2026
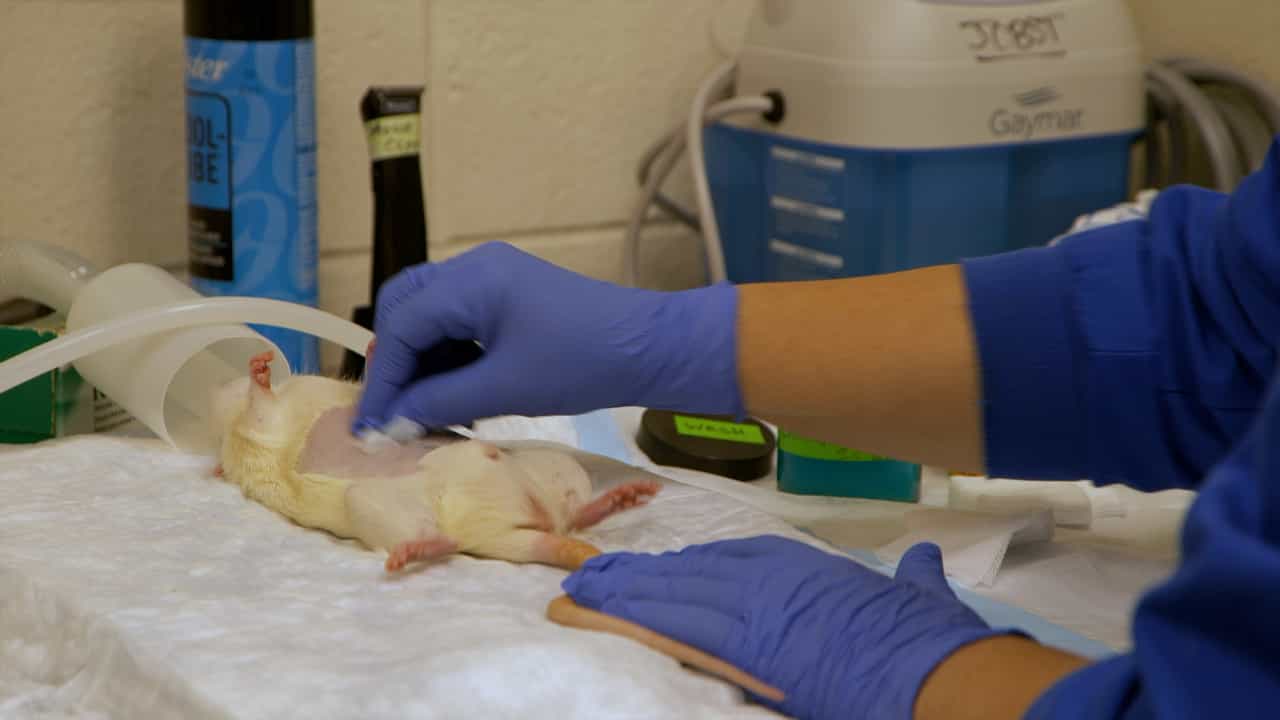

Rodent Inferior Vena Cava Venoplasty Balloon Model
Published on: May 24, 2024
Recanalization of totally occluded iliac and adjacent venous segments
Seshadri Raju1, Susan McAllister, Peter Neglen
1University of Mississippi Medical Center and River Oaks Hospital, Jackson, USA. rajumd@earthlink.net

Insights
Percutaneous recanalization of totally occluded iliac veins and inferior vena cava using stents is a safe and effective short-term treatment. The procedure significantly reduced pain and swelling, with good stent patency rates.
Area of Science:
- Vascular Surgery
- Interventional Radiology
- Cardiovascular Medicine
Background:
- Chronic venous occlusive disease affects the iliac veins and inferior vena cava, leading to significant morbidity.
- Percutaneous recanalization offers a minimally invasive approach to restore venous flow.
Purpose of the Study:
- To evaluate the safety and efficacy of percutaneous recanalization of totally occluded iliac veins and inferior vena cava.
- To report outcomes including patency rates and symptom resolution.
Main Methods:
- 38 limbs underwent iliac vein recanalization; 9 also required inferior vena cava recanalization.
- Large-caliber, self-expanding stents were deployed, often extending into the common femoral vein and inferior vena cava.
- Intravascular ultrasound was utilized; a median of 3 stents were placed per patient.
Main Results:
- No procedural morbidity or mortality was observed.
- Actuarial 24-month patency rates were 49% (primary), 62% (primary assisted), and 76% (secondary).
- Significant reductions in pain (median 4 to 0) and swelling were achieved; 66% of stasis ulcers resolved.
Conclusions:
- Percutaneous recanalization with stent placement is a successful short-term treatment for occluded iliac veins and inferior vena cava.
- The procedure demonstrates good patency and significant improvement in patient symptoms.
- Minimal morbidity associated with the intervention supports its clinical utility.
Purpose:
The purpose of this study was to report our experience with percutaneous recanalization of totally occluded iliac veins and inferior vena cava.
Material And Methods:
Recanalization of the iliac vein was performed in 38 limbs. In nine limbs, recanalization of the inferior vena cava was also necessary (two with filter). In 28 of 38 limbs, the stent was extended below the groin crease into the common femoral vein segment. Large-caliber (14 or 16 mm for iliac vein) flexible self-expanding stents were used. Stents were routinely extended for a short distance into the inferior vena cava to forestall development of iliocaval stenosis. Intravascular ultrasound scan was a valuable tool in the procedure. The median length of the recanalized segment was long (22 cm), and multiple stents (median, n = 3) were necessary in most patients. Forty-five percent of the patients had coagulation abnormalities.
Results:
No morbidity or mortality was seen. Actuarial primary, primary assisted, and secondary patency rates of the stents at 24 months were 49%, 62%, and 76%, respectively. Median pain level decreased significantly (level 4 to level 0; P <.0001) after stent placement, and more than two thirds of the patients became totally pain free after the procedure. Swelling also improved significantly, and a third of the patients became totally free of any swelling after stent placement. Sixty-six percent of cases with stasis ulcers/dermatitis (n = 14) were resolved (actuarial, 1 year), although uncorrected reflux persisted in many of these limbs.
Conclusion:
Percutaneous recanalization of the occluded iliac vein with stent placement appears to be successful in the short term, with good patency, significant symptom resolution, and minimal morbidity.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:26
Varicose Veins II: Diagnostic Studies and Interprofessional Care
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:26
Aneurysm III: Interprofessional Care