Related Experiment Video
Updated: Sep 28, 2026
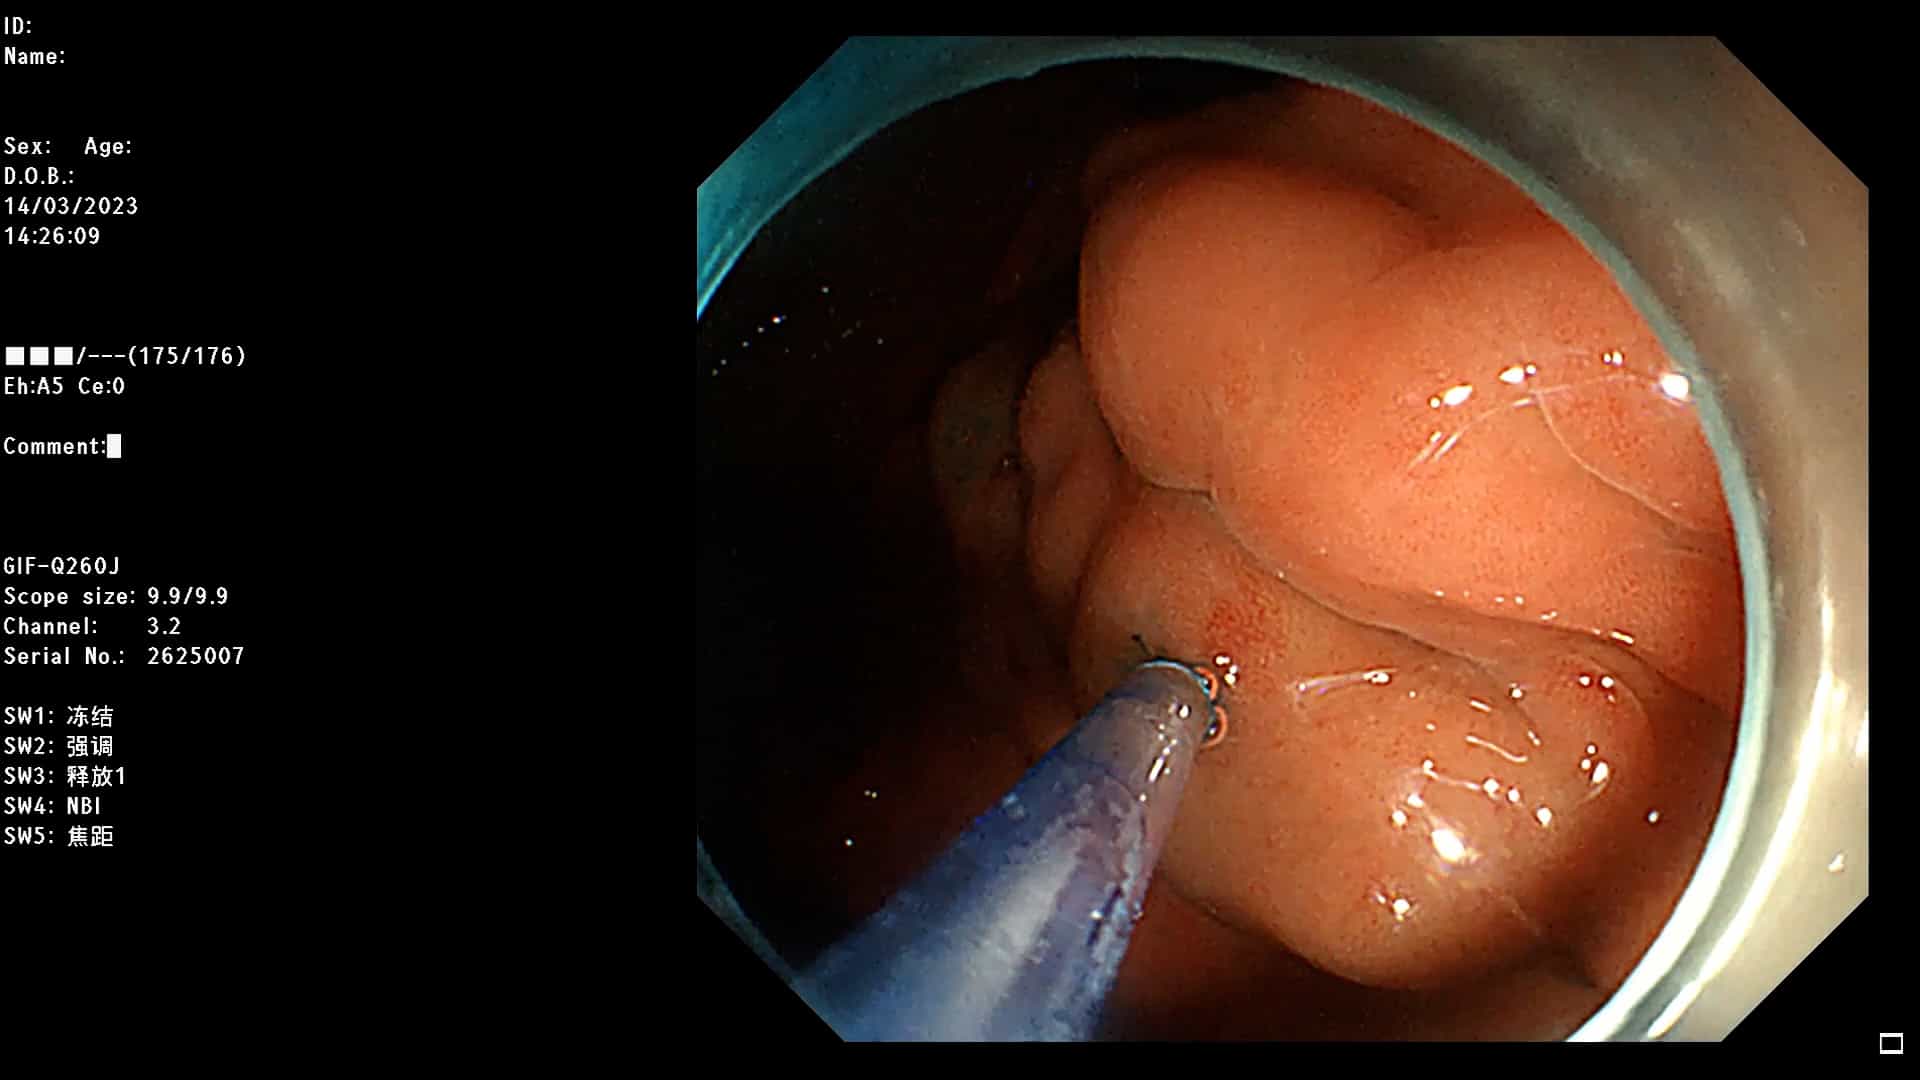
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
Local therapeutic injection in bleeding peptic ulcer: a comparison of adrenaline to adrenaline plus a sclerosing
A Garrido Serrano1, F J Guerrero Igea, C Perianes Hernández
1Department of Gastrointestinal Medicine, Hospital Comarcal de Riotinto, Huelva, Spain. agarridos@interec.org

Objective:
a) To analyse the probability of haemodynamic changes in patients with non-variceal upper gastrointestinal bleeding (NV-UGB), as well as the risk of bleeding in cases of peptic ulcer; and b) to compare an injection of epinephrine alone with epinephrine plus an sclerosing agent in ulcers with a high risk of persistent or recurrent bleeding.
Methods:
We studied 500 consecutive patients (295 males/205 females) who were admitted because of an NV-UGB episode. Haemodynamic evaluation and upper endoscopy were performed in all patients. They were randomised to receive an injection of epinephrine 1:10.000 or epinephrine plus 2% polidocanol in case of active bleeding, visible vessel or unstable clot.
Results:
263/500 (52.6%) were taking NSAIDs before the acute bleeding. 70/96 (72.9%) patients with red haematemesis showed haemodynamic changes vs 15/107 (14%) with dark haematemesis and melena, and 29/281 (10.3%) with melena alone, p < 0.01, OR = 20. Duodenal ulcer was the cause of NV-UGB in 206 cases (40.6%) and gastric ulcer in 134 (27.2%). However, an endoscopic therapy was performed in 85 patients, 58 with gastric ulcers (19 with active bleeding, 33 with visible vessel and 6 with unstable clot) vs 27 with duodenal ulcers (6 with active bleeding, 19 with visible vessel and 2 with unstable clot), p < 0.01, OR = 4.7. 15/85 patients developed recurrent bleeding after injection therapy: 3 with a non-bleeding visible vessel and 10 with active bleeding (10 were treated with epinephrine and 2 with epinephrine plus 2% polidocanol, p < 0.04, OR = 8). A multivariate logistic regression analysis showed that age, active bleeding and type of injected agent were the only independent variables associated with failure of treatment and recurrent bleeding.
Conclusions:
a) 52.6% of patients with NV-UGB were taking NSAIDs before acute bleeding; b) epinephrine injection followed by a sclerosing agent is more effective in case of active bleeding; however, there is no difference in case of visible vessel or unstable clot; and c) age, active bleeding and type of treatment were the only independent variables associated with recurrent bleeding.
Related Concept Videos
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:27
Peptic Ulcer