Related Experiment Video
Updated: Sep 28, 2026

10:26

Bladder Smooth Muscle Strip Contractility as a Method to Evaluate Lower Urinary Tract Pharmacology
Published on: August 18, 2014
Anaphylactoid reaction to cisatracurium may be explained by atracurium metabolites
Anesthesia and Analgesia
|December 31, 2002

Abstract
No abstract available in PubMed .
Related Concept Videos
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Nondepolarizing neuromuscular blockers prevent the membrane depolarization of muscle cells and inhibit muscle contraction. These are usually administered with anesthetics to achieve complete muscle relaxation. Upon administration, these drugs first block the small, rapidly contracting muscles of the face and hands, followed by the larger muscles of the trunk and the intercostal muscles. The diaphragm is the last muscle to be affected.
Although all competitive neuromuscular blockers are designed...
Although all competitive neuromuscular blockers are designed...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
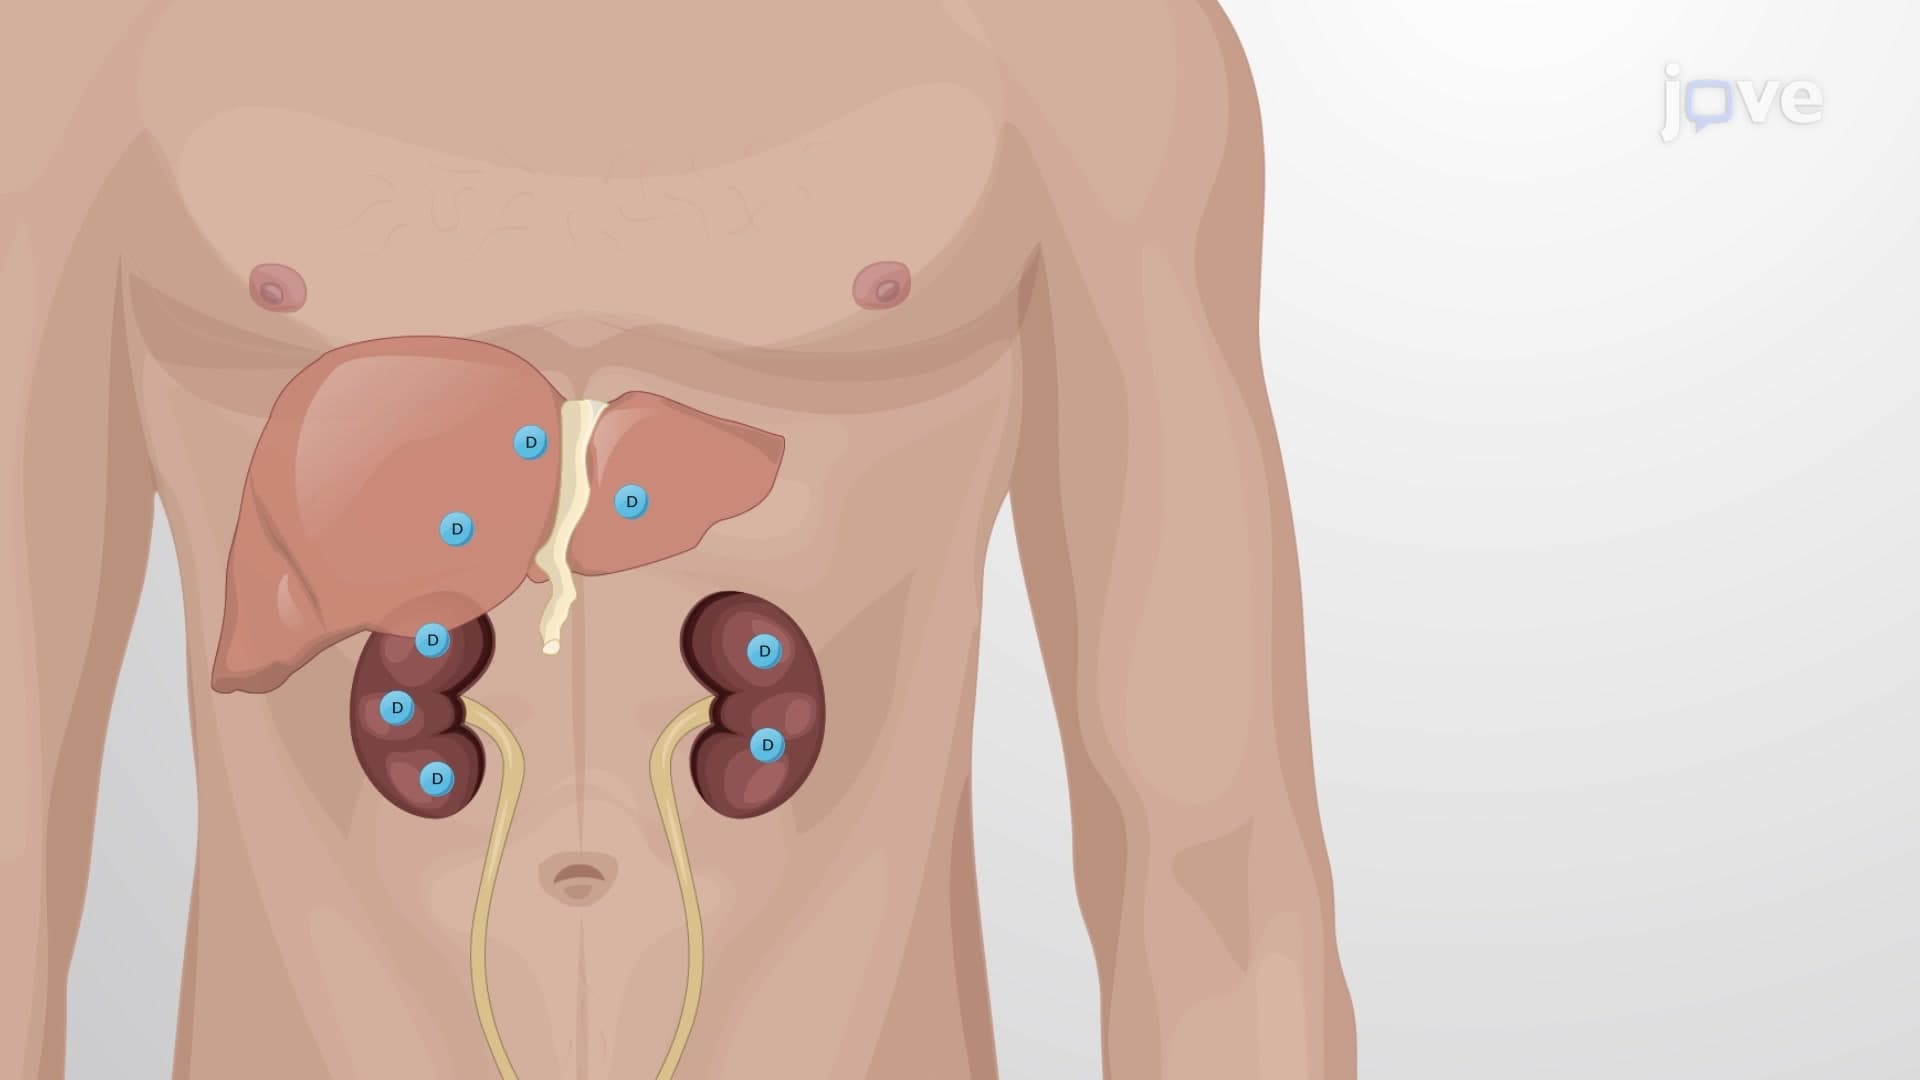
All neuromuscular blocking agents are injected intravenously because they are poorly absorbed from the GI tract. Rapid onset is achieved with intravenous administration, although absorption is also adequate from an intramuscular injection. Since these agents are highly ionized, they do not readily penetrate cell membranes or cross the blood-brain barrier.
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:24
Cholinergic Antagonists: Pharmacokinetics
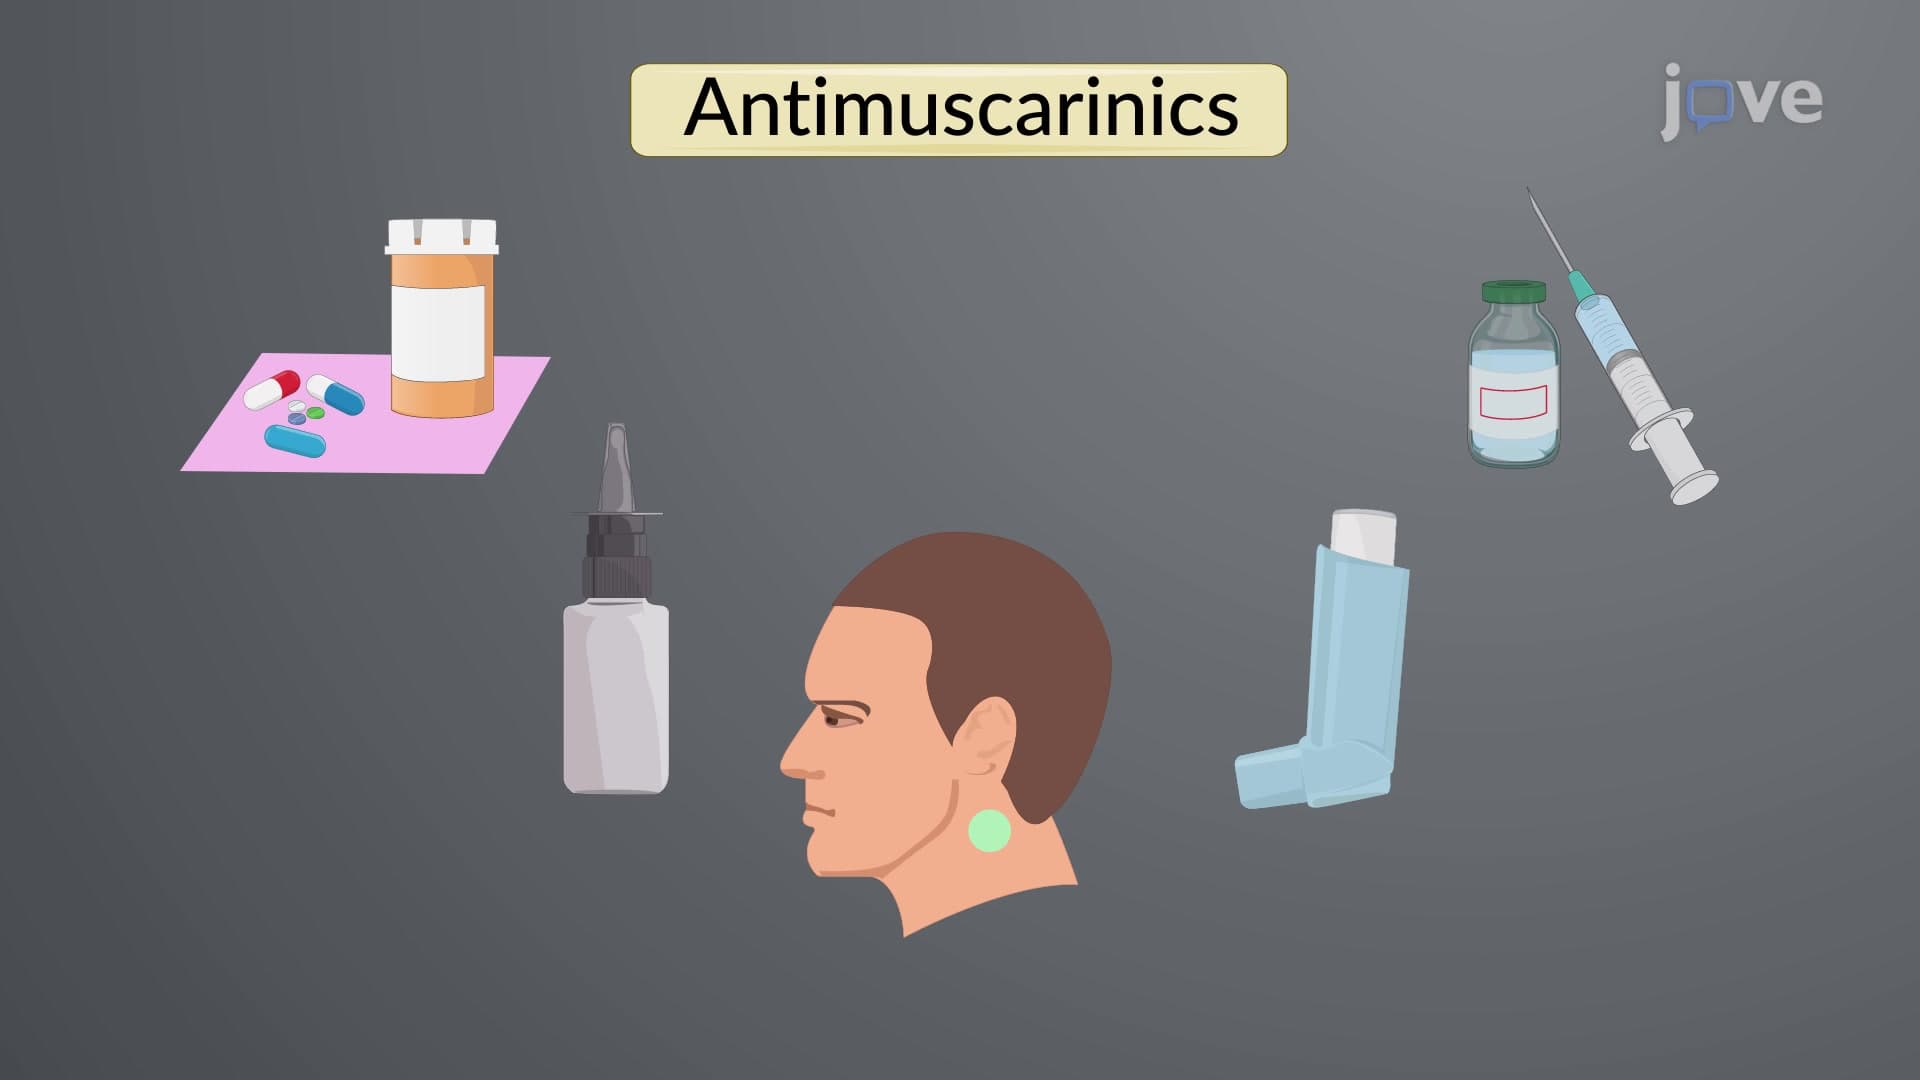
Cholinergic antagonists—such as antimuscarinics—are available in oral, topical, ocular, parenteral, and inhalational formulations. Most antimuscarinics are oral formulations, while scopolamine is available as a topical patch, and ipratropium and tiotropium are available as inhalation aerosols or powders. Atropine, tropicamide, and cyclopentolate are topically instilled in the eye. Most antimuscarinics are lipid-soluble and readily absorbed from the gastrointestinal tract and the conjunctiva.
 01:17
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
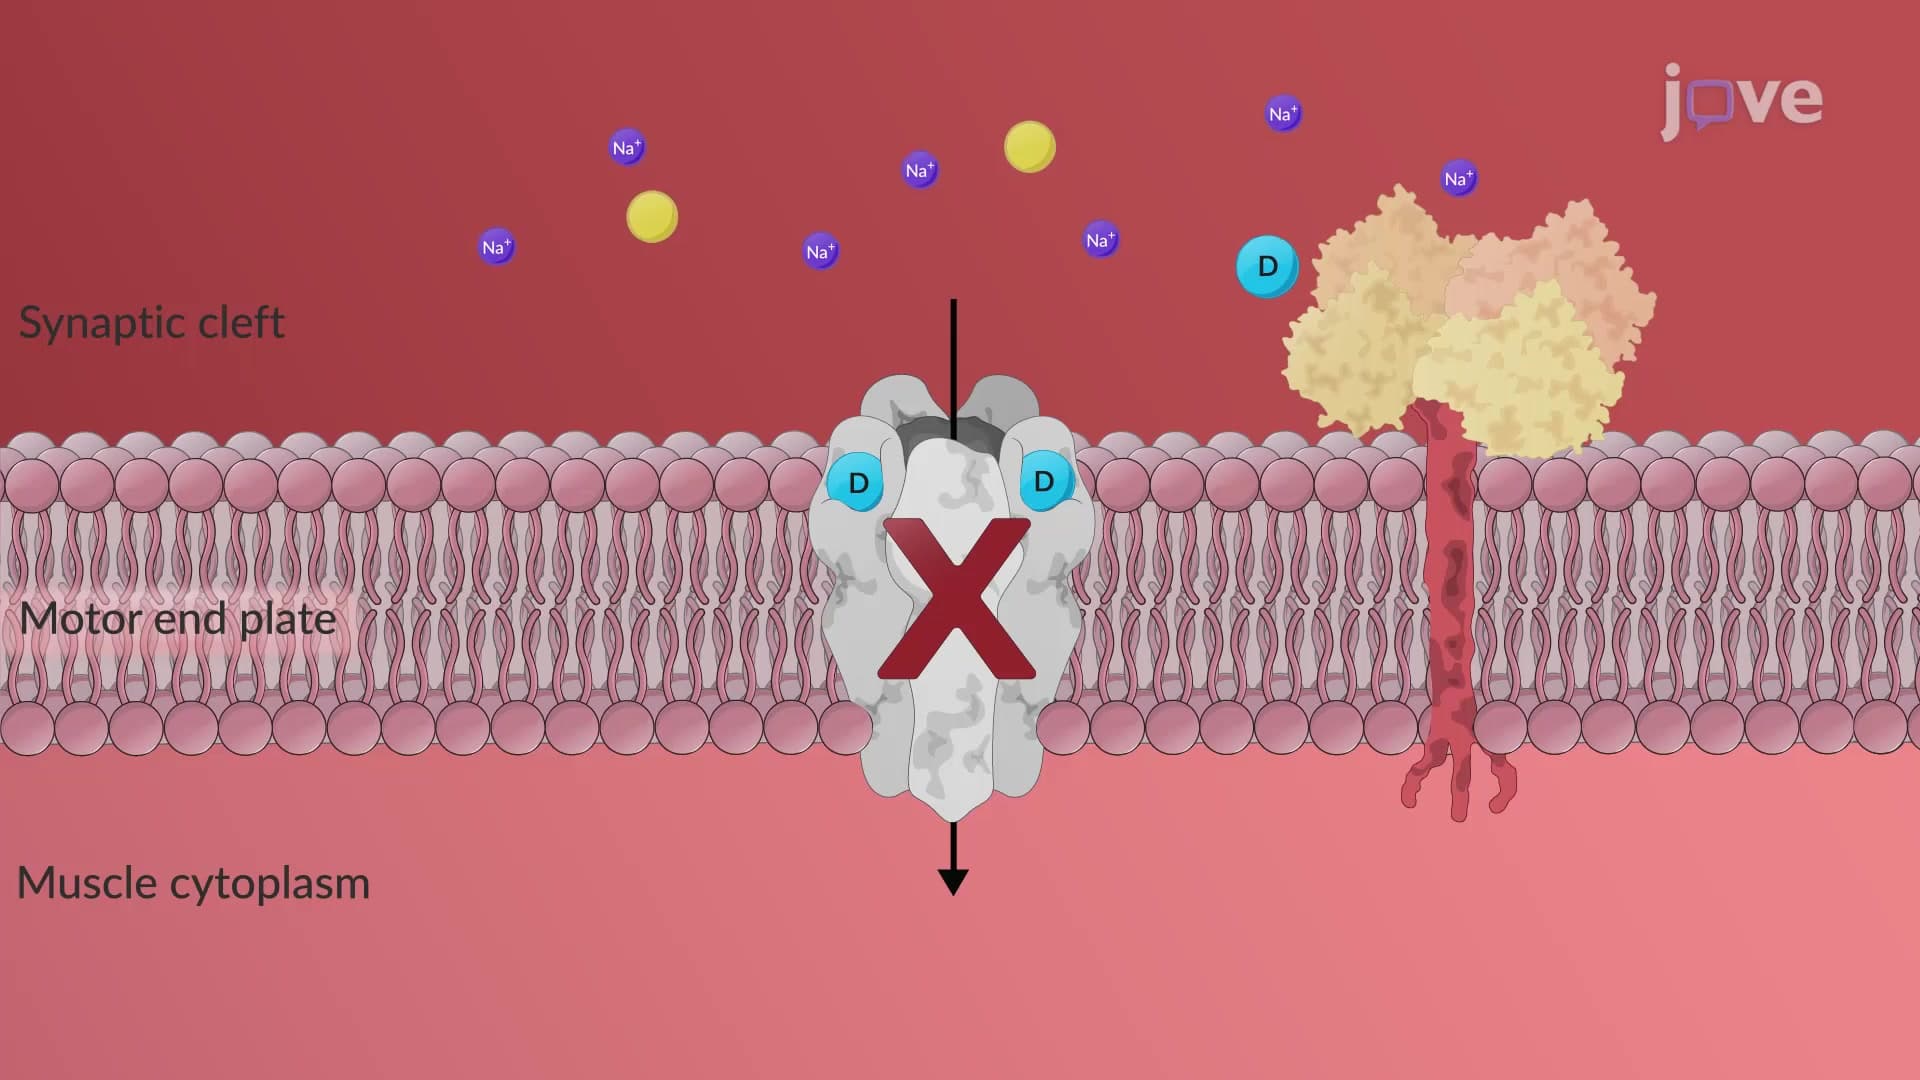
Nondepolarizing neuromuscular blockers induce paralysis by competitively blocking nicotinic acetylcholine receptors at the muscle end plate. Examples include pancuronium, mivacurium, vecuronium, and rocuronium. These quaternary ammonium derivatives are administered intravenously, are poorly absorbed, and are excreted via the kidneys.
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Anticholinesterases, also known as cholinesterase inhibitors, work by blocking the breakdown of acetylcholine, leading to its accumulation in the synaptic cleft. This accumulation indirectly enhances both muscarinic and nicotinic actions. These agents are classified as reversible or irreversible based on their mechanism of action.
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Skeletal muscle relaxants are widely used for muscle paralysis and relieving pain following any muscle injury or stiffness. However, depending on the drug type, they can have adverse effects that range from mild to severe. Usually, nondepolarizing neuromuscular blockers have minimal side effects. For example, drugs like d-tubocurarine, cisatracurium, and rocuronium cause hypotension, whereas drugs like baclofen, when stopped abruptly, can lead to the recurrence of spastic conditions.
Unlike...
Unlike...