Related Experiment Video
Updated: Sep 27, 2026


Establishment of Rat Models Mimicking Gender-affirming Hormone Therapies
Published on: January 10, 2025
Clinical differences among the aromatase inhibitors
Jennifer A Ligibel1, Eric P Winer
1Harvard Medical School, Women's Hospital, Boston, Massachusetts 02115, USA.

Abstract:
In the United States, three third-generation aromatase inhibitors are available commercially: anastrozole, letrozole, and exemestane. Anastrozole and letrozole are nonsteroidal agents, whereas exemestane is a steroid. The three agents differ in terms of structure and metabolic products and in the degree to which they suppress aromatase activity. The clinical significance of these differences is unclear. All three of the agents have been found to be equivalent or superior to megesterol acetate as a second-line therapy for metastatic breast cancer. In the first-line setting, large Phase III trials have demonstrated that anastrozole and letrozole are equivalent or superior to tamoxifen in women with metastatic disease. Multiple trials with widely varying study designs have been launched in the adjuvant setting comparing the aromatase inhibitors to tamoxifen. Early results from the ATAC (Arimidex, Tamoxifen, Alone or in Combination) trial suggest a small but statistically significant improvement in disease-free survival for anastrozole compared with tamoxifen, but further follow-up is needed. This article explores the efficacy and tolerability of the aromatase inhibitors in both the metastatic and the adjuvant settings.
Related Concept Videos
 01:16
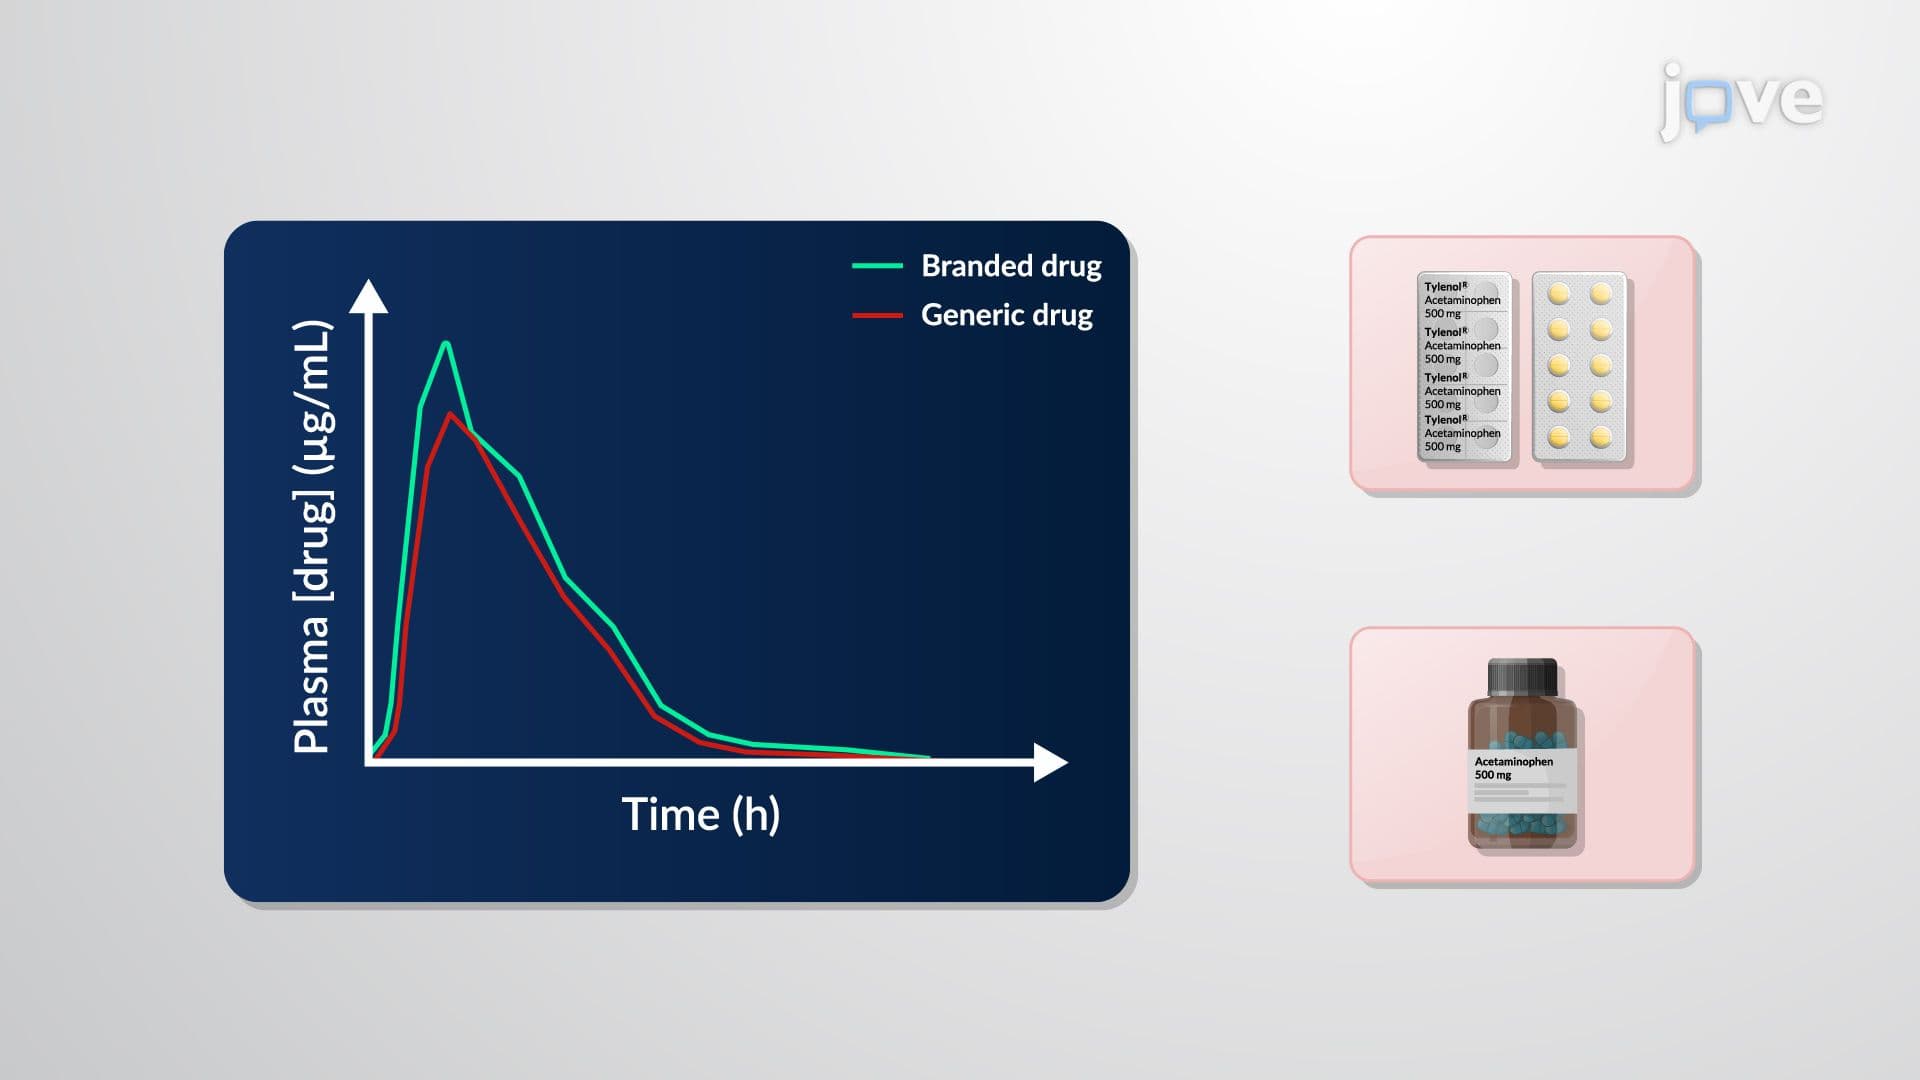
Bioequivalence Data: Statistical Interpretation
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
 01:16
Bioequivalence: Overview
 01:09
Bioequivalence of Drugs: Drugs with Multiple Indications
 01:17
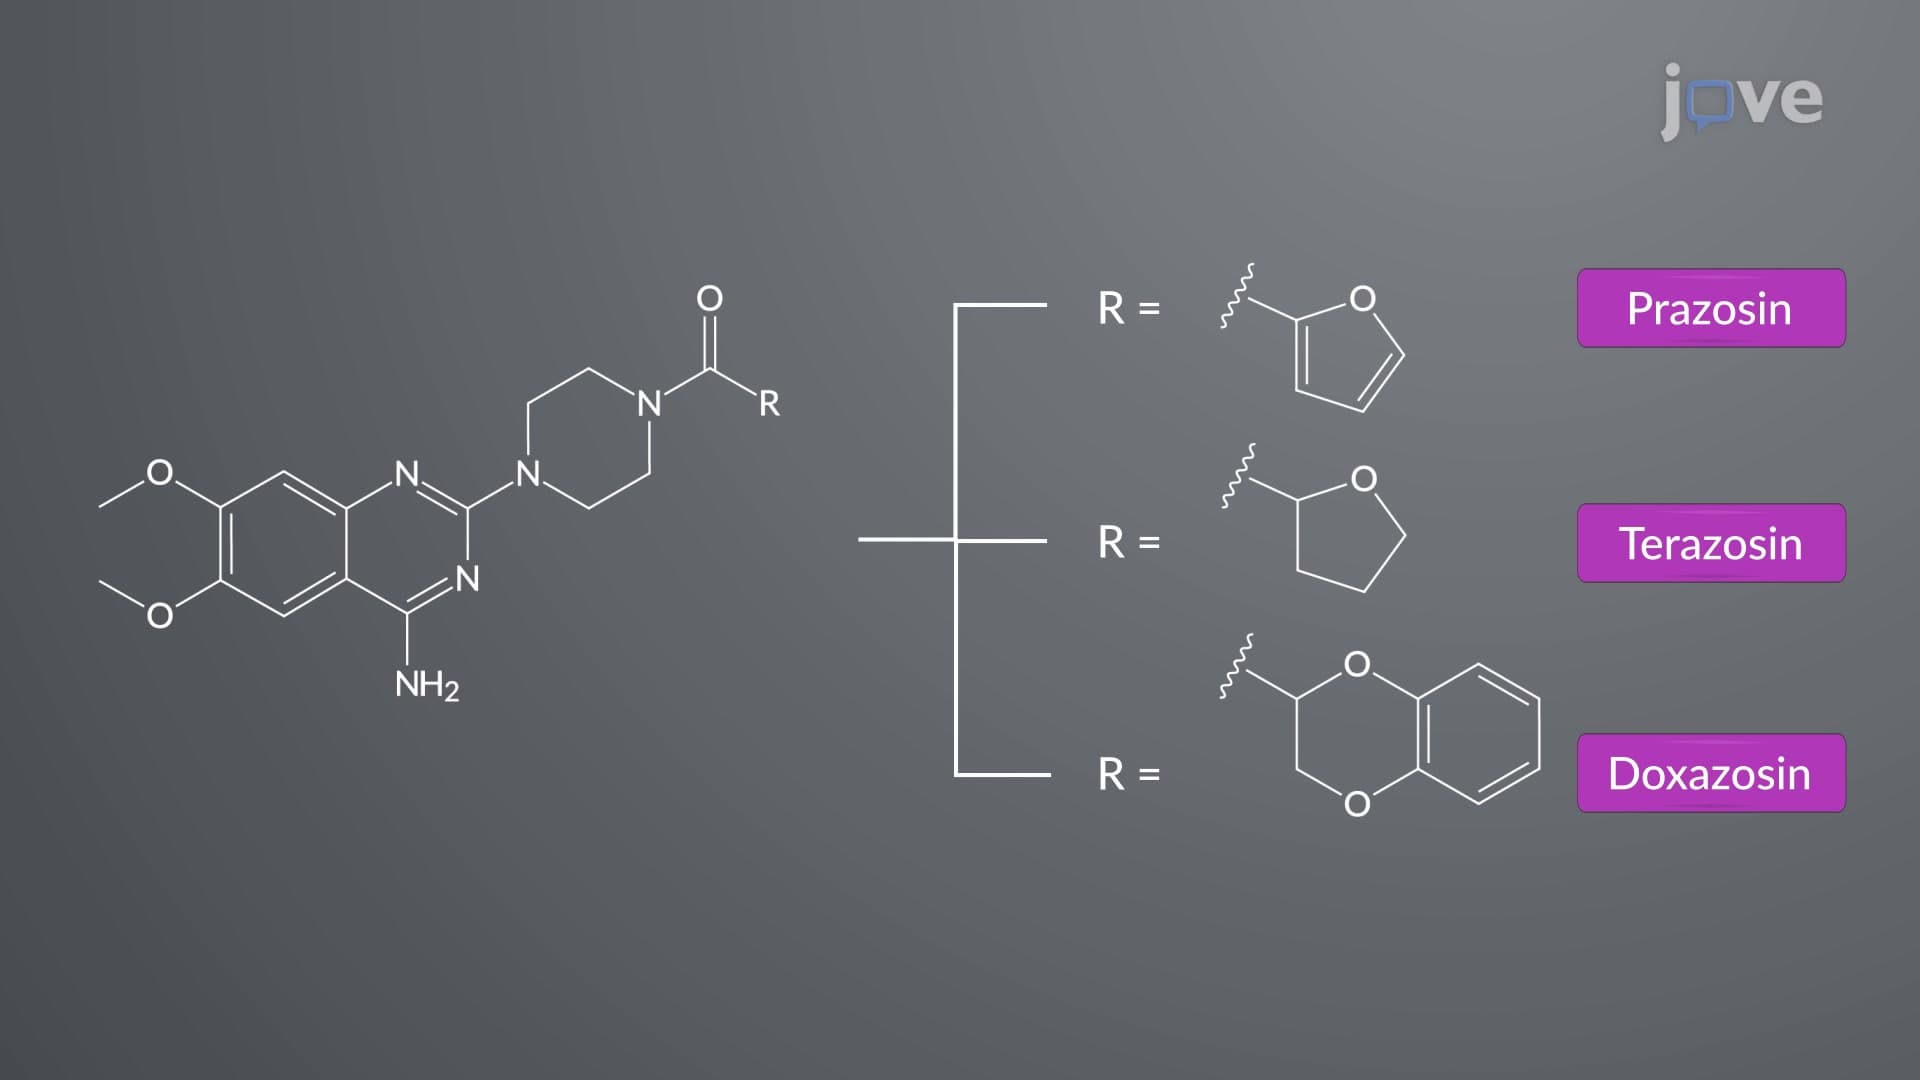
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline moieties. Phenoxybenzamine, with a haloalkylamine...
 01:27
Pharmaceutical Alternatives: Polymorphic Form-Related and Particle Size-Related Therapeutic Nonequivalence