Related Experiment Video
Updated: Aug 19, 2026


A Hyperandrogenic Mouse Model to Study Polycystic Ovary Syndrome
Published on: October 2, 2018
Ovarian and adrenal contributions to peripheral androgens in hirsute women

Abstract:
Serum levels of testosterone (T), 5alpha-dihydrotestosterone (DHT), androstenedione (A), dehydroepiandrosterone (DHEA), dehydroepiandrosterone-sulfate (DHEA-S), 17-hydroxyprogesterone (17-P), and cortisol (F) were measured in 33 hirsute women. Ten were hirsute and eumenorrheic (H-E), and 23 were hirsute and oligomenorrheic or amenorrheic (H-OA). Daily morning blood samples were obtained for 6 consecutive days. Dexamethasone (Dex), 2 mg/day was administered starting after venipuncture on the second day and continuing for 5 days. Human chorionic gonadotropin (hCG) was administered intramuscularly on the afternoon of the fourth and fifth days. The mean levels of all steroids measured under basal conditions in the hirsute women as a group were significantly elevated when compared to nonhirsute premenopausal women. Dehydroepiandrosterone-sulfate was the only steroid which showed significantly different mean levels between the two groups of hirsute women, being higher in the H-OA patients. Individual hirsute patients showed an elevated serum 17-P level as the most consistent finding; it was present in 90% of the patients in both groups. Significantly more H-E patients showed Dex-suppressible DHT (90% vs 40%; P less than 0.05) and A (70% vs 25%; P less than 0.05) than did H-OA patients. Dex-suppressibility of 17-P was observed in only 20% of the H-E and 15% of H-OA patients. A positive response to hCG was observed in all patients for serum 17-P and in about half or less of the patients for the other steroids. These dynamic tests of adrenal suppression and ovarian stimulation suggest that the ovary may be the main source of 17-P overproduction in both groups of patients. Although 17-P has been previously postulated to have androgenic activity, it is not yet known whether this steroid has a causal relationship to hirsutism.


Related Concept Videos
 01:37
Hypothalamic-Pituitary Axis
 01:17
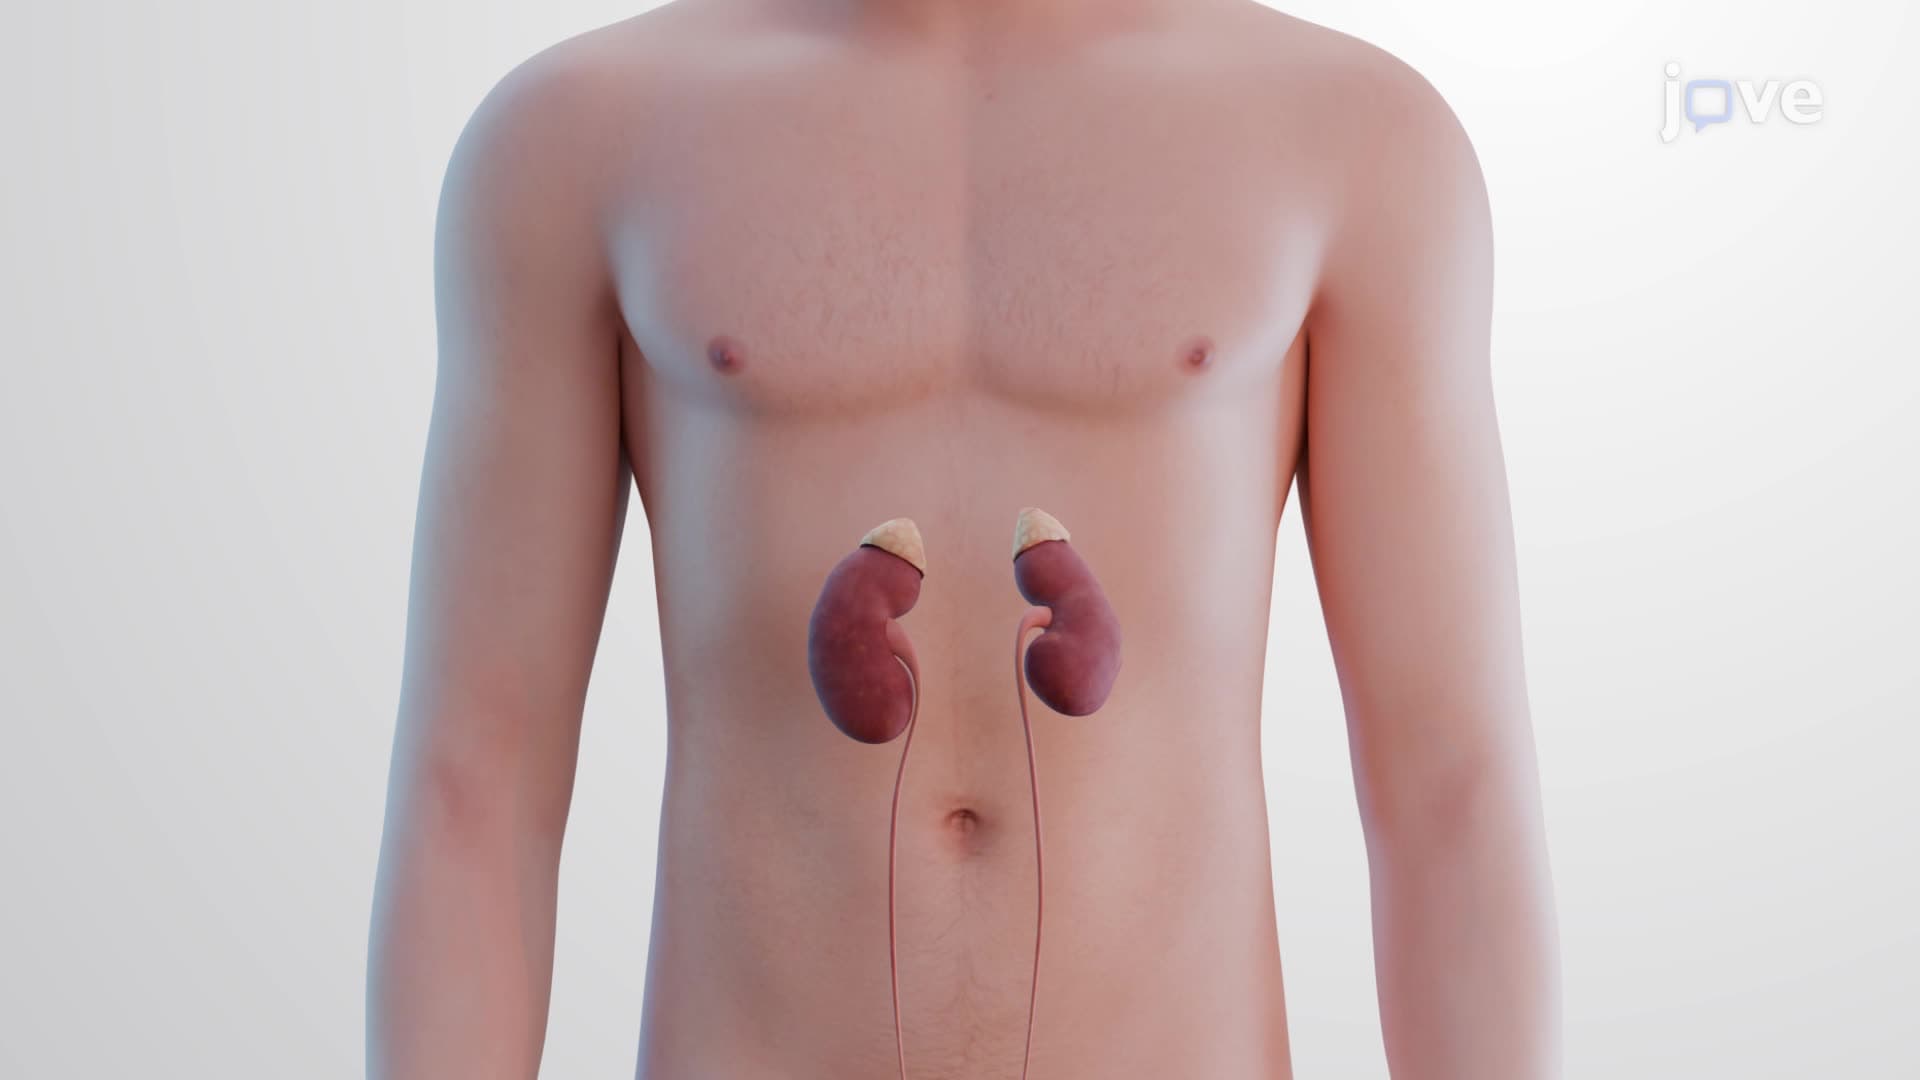
Anatomy of the Adrenal Glands
These glands possess a distinctive yellow tinge due to the stored cholesterol and fatty acids required for hormone synthesis. They are encased in a fibrous capsule and cushioned by fat.
The adrenal gland comprises two distinct regions...
 01:31
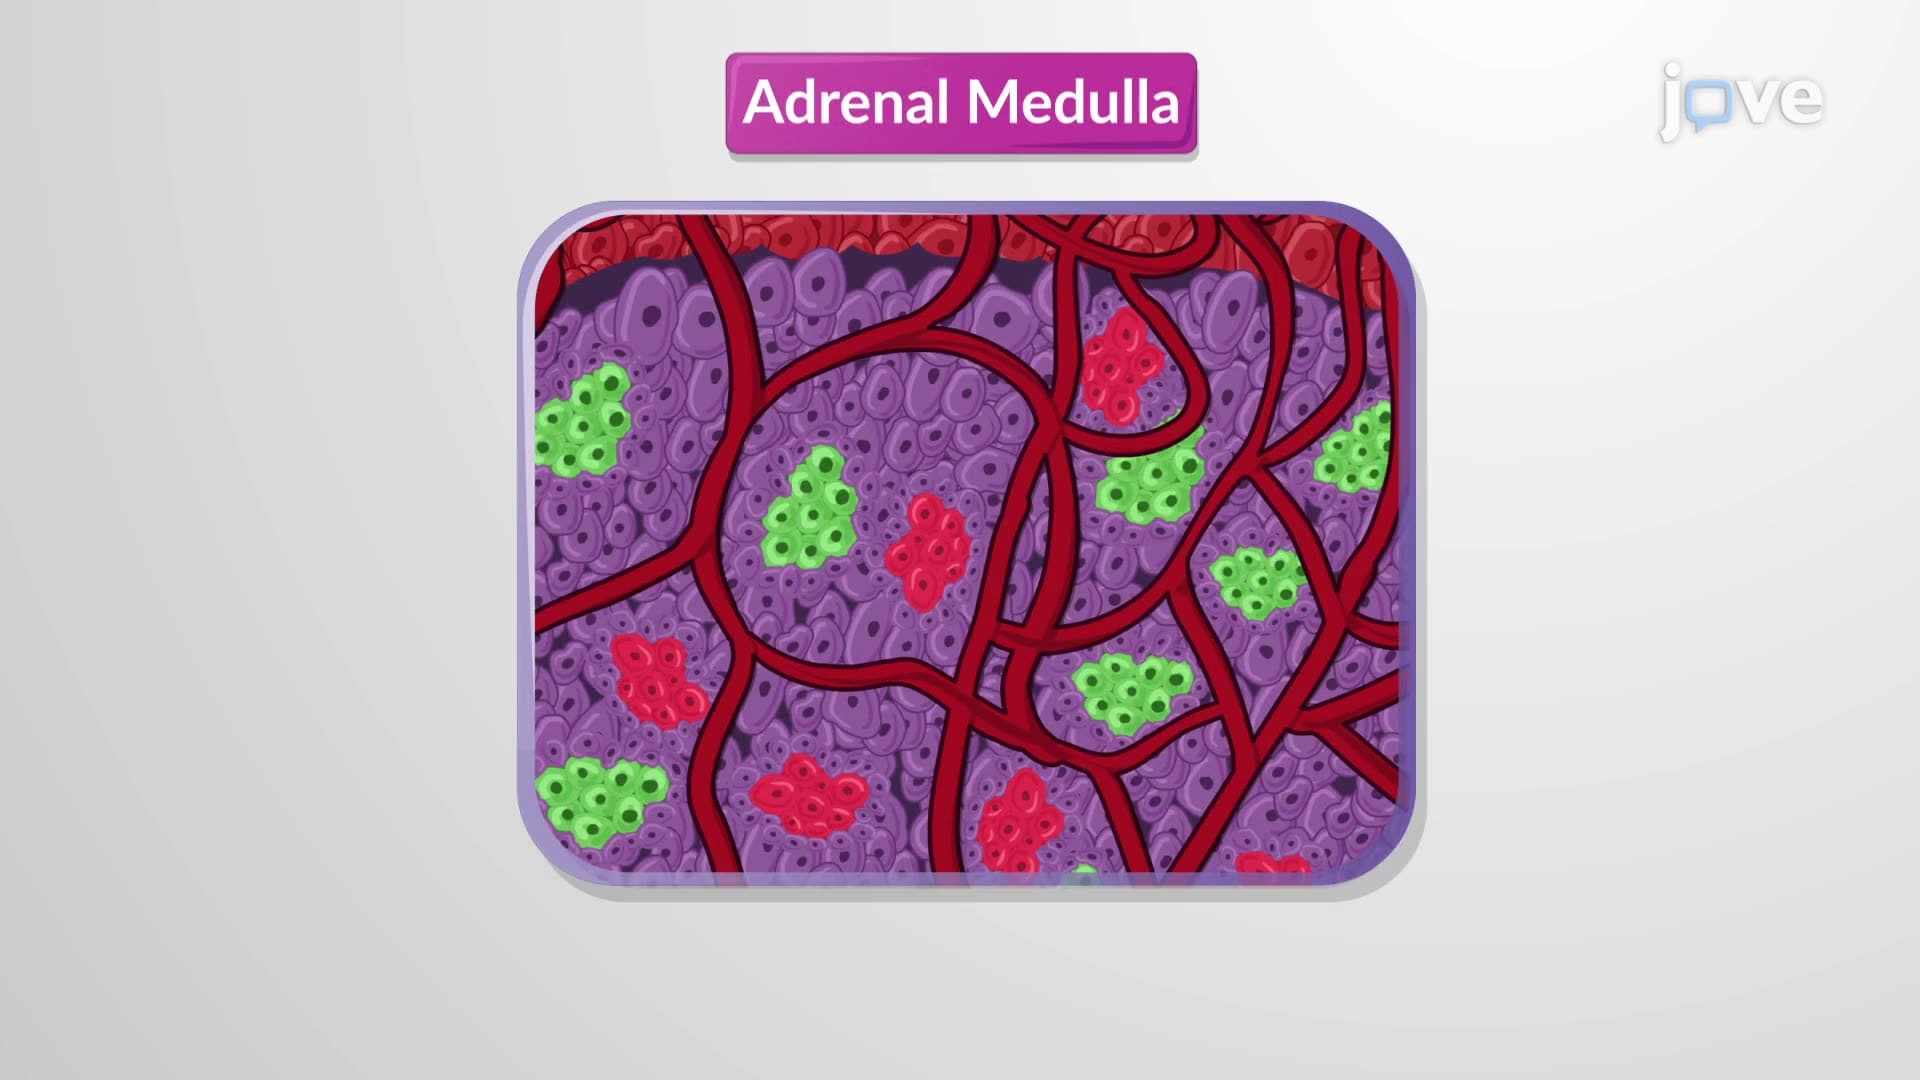
Hormones of the Adrenal Glands
The adrenal cortex, a powerhouse of hormone synthesis, generates over two dozen corticosteroid hormones. The zona glomerulosa produces mineralocorticoids, exemplified by aldosterone, influencing the electrolyte composition of body fluids. The synthesis of glucocorticoids such as cortisol and corticosterone...
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:24
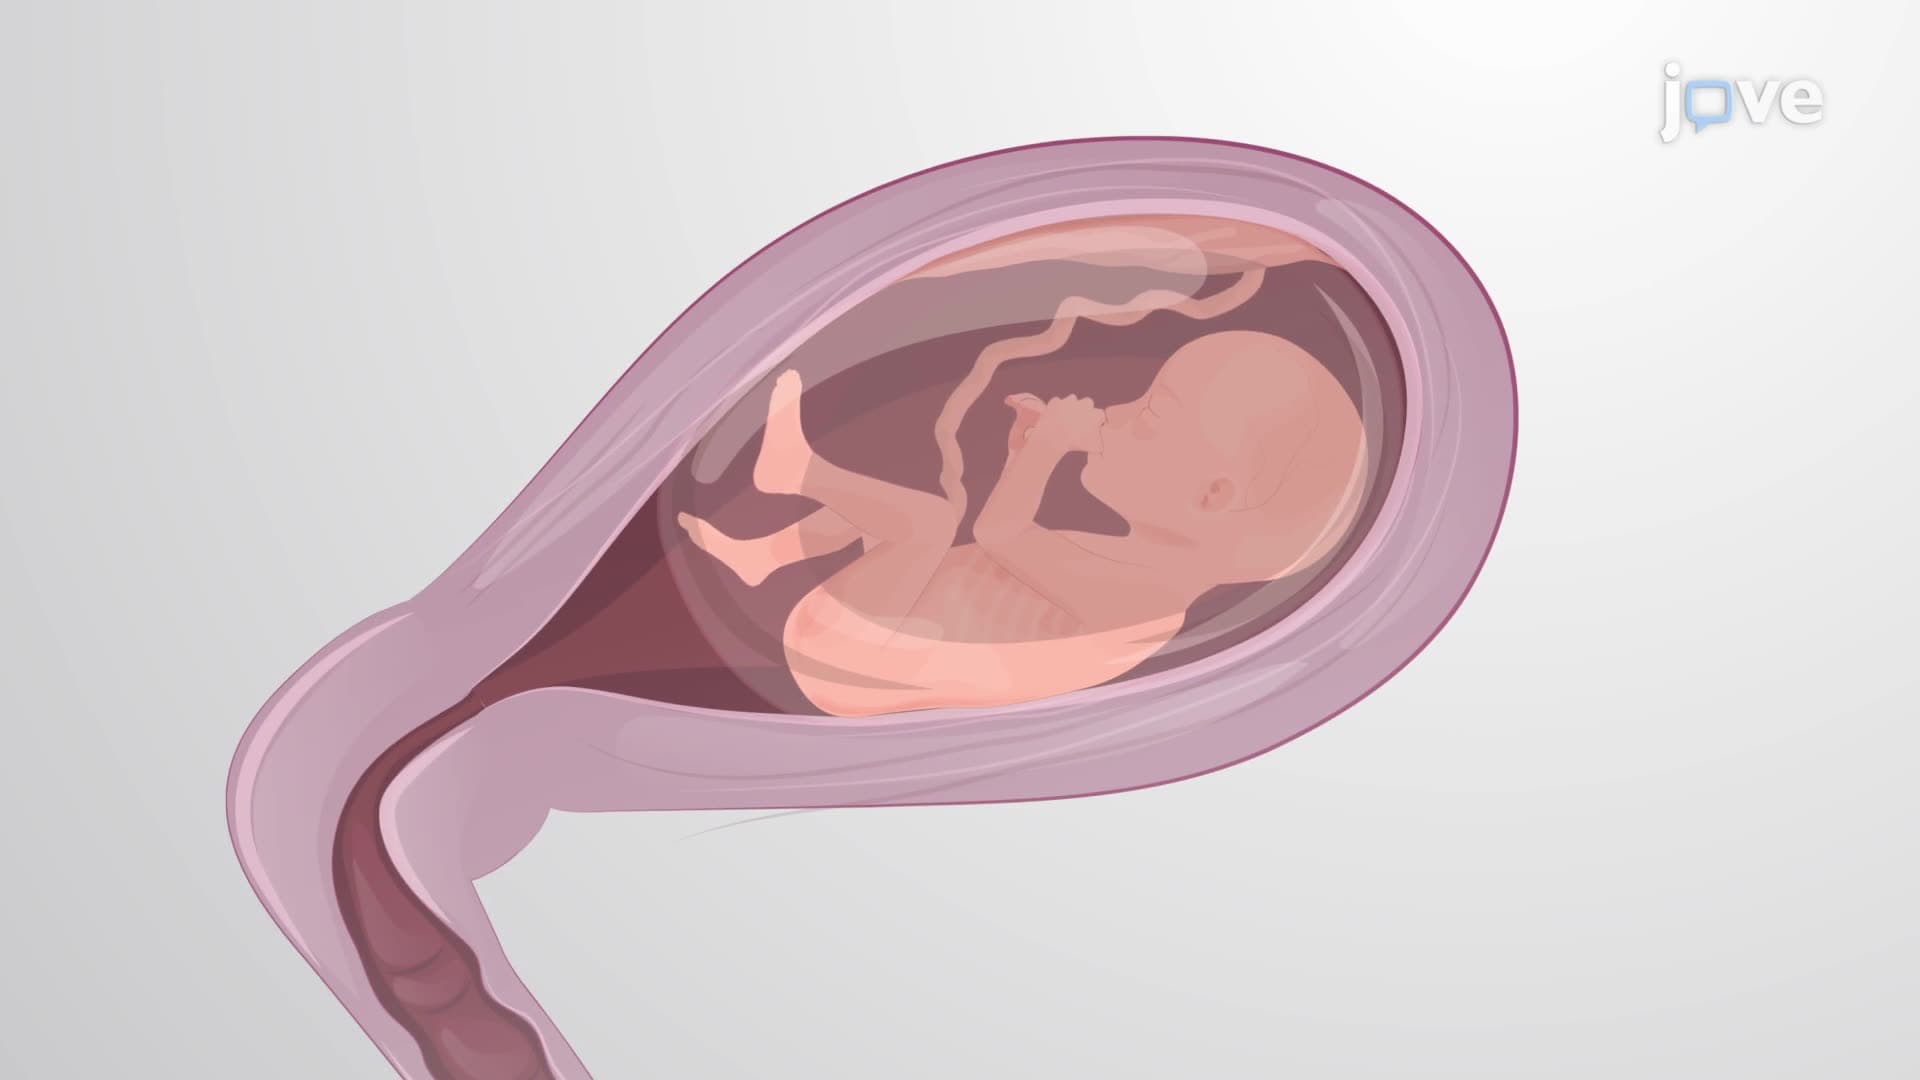
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair growth — and...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.