Related Experiment Video
Updated: Sep 21, 2026

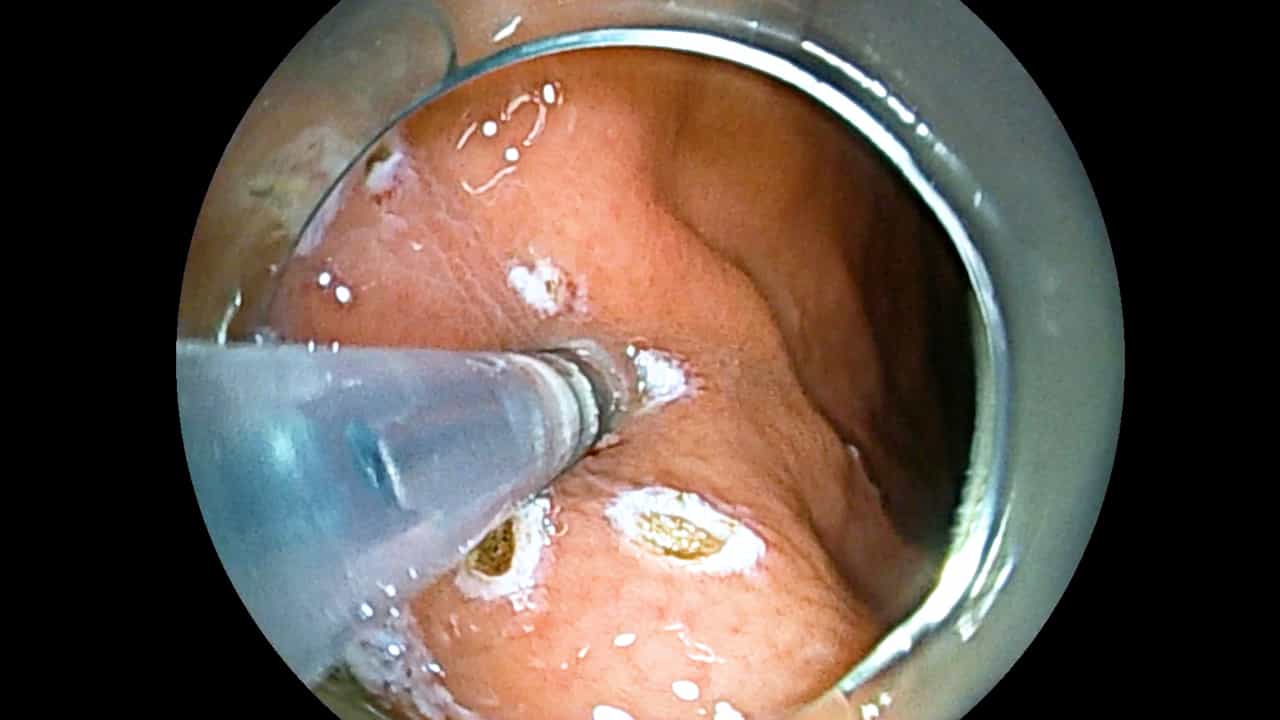
ADSC-sheet Transplantation to Prevent Stricture after Extended Esophageal Endoscopic Submucosal Dissection
Published on: February 10, 2017
Esophageal stenosis after endoscopic mucosal resection of superficial esophageal lesions
Chikatoshi Katada1, Manabu Muto, Tetsuro Manabe
1The Division of Digestive Endoscopy and Gastrointestinal Oncology, National Cancer Center Hospital East, Kashiwa, Japan.

Background:
Although bleeding and perforation are generally recognized major complications of endoscopic mucosal resection, esophageal stricture after endoscopic mucosal resection has not been well studied. Factors associated with the occurrence and severity of esophageal stenosis after endoscopic mucosal resection were investigated.
Methods:
Two hundred sixteen superficial esophageal lesions in 137 consecutive patients who underwent endoscopic mucosal resection from February 1993 through March 2001 were retrospectively studied. The circumferential extent of the mucosal defect after endoscopic mucosal resection was classified into 4 groups: under one fourth, one fourth to one half, one half to three fourths, and over three fourths. The longitudinal length of the mucosal defect was also evaluated. Stenosis was diagnosed when a standard endoscope (11-mm diameter) could not be passed through the stricture.
Results:
Esophageal stenosis developed after endoscopic mucosal resection of 13 lesions (6.0%). In all these cases endoscopic mucosal resection resulted in a mucosal defect that involved over three fourths of the luminal circumference. In the subgroup of patients with mucosal defects involving over three fourths of the circumference, those with a mucosal defect over 30 mm long required more frequent balloon dilatation (mean 8 [4.3] times) and the stenosis was of longer duration (mean 16 [17.7] months) than those with defects 30 mm or less in length (respectively, 1 [0.6] times and 2 [1.9] months).
Conclusions:
A circumferential mucosal defect involving over three fourths the circumference of the esophagus after endoscopic mucosal resection was significantly associated with the subsequent development of esophageal stenosis. In addition, mucosal defects longer than 30 mm were associated with greater severity of stenosis. When endoscopic mucosal resection is performed for superficial esophageal lesions, removal of excess mucosa should be avoided.
More Related Videos

Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:27
Esophageal Achalasia